P.S. Free & New MCCQE dumps are available on Google Drive shared by Actual4Exams: https://drive.google.com/open?id=1Z5JCrVN7fIdUPTek1QFbDb9qyrazY5PX
So we can say that the MCCQE Part 1 Exam (MCCQE) practice test questions are real, valid, and updated and these will greatly help you in MCCQE exam preparation. The availability of MCCQE Part 1 Exam (MCCQE) exam questions in three different formats, free demo download facility, affordable price, free three months updated MCCQE Exam Questions download facility, and verified and real MCCQE Part 1 Exam (MCCQE) exam questions are the top features of Actual4Exams MCCQE exam questions.
| Section | Objectives |
|---|---|
| Topic 1: Dimensions of Care | - Acute Care
|
| Topic 2: Physician Activities | - Professionalism
|
Compared with the other products in the market, our MCCQE latest questions grasp of the core knowledge and key point of the real exam, the targeted and efficient MCCQE Part 1 Exam study training dumps guarantee our candidates to pass the test easily. Passing exam won’t be a problem anymore as long as you are familiar with our MCCQE Exam Material (only about 20 to 30 hours practice). High accuracy and high quality are the reasons why you should choose us.
NEW QUESTION # 206
An 80-year-old woman presents to the Emergency Department with dizziness. She has a medical history of coronary artery disease. On examination, she is alert and oriented. Her vital signs are as follows:
Her electrocardiogram is shown in the image.
Which one of the following is the most likely diagnosis?
Blood pressure
80/60 mm Hg
Heart rate
40/min
Respiratory rate
12/min
Her electrocardiogram is shown in the attached image. Which one of the following is the most likely diagnosis?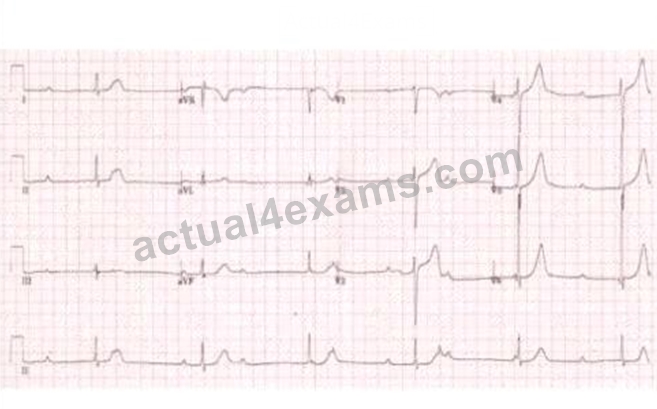
Answer: B
Explanation:
Comprehensive and Detailed Explanation:
The ECG reveals:
* Regular P waves that are not consistently followed by QRS complexes
* A dissociation between the atrial (P wave) and ventricular (QRS complex) activity
* A slow ventricular rate (~40 bpm) independent of atrial rate
These findings are characteristic of a third-degree (complete) atrioventricular (AV) block, where there is no conduction of atrial impulses to the ventricles. The atria and ventricles beatindependently, and the ventricular rate is maintained by an escape rhythm, often junctional or ventricular in origin.
This correlates with the patient's symptoms (dizziness, hypotension) and bradycardia, suggesting inadequate cardiac output due to AV dissociation.
Toronto Notes 2023 - Cardiology:
"Third-degree AV block shows complete AV dissociation with independent atrial and ventricular activity. It typically presents with bradycardia and hypotension. Urgent pacing may be required." MCCQE1 Objectives (Cardiology > 34-2: Bradyarrhythmias and Conduction Disorders):
"Candidates must identify complete heart block and recognize its clinical urgency." Ruling out other options:
* A. Sinus bradycardia would show regular P waves with 1:1 P-QRS conduction.
* B. First-degree AV block has prolonged PR intervals (>200 ms) but all P waves are conducted.
* D. Junctional escape rhythm may present with bradycardia, but P waves would be absent, inverted, or occur after QRS complexes.
* E. Mobitz type I (Wenckebach) has progressively lengthening PR intervals before a dropped QRS.
NEW QUESTION # 207
A 20-year-old woman from a remote northern community presents to the office with a 2-week history of malaise and a 2-day history of disabling pain in her left elbow. She had a sore throat 4 weeks ago. She also notes that she has had 2 weeks of pain and swelling in her right knee, followed by pain and swelling in her left elbow. On examination, you note 0.5-cm to 1-cm nodules just above both her elbows. You find no active joint swelling. An electrocardiogram shows a prolonged PR interval. Which one of the following is the most appropriate investigation?
Answer: E
Explanation:
This presentation is most consistent with acute rheumatic fever (ARF): a history of pharyngitis 4 weeks earlier, migratory large-joint pain/swelling (knee then elbow), subcutaneous nodules over extensor surfaces, and prolonged PR interval (a Jones minor criterion indicating cardiac involvement). MCCQE objectives emphasize that diagnosing ARF requires meeting Jones criteria plus evidence of preceding group A streptococcal (GAS) infection. Because the sore throat occurred weeks ago, a pharyngeal culture is often negative and is less useful for establishing prior GAS infection. The most appropriate test is therefore an antistreptolysin O (ASO) titre (or other streptococcal serology such as anti-DNase B), which documents a recent streptococcal immune response and supports the diagnosis. Echocardiography can assess severity of carditis/valvular disease, but it does not provide the required evidence of preceding GAS infection.
Rheumatoid factor and biopsy of nodules do not address the likely ARF diagnosis.
NEW QUESTION # 208
A 43-year-old man comes to your office for the first time. He has not seen a doctor in over 5 years and has no known past medical history. On examination, his blood pressure is 120/70 mm Hg, and the remainder of his examination is normal. As part of the initial visit, you order some screening blood work that reveals a fasting blood glucose of 6.3 mmol/L (3.3-5.8) and a hemoglobin A1c of 6.1% (4-6). Which one of the following is the best next step?
Answer: C
Explanation:
This patient's lab results suggest impaired fasting glucose and an elevated A1c just below the threshold for diabetes. The gold standard to confirm diabetes in such intermediate cases is the 75 g oral glucose tolerance test (OGTT).
Toronto Notes 2023 - Endocrinology, "Diabetes Mellitus" Section:
"If A1c is in the 6.0-6.4% range or fasting glucose 6.1-6.9 mmol/L, a 75 g OGTT is recommended to establish the diagnosis of diabetes or confirm impaired glucose tolerance." MCCQE1 Objectives (Internal Medicine > 76-4: Diabetes):
"Candidates must correctly apply diabetes screening and diagnostic criteria and follow up abnormal results with appropriate confirmatory testing." Urine ACR (C) is useful in diagnosed diabetes, not for initial screening. TSH (A), capillary glucose testing (B), and exercise testing (E) are not indicated at this stage.
NEW QUESTION # 209
A 6-week-old boy is brought to your office by his parents for a follow-up following a recent urinary tract infection. His abdominal ultrasound shows dilated urinary bladder and ureters as well as bilateral hydronephrosis. Which one of the following historical findings would be most helpful in establishing the correct diagnosis?
Answer: C
Explanation:
This infant has evidence of urinary outflow obstruction on ultrasound. The most common cause in male infants is posterior urethral valves. Poor urinary stream is a hallmark symptom of bladder outlet obstruction in neonates.
Toronto Notes 2023 - Pediatrics, "Pediatric Urology" Section:
"Posterior urethral valves should be suspected in male infants with recurrent UTIs, hydronephrosis, and a weak urinary stream. Diagnosis is confirmed by voiding cystourethrogram." MCCQE1 Objectives (Pediatrics > 78-4: Urinary Tract Abnormalities):
"Candidates must identify congenital causes of urinary obstruction. Poor stream and hydronephrosis are classic features of posterior urethral valves." Crying with urination (E) is nonspecific. Hematuria (B) and malodorous urine (D) are common with infections. Circumcision (A) is unrelated.
NEW QUESTION # 210
A 34-year-old woman, gravida 3, para 2, aborta 0, presents at 38 weeks' gestation. She is in early labor with ruptured membranes. Her previous pregnancy was complicated by fever during labor. Which one of the following would increase the risk of fever recurrence?
Answer: C
Explanation:
Comprehensive and Detailed Explanation:
Epidural analgesia is associated with increased maternal intrapartum fever due to non-infectious(neurogenic) thermoregulation impairment. This is a well-known phenomenon in laboring women.
Toronto Notes 2023 - Obstetrics / Anesthesia:
"Epidural analgesia increases risk of intrapartum fever by up to 20% via non-infectious mechanisms." MCCQE1 Objectives (Obstetrics > 80-5: Intrapartum Care):
"Candidates must recognize risk factors for intrapartum complications, including effects of epidural use." Multiparity (A), precipitous labor (B), and maternal age (C) are not established risk factors for intrapartum fever.
NEW QUESTION # 211
......
The Medical Council of Canada MCCQE web-based practice exam software can be easily accessed through browsers like Safari, Google Chrome, and Firefox. The customers do not need to download or install excessive software or applications to take the MCCQE Part 1 Exam (MCCQE) web-based practice exam. The MCCQE web-based practice exam software format can be accessed through any operating system like Windows or Mac.
Real MCCQE Braindumps: https://www.actual4exams.com/MCCQE-valid-dump.html
BONUS!!! Download part of Actual4Exams MCCQE dumps for free: https://drive.google.com/open?id=1Z5JCrVN7fIdUPTek1QFbDb9qyrazY5PX