What's more, part of that TrainingDumps EFM dumps now are free: https://drive.google.com/open?id=16trYXZIeCQCi5i12PFVBYqYOlkV7LnAC
Many exam candidates feel hampered by the shortage of effective EFM preparation quiz, and the thick books and similar materials causing burden for you. Serving as indispensable choices on your way of achieving success especially during this EFM Exam, more than 98 percent of candidates pass the exam with our EFM training guide and all of former candidates made measurable advance and improvement.
| Section | Objectives |
|---|---|
| Fetal Physiology and Oxygenation | - Fetal cardiovascular physiology - Oxygen transport and acid-base balance |
| Maternal and Fetal Complications | - Hypoxia and uteroplacental insufficiency - High-risk obstetric conditions affecting fetal monitoring |
| Uterine Activity | - Tachysystole and abnormal contraction patterns - Normal uterine contraction patterns |
| Intrapartum Assessment and Monitoring | - External and internal monitoring techniques - Risk assessment during labor |
| Fetal Heart Rate Interpretation | - Accelerations and decelerations - Baseline rate and variability - Category I, II, and III tracing interpretation |
| Intrauterine Resuscitation and Interventions | - Maternal position changes and oxygen administration - Fluid management and medication adjustments |
>> EFM Latest Exam Discount <<
The TrainingDumps is committed to making the NCC EFM exam preparation journey simple, smart, and swift. To meet this objective the TrainingDumps is offering EFM practice test questions with top-rated features. These features are updated and real EFM exam questions, availability of NCC EFM Exam real questions in three easy-to-use and compatible formats, three months free updated EFM exam questions download facility, affordable price and 100 percent Certified - Electronic Fetal Monitoring EFM exam passing money back guarantee.
NEW QUESTION # 79
(Full question statement)
The fetal heart rate tracing shown is obtained upon the woman's admission to labor and delivery. This tracing is most consistent with what maternal condition?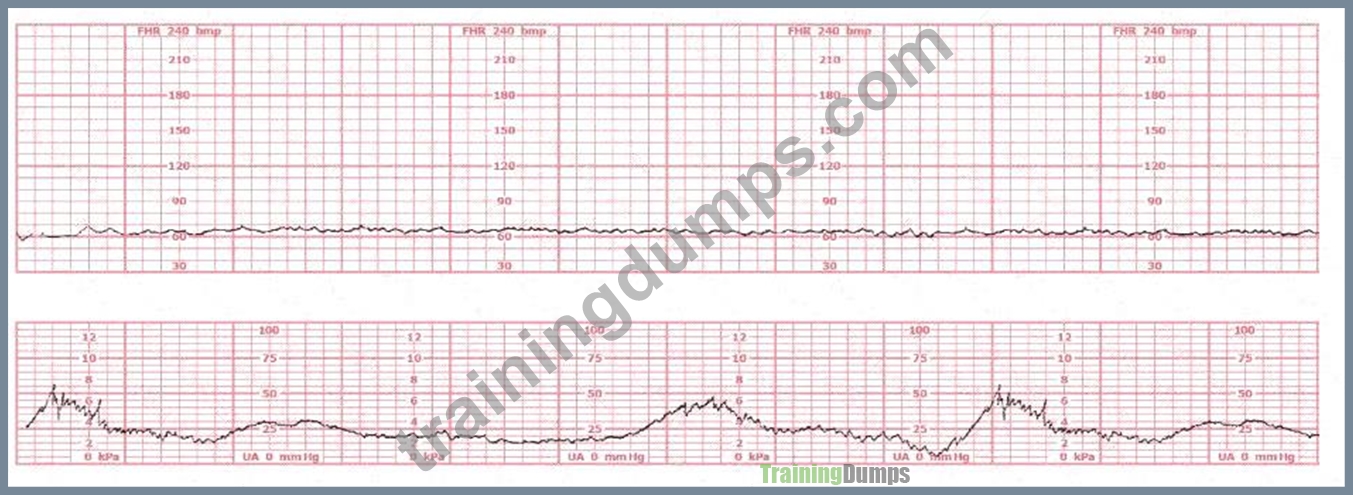
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract (NCC C-EFM sources: AWHONN, Miller's Pocket Guide, Menihan, Simpson, Creasy & Resnik, 2025 Candidate Guide) The tracing displays baseline fetal bradycardia, with a rate near 100 bpm, minimal variability, and preserved periodic response. According to AWHONN's Fetal Heart Monitoring Principles & Practices and Menihan's Electronic Fetal Monitoring, maternal conditions that reduce oxygen-carrying capacity- including maternal anemia-can lead to lower fetal oxygen delivery, prompting a fetal compensatory bradycardic baseline.
Creasy & Resnik's Maternal-Fetal Medicine notes that sickle cell anemia decreases maternal hemoglobin function even when maternal vital signs appear stable, reducing uteroplacental oxygen transport. Fetuses of mothers with sickling disorders may demonstrate lower resting fetal heart rates due to chronic mild hypoxemia.
Conversely, Eisenmenger's syndrome is associated with severe maternal cyanosis and high fetal mortality, often producing late decelerations and growth restriction rather than mild bradycardia. Systemic lupus erythematosus (SLE) is commonly associated with heart block (especially with anti-Ro/SSA antibodies), which is not displayed here, as true heart block presents with a fixed atrial-ventricular dissociation and FHR
< 60 bpm.
Thus, based on fetal physiology and maternal disease correlations taught in NCC-recommended sources, the tracing is most consistent with maternal sickle cell anemia.
NEW QUESTION # 80
The baseline fetal heart rate in this tracing is: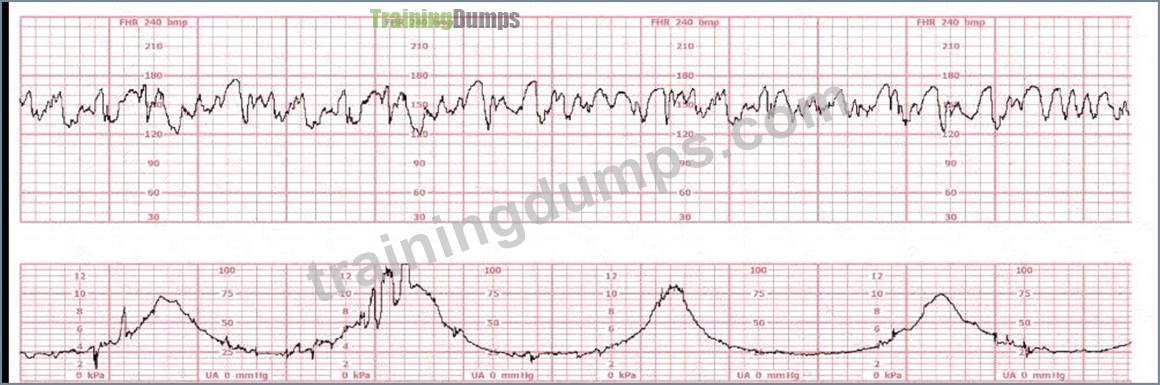
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
On the tracing:
* FHR consistently ranges 170-185 bpm.
* Variability remains present, confirming adequate signal.
* This pattern persists for the required minimum 10-minute baseline window.
NICHD/NCC define fetal tachycardia as:
* Baseline > 160 bpm for at least 10 minutes
Because the FHR is well above 160 for the whole reviewable period, the baseline is tachycardic.
Why the other answers are incorrect:
* A. 155 bpm - Too low; FHR visually averages well above this.
* B. Indeterminate - Not applicable; variability is clear and the tracing meets the #10-minute rule.
Correct answer: C. Tachycardia
References:NICHD Definitions; NCC C-EFM Candidate Guide; AWHONN; Miller; Menihan.
NEW QUESTION # 81
A pattern of recurrent variable decelerations would move from Category II to Category III if what fetal heart rate change occurs?
Answer: A
NEW QUESTION # 82
A fetal heart rate deceleration that is episodic is a/an:
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
NCC and NICHD differentiate:
* Periodic decelerations - those occurring with contractions
* Episodic decelerations - those occurring independent of contractions
Deceleration types:
* Early - periodic (mirror contractions)
* Late - periodic (after peak of contraction)
* Variable - may be periodic or episodic, and are the only type strongly associated with episodic patterns** Therefore, the only deceleration type that is characteristically episodic is a variable deceleration.
Correct answer: C. Variable deceleration
References:NICHD FHR Definitions; NCC C-EFM Guide; AWHONN; Menihan; Simpson & Creehan.
NEW QUESTION # 83
A patient presents at 38-weeks gestation with complaints of decreased fetal movement and ruptured membranes. The fetal heart rate is not able to be determined with an external ultrasound monitor. A spiral electrode is placed, and the tracing shows a rate of 90 bpm. What is the next most appropriate action?
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
Whenever a fetal heart rate is unexpectedly low (such as 90 bpm), the FIRST step per NCC and AWHONN is to confirm that the signal is fetal, not maternal.
Even internal spiral electrodes can capture maternal heart rate, especially after:
* Rupture of membranes
* Maternal hypotension
* Maternal dehydration
* Maternal tachycardia or bradycardia
Thus, the first, most immediate action is:
# Palpate the maternal radial pulse to determine whether the tracing is maternal or fetal.
If rates match # the monitor is falsely detecting the maternal pulse.
If rates differ # confirm true fetal bradycardia and begin intrauterine resuscitation.
Why the other options are incorrect:
* A. Intrauterine resuscitation - should NOT begin before confirming the tracing is fetal.
* C. Bedside ultrasound - appropriate after confirming that the tracing is not maternal, not before.
Correct answer: B. Palpation of the maternal radial pulse.
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; Menihan; Miller's Pocket Guide; Simpson
& Creehan.
NEW QUESTION # 84
......
We provide 24-hours online customer service which replies the client’s questions and doubts about our EFM training quiz and solve their problems. Our professional personnel provide long-distance assistance online. Our expert team will check the update EFM learning prep and will send the update version automatically to the clients. So the clients can enjoy the convenience of our wonderful service and the benefits brought by our superior EFM guide materials.
Test EFM Questions Vce: https://www.trainingdumps.com/EFM_exam-valid-dumps.html
P.S. Free 2026 NCC EFM dumps are available on Google Drive shared by TrainingDumps: https://drive.google.com/open?id=16trYXZIeCQCi5i12PFVBYqYOlkV7LnAC