Don't underestimate the difficulty level of the ACDIS CCDS certification exam because it is not easy to clear. You need to prepare real CCDS exam questions to get success. If you do not prepare with actual CCDS Questions, there are chances that you may fail the final and not get the CCDS certification.
| Section | Weight | Objectives |
|---|---|---|
| Official Guidelines for Coding and Reporting | 14.17% | - Coding guidelines for principal diagnosis selection - Hospital-acquired conditions - AHA Coding Clinic - Present on admission indicators - Working DRG assignment for multiple diagnoses - Official Guidelines for Coding and Reporting updates - Discharge dispositions and transfers - Secondary diagnosis assignment - Principal diagnosis assignment |
| Medical record documentation | 19.17% | - ACDIS/AHIMA Guidelines for Achieving a Compliant Query Practice - Provider role and diagnosis code assignment - Types of physician queries - Addressing diagnoses without clinical support - Translating clinical indicators into compliant queries - Physician query formats - Health record elements used for diagnosis and procedure code assignment - When a physician query is warranted - Documentation requiring clarification - Situations in which queries are not appropriate - Compliant and noncompliant queries - Clinical indicators |
| Healthcare facility CDI program analysis | 8.33% | - PEPPER data - Publicly reported data - CDI program forecasting - Physician performance measurement - Severity of illness and risk of mortality - Hospital Value-Based Purchasing measures - High-frequency DRGs - CDI specialist productivity metrics - Tracking and trending physician, department, and hospital performance - CC/MCC capture - Hospital-specific financial data - Provider response rates - Patient Safety Indicators - Basic computer and software application skills - Case mix index (CMI) |
| Anatomy and physiology, pathophysiology, pharmacology, and medical terminology | 19.17% | - Diseases and disorders of the skin, subcutaneous tissue, and breast - Injuries, poisonings, and toxic effects of drugs - Diseases and disorders of the hepatobiliary system - Infectious and parasitic diseases - Diseases and disorders of the blood and blood-forming organs and immunological disorders - Diseases and disorders of the digestive system - Pharmaceuticals and disease processes - Standard medical abbreviations - Diseases and disorders of the kidney and urinary tract - Clinical indicators and query opportunities by Major Diagnostic Category - Mental diseases and disorders - Diseases and disorders of the circulatory system - Diseases and disorders of the respiratory system - Endocrine, nutritional, and metabolic diseases and disorders - Alcohol/drug use and alcohol/drug-induced organic brain disorders - Diseases and disorders of the nervous system - Myeloproliferative diseases and disorders and poorly differentiated neoplasms - Medications as clinical indicators - HIV infections - Diseases and disorders of the musculoskeletal system - Diagnostic tests as clinical indicators |
| Professionalism, ethics, and compliance | 9.17% | - DRG compliance initiatives - Leading queries - Medical record confidentiality - Potential DRG creep - Compliance risks indicated by PEPPER - CDI department goals beyond reimbursement |
| Impact of reportable diagnoses on quality of care | 8.33% | - CDI impact on Hospital Value-Based Purchasing - Hospital Value-Based Purchasing - Quality data from record abstraction and claims data - Healthcare-associated infections and complication codes - Documentation and code assignment impact on mortality index - Hospital Inpatient Quality Reporting Program - 30-day mortality measures - Coded data elements affecting Patient Safety Indicators - Hospital-Acquired Condition Reduction Program - Hospital Readmissions Reduction Program - Patient Safety Indicators - Mortality reviews and observed/expected ratios |
| Communication skills | 9.17% | - Effective and non-confrontational physician communication - Reconciling CDI working DRGs with final coded DRGs - Verbal versus written physician communication - Roles and responsibilities of CDI specialists - Physician education forms and tools - Educational presentations for healthcare departments and administration - Roles and responsibilities of coders working with CDI departments |
| Healthcare regulations, reimbursement, and documentation requirements related to the IPPS | 12.5% | - Medicare Severity Diagnosis Related Groups (MS-DRGs) - Documentation impact on IPPS reimbursement - IPPS and its updates and revisions - Complication/comorbidity (CC) - Principal diagnosis and medical necessity - Medical staff and clinical staff documentation responsibilities - Documentation and medical necessity of setting - Coding and billing practices vulnerable to denial - Major complication/comorbidity (MCC) - Inpatient admission criteria and CMS Two-Midnight Rule - Case mix index (CMI) - Medicare contractors and their impact on CDI |
In order to save you a lot of installation troubles, we have carried out the online engine of the CCDS latest exam guide which does not need to download and install. This kind of learning method is convenient and suitable for quick pace of life. But you must have a browser on your device. Also, you must open the online engine of the study materials in a network environment for the first time. In addition, the CCDS Study Dumps don’t occupy the memory of your computer. When the online engine is running, it just needs to occupy little running memory. At the same time, all operation of the online engine of the CCDS training practice is very flexible as long as the network is stable.
NEW QUESTION # 119
During one month, a CDI department issued 400 queries. Providers responded to 360 of them. What was the provider query response rate?
Answer: D
Explanation:
Provider query response rate is calculated by dividing the number of answered queries by the total number of queries requiring a response, then multiplying by 100.
360 ÷ 400 × 100 = 90%.
Therefore, the provider response rate is 90%.
Response rate measures whether clinicians engage with documentation clarification requests. It should be distinguished from agreement rate, which measures how often the provider's response supports the diagnosis or clarification being considered. A physician can respond appropriately while disagreeing with the proposed diagnostic possibilities, so a lower agreement rate does not necessarily indicate poor engagement.
A CDI manager should also evaluate response timeliness, service-line patterns, unanswered-query aging, escalation frequency, and whether responses result in complete documentation.
A response rate should not be artificially increased by pressuring providers to choose a particular answer.
Current ACDIS/AHIMA guidance emphasizes a compliant clarification process that preserves independent provider judgment.
In mature CDI programs, metrics are best evaluated longitudinally rather than in isolation. Significant changes should be examined for workflow, staffing, education, electronic-query functionality, or physician- engagement factors.
CCDS Reference Topics: Query response rate; CDI metrics; provider engagement; program analysis; communication.
=========
NEW QUESTION # 120
A patient presents to the ED following a motor vehicle crash with a lacerated spleen. The patient's BP is 80
/60, HR is 160, and the patient receives dopamine, a 2-L saline bolus, and 3 units of PRBCs. The physician documents MVA with lacerated spleen. Based on these clinical indicators, which of the following conditions would BEST reflect the accurate acuity of this patient?
Answer: C
Explanation:
The clinical presentation most strongly supports clarification of hypovolemic shock, specifically hemorrhagic shock in the context of traumatic splenic bleeding. Profound hypotension at 80/60 mmHg, extreme tachycardia at 160 beats/min, substantial crystalloid resuscitation, transfusion of three units of packed red blood cells, and vasopressor support demonstrate severe circulatory compromise.
Acute blood loss anemia may also be present and should be documented when clinically supported, but it does not fully represent the patient's hemodynamic instability. Shock describes failure of effective tissue perfusion and therefore more accurately captures the immediate physiologic severity.
SIRS due to trauma is less specific than the evident volume-loss state and would not adequately describe the hemorrhagic circulatory collapse. The record already identifies splenic laceration; "ruptured spleen" should not be substituted without provider confirmation and appropriate operative/imaging evidence.
For CDI purposes, this is a classic situation in which documentation of only the anatomical injury understates the patient's physiologic acuity. A neutral query can present the documented hypotension, tachycardia, transfusion, fluids, and vasoactive treatment and request clarification of the associated condition.
CCDS Reference Topics: Shock; trauma; hemorrhage; acute blood loss; severity-of-illness documentation.
=========
NEW QUESTION # 121
A patient has hypertension and acute on chronic diastolic heart failure documented during the same admission. The physician does not explicitly link the conditions and does not state that they are unrelated.
Which statement is MOST accurate?
Answer: A
Explanation:
ICD-10-CM generally presumes a causal relationship between hypertension and qualifying heart disease, including heart failure, when both are documented and the provider has not stated that they are unrelated.
The appropriate hypertensive heart-disease code is assigned together with an additional I50.- code identifying the specific heart-failure type and acuity.
The presumption is not limited to systolic heart failure. Diastolic and combined heart-failure diagnoses are included when they meet the applicable classification rules.
Therefore, a query solely asking the physician to state that hypertension caused the heart failure is generally unnecessary when both conditions are documented and no contradictory statement exists.
CDI should nevertheless query if the heart-failure type or acuity is unclear, documentation conflicts, or the provider explicitly indicates another relationship that affects classification.
Understanding presumed relationships is important because unnecessary queries consume physician time and create avoidable administrative work. CDI specialists must distinguish clinical relationships that require explicit provider linkage from those supplied by ICD-10-CM conventions.
CCDS Reference Topics: Hypertensive heart disease; heart failure; presumed causal relationship; coding conventions; query reduction.
=========
NEW QUESTION # 122
The table below shows physician performance: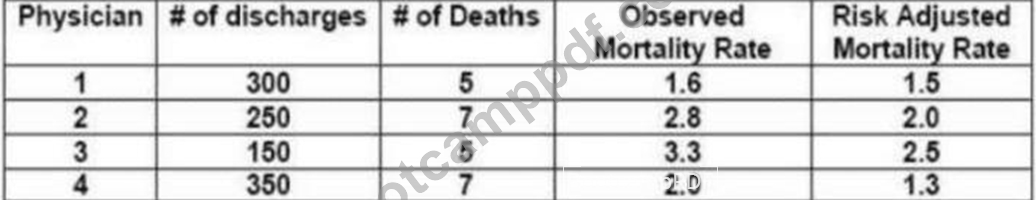
Which of the following physicians will have the most favorable mortality rate on a public website, such as Healthgrades.com?
Answer: A
Explanation:
Physician 4 has the most favorable risk-adjusted mortality rate, at 1.3, compared with Physician 1 at 1.5, Physician 2 at 2.0, and Physician 3 at 2.5. Although Physician 1 has fewer observed deaths and an observed mortality rate of 1.6%, public outcome comparisons commonly incorporate risk adjustment rather than relying solely on raw mortality. Risk adjustment attempts to account for differences in patient complexity, comorbid disease burden, demographic factors, and other characteristics that influence expected outcomes.
This is directly relevant to CDI because incomplete documentation of clinically significant comorbidities can understate patient severity and therefore adversely affect the expected mortality component of risk-adjusted performance calculations. Conversely, accurate documentation allows coded data to represent the actual severity and risk of the population being treated. Healthgrades specifically states that its mortality methodology adjusts for patient risk factors to permit more meaningful comparisons of clinical outcomes.
The CCDS content outline specifically requires knowledge of mortality indices, severity of illness/risk of mortality, physician performance, and the effect of documentation on publicly reported data.
CCDS Reference Topics: Impact of reportable diagnoses on quality of care; Healthcare facility CDI program analysis; mortality index and risk adjustment.
=========
NEW QUESTION # 123
A patient's record contains fever, tachycardia, hypotension, positive blood cultures, and treatment with IV antibiotics and fluids. No corresponding diagnosis has been documented. Which query format is MOST appropriate?
Answer: B
Explanation:
A neutral multiple-choice query is appropriate when significant clinical indicators exist but no corresponding diagnosis has been documented. The query should present the relevant patient-specific facts and allow the provider to exercise independent clinical judgment among reasonable alternatives.
For example, depending on the complete record, options could include sepsis, localized infection without sepsis, bacteremia, another condition, or unable to determine. Each offered diagnosis must be clinically supported.
A yes/no query is generally inappropriate when it introduces a completely new diagnosis that has never appeared in the health record. Option B is overtly leading because it directs the provider to document sepsis rather than requesting clarification.
The 2026 ACDIS/AHIMA compliant-query guidance, published August 20, 2026, supersedes all previous versions and serves as the current foundational standard for CDI and coding query practice. It applies across inpatient, outpatient, ambulatory, and professional-fee settings.
The purpose of the query is documentation integrity-not obtaining an MCC, changing the MS-DRG, or achieving a particular quality result.
CCDS Reference Topics: Multiple-choice queries; missing diagnosis; nonleading queries; clinical indicators; compliance.
=========
NEW QUESTION # 124
......
As a matter of fact, since the establishment, we have won wonderful feedback and ceaseless business, continuously working on developing our CCDS test prep. We have been specializing CCDS exam dumps many years and have a great deal of long-term old clients, and we would like to be a reliable cooperator on your learning path and in your further development. While you are learning with our CCDS Quiz guide, we hope to help you make out what obstacles you have actually encountered during your approach for CCDS exam torrent through our PDF version, only in this way can we help you win the CCDS certification in your first attempt.
New CCDS Braindumps Files: https://www.bootcamppdf.com/CCDS_exam-dumps.html