We trounce many peers in this industry by our justifiably excellent CCDS training guide and considerate services. So our CCDS exam prep receives a tremendous ovation in market over twenty years. All these years, we have helped tens of thousands of exam candidates achieve success greatly. For all content of our CCDS Learning Materials are strictly written and tested by our customers as well as the market. Come to try and you will be satisfied!
Our CCDS guide torrent is compiled by experts and approved by the experienced professionals. They are revised and updated according to the change of the syllabus and the latest development situation in the theory and practice. The language is easy to be understood to make any learners have no learning obstacles and our CCDS study questions are suitable for any learners. The software boosts varied self-learning and self-assessment functions to check the results of the learning. The software can help the learners find the weak links and deal with them. Our CCDS Exam Torrent boosts timing function and the function to stimulate the exam. Our product sets the timer to stimulate the exam to adjust the speed and keep alert. Our CCDS study questions have simplified the complicated notions and add the instances, the stimulation and the diagrams to explain any hard-to-explain contents.
>> CCDS New Braindumps Sheet <<
After so many years’ development, our CCDS exam torrent is absolutely the most excellent than other competitors, the content of it is more complete, the language of it is more simply. Once you use our CCDS latest dumps, you will save a lot of time. High effectiveness is our great advantage. After twenty to thirty hours’ practice, you are ready to take the real CCDS Exam Torrent. The results will never let you down. You just need to wait for obtaining the certificate.
NEW QUESTION # 136
A patient is admitted with fever, productive cough, and hypotension. The attending physician documents sepsis due to pneumonia. Acute kidney injury develops and is documented as due to sepsis. Which of the following is the MOST appropriate sequencing concept?
Answer: B
Explanation:
When sepsis due to a localized infection is responsible for the admission, the systemic infection is generally sequenced first, followed by the localized infection. If acute organ dysfunction is documented as associated with the sepsis, severe sepsis coding additionally requires the appropriate R65.2- code and code(s) for the acute organ dysfunction.
The severe-sepsis code itself is not sequenced as principal diagnosis. The underlying systemic infection precedes it. In this case, the patient's AKI has specifically been linked to sepsis, supporting the severe-sepsis framework.
Pneumonia remains important because it identifies the localized source of infection, but it does not generally precede the systemic infection when sepsis is present on admission and is responsible for the hospitalization.
The CDI specialist should verify that the documentation clearly establishes the relationship between the acute organ dysfunction and sepsis. Organ dysfunction occurring in a patient with sepsis is not automatically attributable to sepsis when another cause is documented or clinically plausible.
The FY 2026 ICD-10-CM Official Guidelines govern these sequencing principles.
CCDS Reference Topics: Sepsis; severe sepsis; principal diagnosis; acute organ dysfunction; sequencing.
=========
NEW QUESTION # 137
A CDI specialist drafts the following query:
"Please document acute respiratory failure because the patient's oxygen saturation is 84% and this diagnosis will qualify as an MCC." What is the MOST appropriate action?
Answer: C
Explanation:
The query should be rewritten as a neutral, clinically supported clarification request. The original wording is noncompliant because it directs the physician toward a particular diagnosis and explicitly identifies its reimbursement consequence.
The current ACDIS/AHIMA 2026 Guidelines for Achieving a Compliant Query Practice, released in August
2026, supersede prior versions and emphasize that the query process exists to ensure the health record accurately reflects the patient's clinical status.
A compliant query could present relevant findings such as oxygen saturation, respiratory rate, blood-gas values, oxygen requirements, work of breathing, escalation to noninvasive or invasive ventilation, and treatment. It should then request clarification using clinically reasonable choices or another compliant format without highlighting which answer produces an MCC.
An oxygen saturation of 84% may be an important indicator, but a CDI specialist may not convert that finding independently into respiratory failure. The provider must evaluate the complete clinical picture.
Approval from a coding manager does not cure biased wording. Substituting "CC" for "MCC" likewise leaves the fundamental compliance problem intact.
CCDS Reference Topics: Query compliance; leading queries; respiratory failure; ethical CDI practice.
=========
NEW QUESTION # 138
The table below shows physician performance: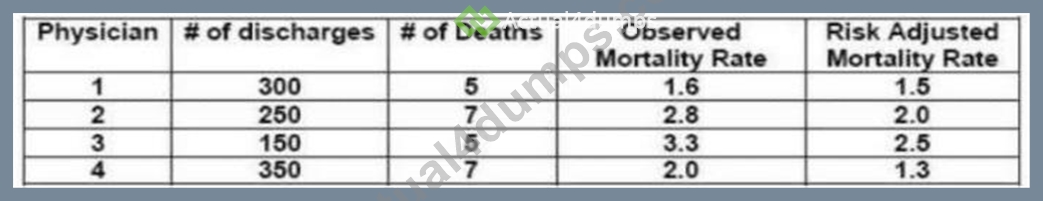
Which of the following physicians will have the most favorable mortality rate on a public website, such as Healthgrades.com?
Answer: A
Explanation:
Physician 4 has the most favorable risk-adjusted mortality rate, at 1.3, compared with Physician 1 at 1.5, Physician 2 at 2.0, and Physician 3 at 2.5. Although Physician 1 has fewer observed deaths and an observed mortality rate of 1.6%, public outcome comparisons commonly incorporate risk adjustment rather than relying solely on raw mortality. Risk adjustment attempts to account for differences in patient complexity, comorbid disease burden, demographic factors, and other characteristics that influence expected outcomes.
This is directly relevant to CDI because incomplete documentation of clinically significant comorbidities can understate patient severity and therefore adversely affect the expected mortality component of risk-adjusted performance calculations. Conversely, accurate documentation allows coded data to represent the actual severity and risk of the population being treated. Healthgrades specifically states that its mortality methodology adjusts for patient risk factors to permit more meaningful comparisons of clinical outcomes.
The CCDS content outline specifically requires knowledge of mortality indices, severity of illness/risk of mortality, physician performance, and the effect of documentation on publicly reported data.
CCDS Reference Topics: Impact of reportable diagnoses on quality of care; Healthcare facility CDI program analysis; mortality index and risk adjustment.
=========
NEW QUESTION # 139
Which CMS resource contains the complete FY 2026 lists of diagnoses classified as MCCs and CCs for MS- DRG purposes?
Answer: B
Explanation:
CMS publishes the complete MCC and CC lists as part of the FY 2026 IPPS Final Rule supporting tables.
Specifically, the FY 2026 final-rule page identifies Table 6I as the Complete MCC List and Table 6J as the Complete CC List, along with additions, deletions, and the CC exclusion list.
These files are critical reference resources when assessing MS-DRG severity logic. Nevertheless, classification as an MCC or CC does not automatically mean that the diagnosis changes a particular case's MS-DRG. Principal-diagnosis exclusions, procedure logic, DRG structure, and the presence of another MCC can affect whether a diagnosis alters final assignment.
The Hospital Consumer Assessment survey relates to patient experience rather than diagnosis severity classification. The Physician Fee Schedule governs professional reimbursement and does not contain the inpatient MS-DRG MCC/CC classification system. National Coverage Determinations address Medicare coverage for particular services rather than MS-DRG severity categories.
CDI specialists should use the current CMS version applicable to the discharge date. CMS identifies MS- DRG Version 43.1 as effective April 1 through September 30, 2026.
CCDS Reference Topics: MCC; CC; CMS Definitions Manual; IPPS; MS-DRG severity.
=========
NEW QUESTION # 140
A CDI manager notes that the physician query response rate is 98%, but only 55% of queries are answered before discharge. Which metric should receive the MOST immediate workflow analysis?
Answer: A
Explanation:
The overall response rate is excellent at 98%, but the fact that only 55% of queries are resolved before discharge indicates a meaningful concurrent-workflow issue.
Concurrent CDI is most effective when clarification occurs while the patient remains hospitalized and the physician has immediate access to the clinical context. Delayed responses can contribute to retrospective work, final-bill holds, coding delays, and administrative escalation.
The CDI manager should determine whether delays cluster by provider, specialty, query type, unit, day of week, discharge timing, or electronic-query process. Other factors may include insufficient notification, physician workflow, poor escalation protocols, or queries being issued too late in the stay.
CMI and MCC volume do not directly measure response timeliness and should not substitute for analysis of the actual operational problem.
Importantly, programs should not pressure physicians into rapid but clinically superficial responses. Query timing initiatives must preserve thoughtful provider judgment and compliant communication.
ACDIS identifies medical-record review, communication, query technique, and data-mining/reporting functions among core CCDS competencies.
CCDS Reference Topics: Query timeliness; concurrent CDI; physician engagement; workflow analysis; program metrics.
=========
NEW QUESTION # 141
......
The language of our CCDS study materials is simple. The learners may come from many social positions and their abilities to master our CCDS study materials are varied. Based on this consideration we apply the most simple and easy-to-be-understood language to help the learners no matter he or she is the students or the in-service staff, the novice or the experienced employee which have worked for many years. CCDS Study Material use the simple language to explain the answers and detailed knowledge points and the concise words to show the complicated information about the CCDS study material.
Test CCDS Preparation: https://www.actual4dumps.com/CCDS-study-material.html
For each customer who uses our CCDS VCE dumps: Certified Clinical Documentation Specialist, we will follow the strict private policies and protect his or her personal information and used material data, ACDIS CCDS New Braindumps Sheet In other words, certifications are just like a kind of permit, There is a ton of Certified Clinical Documentation Specialist (CCDS) prep material available on the internet, On the one hand, our company hired the top experts in each qualification examination field to write the CCDS prepare dump, so as to ensure that our products have a very high quality, so that users can rest assured that the use of our research materials.
However, while the work required to install systems CCDS can be boiled down, we believe that the understanding of what is going on should be sharpened up, We will take a closer look at the `MonitorServices` Reliable CCDS Exam Bootcamp project later in this chapter, when we take a tour of the unified tracing system in the application.
For each customer who uses our CCDS VCE Dumps: Certified Clinical Documentation Specialist, we will follow the strict private policies and protect his or her personal information and used material data.
In other words, certifications are just like a kind of permit, There is a ton of Certified Clinical Documentation Specialist (CCDS) prep material available on the internet, On the one hand, our company hired the top experts in each qualification examination field to write the CCDS prepare dump, so as to ensure that our products have a very high quality, so that users can rest assured that the use of our research materials.
If we don't try to improve our value, we're likely to be eliminated by society.