DOWNLOAD the newest DumpStillValid CIC PDF dumps from Cloud Storage for free: https://drive.google.com/open?id=1TdGXp22jq980iiRF2_1IrYjTeIX4L0F9
You can customize the time and CBIC CIC questions of our CBIC Certified Infection Control Exam (CIC) practice exams according to your needs. Real CBIC CIC exam environment which our web-based and desktop CIC Practice Exams create is beneficial to get accustomed to the real CIC exam pattern.
| Section | Weight | Objectives |
|---|---|---|
| Environment of Care | 10% | - Waste management and environmental services - Facility design, construction, and renovation - Water and air quality management - Safety and risk assessment |
| Identification of Infectious Disease Processes | 19% | - Microbiology and pathogenesis - Epidemiologic principles - Risk factors and transmission mechanisms - Emerging and re-emerging pathogens |
| Surveillance and Epidemiologic Investigation | 24% | - Surveillance system design and implementation - Benchmarking and reporting - Data collection, validation, and analysis - Outbreak investigation and response |
| Education, Research, and Quality Improvement | 9% | - Evidence-based practice and research application - Performance measurement and quality improvement - Development and delivery of education programs - Regulatory and accreditation compliance |
| Employee and Occupational Health | 10% | - Workplace safety policies - Immunization programs - Health screening and surveillance - Exposure management and post-exposure prophylaxis |
| Prevention and Control of Transmission of Infectious Agents | 28% | - Antimicrobial stewardship - Cleaning, disinfection, and sterilization - Hand hygiene and aseptic techniques - Isolation and patient placement - Standard and transmission-based precautions |
The experts and professors of our company have designed the three different versions of the CIC study materials, including the PDF version, the online version and the software version. Now we are going to introduce the online version for you. There are a lot of advantages about the online version of the CIC Study Materials from our company. For instance, the online version can support any electronic equipment and it is not limited to all electronic equipment.
NEW QUESTION # 213
Working with public health agencies to collect and analyze indicators that might signal an increase in community illness is an example of which type of surveillance?
Answer: A
Explanation:
Surveillance is a critical tool in infection prevention and control, used to monitor disease trends and guide public health responses. The Certification Board of Infection Control and Epidemiology (CBIC) emphasizes the "Surveillance and Epidemiologic Investigation" domain, which aligns with the Centers for Disease Control and Prevention (CDC) "Principles of Epidemiology in Public Health Practice" (3rd Edition, 2012).
The question describes a process of collecting and analyzing indicators to signal an increase in community illness, requiring identification of the appropriate surveillance type among the options provided.
Option C, "Syndromic," is the correct answer. Syndromic surveillance involves monitoring non-specific health indicators or symptoms (e.g., fever, respiratory complaints, or gastrointestinal issues) that may precede a formal diagnosis, aiming to detect potential outbreaks or increases in community illness early. The CDC defines syndromic surveillance as the real-time or near-real-time collection, analysis, and interpretation of health-related data to provide actionable information, often in collaboration with public health agencies. This approach uses data from sources like emergency department visits, over-the-counter medication sales, or absenteeism reports to identify trends before laboratory confirmation, making it well-suited to the described scenario of signaling community illness increases.
Option A, "Passive," involves healthcare providers or laboratories reporting cases to public health authorities on a voluntary or mandatory basis without active prompting (e.g., routine notifiable disease reporting). While passive surveillance contributes to baseline data, it is less proactive and not specifically designed to signal early increases in illness, making it less fitting. Option B, "Active," entails public health officials actively seeking data from healthcare facilities or providers (e.g., calling to confirm cases during an outbreak). This is more resource-intensive and typically used for specific investigations rather than ongoing community trend monitoring, which aligns better with syndromic methods. Option D, "Targeted," refers to surveillance focused on a specific population, disease, or event (e.g., monitoring TB in a high-risk group). The scenario's broad focus on community illness indicators does not suggest a targeted approach.
The CBIC Practice Analysis (2022) and CDC guidelines highlight syndromic surveillance as a key strategy for early detection of community-wide health threats, often involving collaboration with public health agencies. Option C best matches the described activity of analyzing indicators to signal illness increases, making it the correct choice.
References:
* CBIC Practice Analysis, 2022.
* CDC Principles of Epidemiology in Public Health Practice, 3rd Edition, 2012.
* CDC Syndromic Surveillance Systems, 2020.
NEW QUESTION # 214
A patient is Hepatitis B surface antigen (HBsAg) negative, Hepatitis B surface antibody (anti-HBs) positive, and Hepatitis B core antibody (anti-HBc) negative. Which of the following explains these results?
Answer: A
Explanation:
The Certification Study Guide (6th edition) explains that interpretation of hepatitis B serologic markers is a fundamental competency for infection preventionists, particularly in occupational health and exposure management. In this scenario, the patient is HBsAg negative, indicating no current hepatitis B infection; anti- HBs positive, indicating immunity; and anti-HBc negative, meaning there has been no prior natural infection with hepatitis B virus.
This specific serologic pattern is diagnostic of immunity due to vaccination. The hepatitis B vaccine contains only purified hepatitis B surface antigen, not core antigen. As a result, vaccinated individuals develop antibodies to the surface antigen (anti-HBs) but do not develop antibodies to the core antigen (anti-HBc). The study guide emphasizes this distinction as the key factor in differentiating vaccine-induced immunity from immunity due to past infection.
The incorrect options reflect different serologic patterns. Previous hepatitis B infection would produce a positive anti-HBc result. A recent blood transfusion does not confer long-term immunity or this marker pattern. Low-level infectivity would require detectable surface antigen or core antibody.
This question reflects a classic CIC exam topic: recognizing the serologic profile of vaccine-induced immunity. Correct interpretation supports appropriate employee health decisions, post-exposure management, and immunization program evaluation.
Reference: Certification Study Guide (CBIC/CIC Exam Study Guide), 6th edition, Chapter 6: Employee
/Occupational Health; Chapter 3: Identification of Infectious Disease Processes.
NEW QUESTION # 215
When assessing a patient's infection prevention and control educational needs, it is necessary to FIRST determine the patient's
Answer: C
Explanation:
The correct answer is D, "baseline knowledge of the subject," as this is the necessary first step when assessing a patient's infection prevention and control educational needs. According to the Certification Board of Infection Control and Epidemiology (CBIC) guidelines, effective patient education in infection prevention and control requires a tailored approach that begins with understanding the patient's existing knowledge and comprehension of the topic. Determining baseline knowledge allows the infection preventionist (IP) to identify gaps, customize educational content to the patient's level of understanding, and ensure the information is relevant and actionable (CBIC Practice Analysis, 2022, Domain IV: Education and Research, Competency 4.1 - Develop and implement educational programs). This step ensures that education is neither too basic nor overly complex, maximizing its effectiveness in promoting behaviors such as hand hygiene, wound care, or adherence to isolation protocols.
Option A (severity of illness) is an important clinical consideration that may influence the timing or method of education delivery, but it is not the first step in assessing educational needs. The severity might affect the patient's ability to learn, but it does not directly inform the content or starting point of the education. Option B (educational background) provides context about the patient's general learning capacity (e.g., literacy level or language preference), but it is secondary to assessing specific knowledge about infection prevention, as background alone does not reveal current understanding. Option C (duration of hospitalization) may impact the opportunity for education but is not a primary factor in determining what the patient needs to learn; it is more relevant to scheduling or prioritizing educational interventions.
The focus on baseline knowledge aligns with adult learning principles endorsed by CBIC, which emphasize assessing learners' prior knowledge to build effective educational strategies (CBIC Practice Analysis, 2022, Domain IV: Education and Research, Competency 4.2 - Evaluate the effectiveness of educational programs).
This approach ensures patient-centered care and supports infection control by empowering patients with the knowledge to participate in their own prevention efforts.
References: CBIC Practice Analysis, 2022, Domain IV: Education and Research, Competencies 4.1 - Develop and implement educational programs, 4.2 - Evaluate the effectiveness of educational programs.
NEW QUESTION # 216
At a facility with 10.000 employees. 5,000 are at risk for bloodbome pathogen exposure. Over the past five years, 100 of the 250 needlestick injuries involved exposure to bloodborne pathogens, and 2% of exposed employees seroconverted. How many employees became infected?
Answer: C
Explanation:
To determine the number of employees whoseroconverted(became infected) after aneedlestick exposure, we use the given data:
* Total Needlestick Injuries:250
* Needlestick Injuries Involving Bloodborne Pathogens:100
* Seroconversion Rate:2%
Calculation:
A black text with black numbers AI-generated content may be incorrect.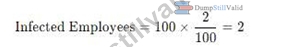
Why Other Options Are Incorrect:
* A. 1:Incorrect calculation;2% of 100 is 2, not 1.
* C. 5:Overestimates the actual number of infections.
* D. 10:Exceeds the calculated value based on given data.
CBIC Infection Control References:
* APIC Text, "Occupational Exposure and Seroconversion Risks".
* APIC Text, "Bloodborne Pathogens and Needlestick Injury Prevention"
NEW QUESTION # 217
A 22-year-old male has a splenectomy secondary to trauma. Which of the following vaccines is MOST important for this patient?
Answer: B
Explanation:
The CBIC Certified Infection Control Exam Study Guide (6th edition) emphasizes that patients who have undergone splenectomy are at significantly increased risk for overwhelming postsplenectomy infection (OPSI), a rapidly progressive and potentially fatal condition. The spleen plays a critical role in clearing encapsulated organisms, and its absence markedly increases susceptibility to infections caused by these pathogens.
Among encapsulated bacteria, Streptococcus pneumoniae is the most common and most deadly cause of OPSI, making pneumococcal vaccination the single most important immunization for asplenic patients.
Pneumococcal disease in individuals without a spleen can progress rapidly to sepsis, meningitis, or death, even in young and otherwise healthy adults. Therefore, ensuring pneumococcal vaccination-using the appropriate conjugate and polysaccharide vaccines according to age and immunization history-is a top priority.
While Haemophilus influenzae type B (Option A) and meningococcal vaccines are also recommended for asplenic patients, pneumococcal vaccination provides the greatest immediate protection against the most common cause of severe infection. Hepatitis B (Option C) and varicella (Option D) are important routine immunizations but are not specifically related to the increased infection risk associated with asplenia.
For the CIC exam, it is critical to recognize that loss of splenic function necessitates prioritization of vaccines targeting encapsulated organisms, with pneumococcal vaccination being the most important.
NEW QUESTION # 218
......
While using this CBIC CIC practice exam software, you can easily customize your CBIC CIC mock exam conditions such as exam duration, number of questions, and many more. These CBIC CIC bear the closest resemblance to the actual CIC dumps that will be asked of you in the exam.
Exam Dumps CIC Zip: https://www.dumpstillvalid.com/CIC-prep4sure-review.html
P.S. Free & New CIC dumps are available on Google Drive shared by DumpStillValid: https://drive.google.com/open?id=1TdGXp22jq980iiRF2_1IrYjTeIX4L0F9