P.S. Free & New EFM dumps are available on Google Drive shared by ActualTestsQuiz: https://drive.google.com/open?id=186VtWZG2xebfmY5rA2_wLGjzPpclh_-d
For more than ten years, our EFM practice engine is the best seller in the market. More importantly, our good EFM guide questions and perfect after sale service are approbated by our local and international customers. If you want to pass your practice exam, we believe that our EFM Learning Engine will be your indispensable choices. More and more people have bought our EFM guide questions in the past years. What are you waiting for? Just rush to buy our EFM exam braindumps and become successful!
| Section | Objectives |
|---|---|
| Topic 1: Uterine Activity | - Tachysystole and abnormal contraction patterns - Normal uterine contraction patterns |
| Topic 2: Fetal Heart Rate Interpretation | - Category I, II, and III tracing interpretation - Accelerations and decelerations - Baseline rate and variability |
| Topic 3: Intrapartum Assessment and Monitoring | - External and internal monitoring techniques - Risk assessment during labor |
| Topic 4: Fetal Physiology and Oxygenation | - Oxygen transport and acid-base balance - Fetal cardiovascular physiology |
| Topic 5: Intrauterine Resuscitation and Interventions | - Fluid management and medication adjustments - Maternal position changes and oxygen administration |
| Topic 6: Maternal and Fetal Complications | - Hypoxia and uteroplacental insufficiency - High-risk obstetric conditions affecting fetal monitoring |
We understand the difficulty of finding the latest and accurate EFM questions. In today's competitive world, it is essential to prepare with the most probable NCC in EFM exam dumps to stay ahead of the competition. That's why we have created our updated NCC EFM Questions, which will help you to clear the Certified - Electronic Fetal Monitoring (EFM) exam in one go.
NEW QUESTION # 88
During amnioinfusion, the infusion should be stopped periodically to assess changes in:
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
During amnioinfusion, NCC emphasizes monitoring for uterine overdistention, which can lead to uterine hypertonus, uterine rupture, or placental separation. The primary way to evaluate overdistention is by measuring baseline uterine pressure via IUPC.
* Rising resting tone (>20-25 mmHg) indicates accumulating fluid and risk.
* Stopping the infusion intermittently allows recalibration and assessment of uterine baseline pressure.
* Contraction pattern (option B) is important but not the primary safety parameter.
* Pain (option C) is nonspecific and not a reliable indicator of uterine overdistention.
Thus, the infusion is stopped to assess baseline uterine pressure.
References:NCC C-EFM Candidate Guide; AWHONN Fetal Heart Monitoring Principles & Practices; Miller' s Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring.
NEW QUESTION # 89
The fetal heart rate tracing shown represents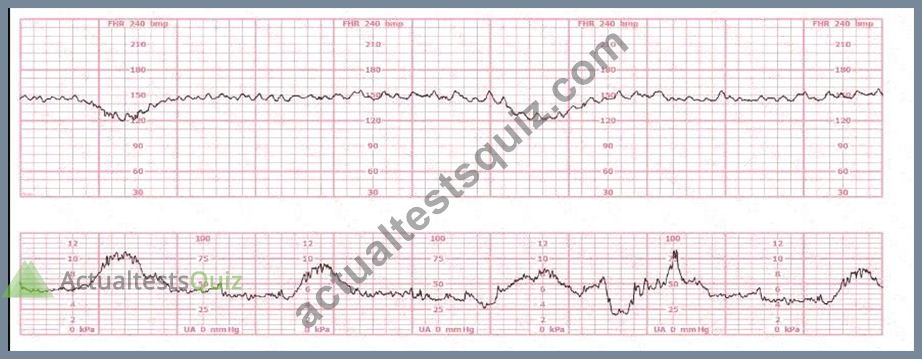
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources The tracing demonstrates a baseline within normal limits, moderate variability, and recurrent variable decelerations associated with contractions. According to NICHD/NCC definitions reproduced in AWHONN' s Fetal Heart Monitoring Principles & Practices and Menihan's Electronic Fetal Monitoring, recurrent variable decelerations with preserved variability classify the tracing as Category II.
A Category I pattern must show baseline 110-160, moderate variability, and absence of late or variable decelerations. Because this tracing shows recurrent variable decelerations, it does not meet Category I criteria.
Category III requires absent variability PLUS recurrent late decelerations, recurrent variable decelerations, bradycardia, or a sinusoidal pattern. This tracing shows moderate variability, therefore it cannot be Category III.
Simpson & Creehan emphasize that variable decelerations reflect cord compression and fall into Category II unless accompanied by absent variability. Miller's Pocket Guide confirms that moderate variability maintains fetal compensatory reserve, keeping the pattern in Category II.
References:
AWHONN - Fetal Heart Monitoring Principles & PracticesMenihan - Electronic Fetal MonitoringSimpson & Creehan - Perinatal NursingCreasy & Resnik - Maternal-Fetal MedicineMiller's Pocket Guide
NEW QUESTION # 90
An internal electronic fetal monitor tracing continues to record artifact despite equipment troubleshooting and replacement of the spiral electrode. The next action is to:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
When internal monitoring continues to record artifact despite:
* Changing the scalp electrode
* Ensuring correct attachment
* Checking cable connections
* Confirming maternal movement is not the cause
NCC requires confirmation of fetal well-being using another modality.
The correct next step is direct auscultation with Doppler or fetoscope.
Why other answers are incorrect:
* Oxygen is not indicated for equipment malfunction.
* Repositioning does not resolve internal FHR artifact.
Thus, Auscultate the fetal heart rate is the appropriate next step.
References:NCC C-EFM Candidate Guide; AWHONN; Miller's Pocket Guide; Menihan.
NEW QUESTION # 91
Interventions undertaken to address fetal tachycardia are targeted at maximizing
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources Fetal tachycardia is typically caused by maternal fever, dehydration, hypoxia, medications, infection, or fetal stress. AWHONN and Simpson & Creehan emphasize that management focuses on improving oxygen delivery across the placenta, which is governed by uteroplacental perfusion.
Menihan's EFM text states that "interventions for fetal tachycardia must address oxygen transfer by optimizing uteroplacental blood flow," including hydration, reducing uterine activity, maternal repositioning, and treating maternal fever.
Increasing maternal circulation alone is insufficient unless it improves placental blood flow. Enhancing fetal sympathetic tone is not a clinical goal and would worsen tachycardia.
Creasy & Resnik highlight that fetal heart rate abnormalities resolve when uteroplacental perfusion is restored, confirming this as the primary target of intervention.
References:
AWHONN - Fetal Heart Monitoring Principles & PracticesSimpson & Creehan - Perinatal NursingMenihan
- Electronic Fetal MonitoringCreasy & Resnik - Maternal-Fetal MedicineMiller's Pocket Guide
NEW QUESTION # 92
A woman reports 12 fetal movements over one hour. The best recommendation is to:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
NCC and AWHONN consider fetal movement counts normal when:
* #10 distinct movements occur within 2 hours
* Or #4 movements in 1 hour for certain protocols
* Or #10 movements in 1 hour (common triage threshold)
This patient reports 12 movements in 1 hour, which is reassuring and requires no further testing.
Thus, recommending she continue daily kick counts at home is appropriate.
Why the other options are incorrect:
* A. NST is not needed because movements are normal.
* B. Continue to monitor is unnecessary; the test is already reassuring.
Correct choice: C. Count again the next day.
References:NCC C-EFM Candidate Guide; AWHONN Fetal Assessment guidelines; Simpson & Creehan.
NEW QUESTION # 93
......
The software keeps track of the previous Certified - Electronic Fetal Monitoring (EFM) practice exam attempts and shows the changes of each attempt. You don't need to wait days or weeks to get your performance report. The software displays the result of the NCC EFM Practice Test immediately, which is an excellent way to understand which area needs more attention.
Prep EFM Guide: https://www.actualtestsquiz.com/EFM-test-torrent.html
BTW, DOWNLOAD part of ActualTestsQuiz EFM dumps from Cloud Storage: https://drive.google.com/open?id=186VtWZG2xebfmY5rA2_wLGjzPpclh_-d