2026 Latest GetValidTest CIC PDF Dumps and CIC Exam Engine Free Share: https://drive.google.com/open?id=19sLVRxNFPN3gaSxPtpkaliTNCfhys6N3
Many candidates who take the qualifying exams are not aware of our CIC exam questions and are not guided by our systematic guidance, and our users are much superior to them. In similar educational products, the CIC quiz guide is absolutely the most practical. Also, from an economic point of view, our CIC Exam Guide Materials is priced reasonable, so the CIC test material is very responsive to users, user satisfaction is also leading the same products. You can deeply depend on our CIC exam guide materials when you want to get the qualification.
| Section | Weight | Objectives |
|---|---|---|
| Topic 1: Identification of Infectious Disease Processes | 19% | - Microbiology and pathogenesis - Epidemiologic principles - Emerging and re-emerging pathogens - Risk factors and transmission mechanisms |
| Topic 2: Education, Research, and Quality Improvement | 9% | - Evidence-based practice and research application - Regulatory and accreditation compliance - Development and delivery of education programs - Performance measurement and quality improvement |
| Topic 3: Surveillance and Epidemiologic Investigation | 24% | - Data collection, validation, and analysis - Outbreak investigation and response - Benchmarking and reporting - Surveillance system design and implementation |
| Topic 4: Employee and Occupational Health | 10% | - Immunization programs - Workplace safety policies - Health screening and surveillance - Exposure management and post-exposure prophylaxis |
| Topic 5: Environment of Care | 10% | - Safety and risk assessment - Facility design, construction, and renovation - Waste management and environmental services - Water and air quality management |
| Topic 6: Prevention and Control of Transmission of Infectious Agents | 28% | - Hand hygiene and aseptic techniques - Standard and transmission-based precautions - Antimicrobial stewardship - Isolation and patient placement - Cleaning, disinfection, and sterilization |
>> CIC Passing Score Feedback <<
IT certification exam materials providers are increasing recently years so that you will feel confused while choosing CBIC CIC latest exam questions vce. Here is good news that GetValidTest dumps are updated and it is valid and latest. If you purchase dumps right now you can get the best discount and price. CIC Latest Exam Questions vce will be your best choice for your test. Wish you pass exam successfully with our products.
NEW QUESTION # 21
After defining and identifying cases in a possible cluster of infections, an infection preventionist should NEXT establish:
Answer: D
Explanation:
When investigating a possible cluster of infections, an infection preventionist (IP) follows a structured epidemiological approach to identify the cause and implement control measures. The Certification Board of Infection Control and Epidemiology (CBIC) outlines this process within the "Surveillance and Epidemiologic Investigation" domain, which aligns with the Centers for Disease Control and Prevention (CDC) guidelines for outbreak investigation. The steps typically include defining and identifying cases, formulating a hypothesis, testing the hypothesis, and implementing control measures. The question specifies the next step after defining and identifying cases, requiring an evaluation of the logical sequence.
Option C, "A hypothesis that will explain the majority of cases," is the next critical step. After confirming a cluster through case definition and identification (e.g., by time, place, and person), the IP should develop a working hypothesis to explain the observed pattern. This hypothesis might propose a common source (e.g., contaminated equipment), a mode of transmission (e.g., airborne), or a specific population at risk. The CDC's
"Principles of Epidemiology in Public Health Practice" (3rd Edition, 2012) emphasizes that formulating a hypothesis is essential to guide further investigation, such as identifying risk factors or environmental sources.
This step allows the IP to focus resources on testing the most plausible explanation before proceeding to detailed analysis or interventions.
Option A, "The route of transmission," is an important element of the investigation but typically follows hypothesis formulation. Determining the route (e.g., contact, droplet, or common vehicle) requires data collection and analysis to test the hypothesis, making it a subsequent step rather than the immediate next action. Option B, "An appropriate control group," is relevant for analytical studies (e.g., case-control studies) to compare exposed versus unexposed individuals, but this is part of hypothesis testing, which occurs after the hypothesis is established. Selecting a control group prematurely, without a hypothesis, lacks direction and efficiency. Option D, "Whether observed incidence exceeds expected incidence," is a preliminary step to define a cluster, often done during case identification using baseline data or statistical thresholds (e.g., exceeding the mean plus two standard deviations). Since the question assumes cases are already defined and identified, this step is complete, and the focus shifts to hypothesis development.
The CBIC Practice Analysis (2022) and CDC guidelines prioritize hypothesis formulation as the logical next step after case identification, enabling a targeted investigation. This approach ensures that the IP can efficiently address the cluster's cause, making Option C the correct answer.
References:
* CBIC Practice Analysis, 2022.
* CDC Principles of Epidemiology in Public Health Practice, 3rd Edition, 2012.
NEW QUESTION # 22
Which of the following should be included when designing a data collection form for surveillance?
Answer: B
Explanation:
The Certification Study Guide (6th edition) emphasizes that effective surveillance depends on the ability to calculate rates, not just counts. To calculate any infection rate, both a numerator (number of infection events) and a denominator (population at risk or time at risk) are required. Therefore, inclusion of denominator information is essential when designing a data collection form for surveillance.
Denominator data may include patient days, device days (e.g., central line days, ventilator days), number of procedures, or number of admissions-depending on the surveillance objective. Without denominator data, infection preventionists cannot calculate standardized rates, compare trends over time, or benchmark against national databases. The study guide clearly states that surveillance systems lacking denominator data produce incomplete and potentially misleading results.
The other options are either vague or inappropriate. While data collection forms should avoid unnecessary information, simply stating "only the information needed" does not address the critical requirement for denominator data. Collecting "as much information as possible" is discouraged because it increases workload, reduces data quality, and may compromise sustainability of surveillance programs. Medication history is not routinely required for most surveillance activities unless it is directly related to the infection being studied.
This question reflects a fundamental CIC exam principle: surveillance must be designed to support valid rate calculation and analysis. Including denominator information ensures that collected data are meaningful, actionable, and aligned with evidence-based infection prevention practices.
Reference: Certification Study Guide (CBIC/CIC Exam Study Guide), 6th edition, Chapter 4: Surveillance and Epidemiologic Investigation.
NEW QUESTION # 23
At a facility with 10.000 employees. 5,000 are at risk for bloodbome pathogen exposure. Over the past five years, 100 of the 250 needlestick injuries involved exposure to bloodborne pathogens, and 2% of exposed employees seroconverted. How many employees became infected?
Answer: B
Explanation:
To determine the number of employees who seroconverted (became infected) after a needlestick exposure, we use the given data:
* Total Needlestick Injuries: 250
* Needlestick Injuries Involving Bloodborne Pathogens: 100
* Seroconversion Rate: 2%
Calculation:
A black text with black numbers AI-generated content may be incorrect.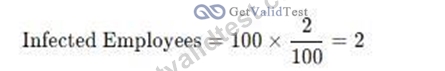
Why Other Options Are Incorrect:
* A. 1: Incorrect calculation; 2% of 100 is 2, not 1.
* C. 5: Overestimates the actual number of infections.
* D. 10: Exceeds the calculated value based on given data.
CBIC Infection Control References:
* APIC Text, "Occupational Exposure and Seroconversion Risks".
* APIC Text, "Bloodborne Pathogens and Needlestick Injury Prevention"
NEW QUESTION # 24
What rate is expressed by the number of patients who acquire infections over a specified time period divided by the population at risk of acquiring an infection during that time period?
Answer: D
Explanation:
The incidence rate measures new cases of infection in a population over a defined time period using the formula: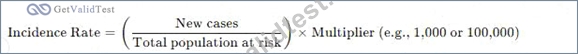
Why the Other Options Are Incorrect?
* B. Disease specific - Refers to infections caused by a particular pathogen, not the general rate of new infections.
* C. Point prevalence - Measures existing cases at a specific point in time, not new cases.
* D. Period prevalence - Includes both old and new cases over a set period, unlike incidence, which only considers new cases.
CBIC Infection Control Reference
APIC defines incidence rate as the number of new infections in a population over a given period.
NEW QUESTION # 25
The infection preventionist (IP) is assisting pharmacists in investigating medication contamination at the hospital's compounding pharmacy. As part of the medication recall process, the IP should:
Answer: C
Explanation:
The scenario involves an infection preventionist (IP) assisting pharmacists in addressing medication contamination at the hospital's compounding pharmacy, with a focus on the medication recall process. The IP' s role is to apply infection control expertise to mitigate risks, guided by the Certification Board of Infection Control and Epidemiology (CBIC) principles and best practices. The recall process requires a systematic approach to identify, contain, and resolve the issue, and the "first" or most critical step must be determined.
Let's evaluate each option:
* A. Have laboratory culture all medication: Culturing all medication to confirm contamination is a valuable step to identify affected batches and guide the recall. However, this is a resource-intensive process that depends on first understanding the scope and source of the problem. Without identifying the potential source of contamination, culturing all medication could be inefficient and delay the recall.
This step is important but secondary to initial investigation.
* B. Inspect for safe injection practices: Inspecting for safe injection practices (e.g., single-use vials, proper hand hygiene, sterile technique) is a critical infection control measure, especially in compounding pharmacies where contamination often arises from procedural errors (e.g., reuse of syringes, improper cleaning). While this is a proactive step to prevent future contamination, it addresses ongoing practices rather than the immediate recall process for the current contamination event. It is a complementary action but not the first priority.
* C. Identify the potential source of contamination: Identifying the potential source of contamination is the foundational step in the recall process. This involves investigating the compounding environment (e.
g., water quality, equipment, personnel practices), raw materials, and production processes to pinpoint where the contamination occurred (e.g., bacterial ingress, cross-contamination). The CBIC emphasizes root cause analysis as a key infection prevention strategy, enabling targeted recalls, corrective actions, and prevention of recurrence. This step is essential before culturing, inspecting, or notifying patients, making it the IP's primary responsibility in this context.
* D. Inform all discharged patients of potential medication contamination: Notifying patients is a critical step to ensure public safety and allow for medical follow-up if they received contaminated medication.
However, this action requires prior identification of the contaminated batches and their distribution, which depends on determining the source and confirming the extent of the issue. Premature notification without evidence could cause unnecessary alarm and is not the first step in the recall process.
The best answer is C, as identifying the potential source of contamination is the initial and most critical step in the medication recall process. This allows the IP to collaborate with pharmacists to trace the contamination, define the affected products, and guide subsequent actions (e.g., culturing, inspections, notifications). This aligns with CBIC's focus on systematic investigation and risk mitigation in healthcare-associated infection events.
CBIC Infection Prevention and Control (IPC) Core Competency Model (updated 2023), Domain III:
Prevention and Control of Infectious Diseases, which includes identifying sources of contamination in healthcare settings.
CBIC Examination Content Outline, Domain V: Management and Communication, which emphasizes root cause analysis during outbreak investigations.
CDC Guidelines for Safe Medication Compounding (2022), which recommend identifying contamination sources as the first step in a recall process.
NEW QUESTION # 26
......
To let the client be familiar with the atmosphere of the CIC exam we provide the function to stimulate the exam and the timing function of our study materials to adjust your speed to answer the questions. We provide the stimulation, the instances and the diagrams to explain the hard-to-understand contents of our CIC Study Materials. For these great merits we can promise to you that if you buy our CIC study materials you will pass the test with few difficulties.
CIC Dumps Torrent: https://www.getvalidtest.com/CIC-exam.html
P.S. Free 2026 CBIC CIC dumps are available on Google Drive shared by GetValidTest: https://drive.google.com/open?id=19sLVRxNFPN3gaSxPtpkaliTNCfhys6N3