BONUS!!! Download part of ActualTestsQuiz VTNE dumps for free: https://drive.google.com/open?id=1NaVT3OCgIhF1PYg_71rUclwE5IAKfh6J
ActualTestsQuiz's braindumps provide you the gist of the entire syllabus in a specific set of questions and answers. These study questions are most likely to appear in the actual VTNE exam. The Certification exams are actually set randomly from the database of VTNE. Thus most of the questions are repeated in exams and our experts after studying the previous exam have sorted out the most important questions and prepared dumps out of them. Hence VTNE Dumps are a special feast for all the exam takers and sure to bring them not only VTNE exam success but also maximum score.
| Section | Objectives |
|---|---|
| Topic 1: Pain Management and Analgesia | - Pain assessment techniques - Analgesic drug use |
| Topic 2: Diagnostic Imaging | - Image processing and interpretation basics - Radiography positioning and safety |
| Topic 3: Surgical Nursing | - Preoperative and postoperative care - Sterile technique and instrumentation |
| Topic 4: Animal Care and Nursing | - Nutrition and husbandry - Patient handling and restraint |
| Topic 5: Anesthesia | - Anesthetic protocols and equipment - Anesthetic monitoring |
| Topic 6: Laboratory Procedures | - Urinalysis and microbiology - Hematology and clinical pathology |
| Topic 7: Emergency Medicine and Critical Care | - Triage and stabilization - Shock management and CPR |
| Topic 8: Pharmacology | - Dosage calculations and administration - Drug classifications and uses |
| Topic 9: Dentistry | - Oral anatomy and disease recognition - Dental prophylaxis procedures |
>> VTNE Latest Braindumps Book <<
Our product’s passing rate is 99% which means that you almost can pass the test with no doubts. The reasons why our VTNE study materials’ passing rate is so high are varied. Firstly, our test bank includes two forms and they are the PDF test questions which are selected by the senior lecturer, published authors and professional experts and the practice test software which can test your mastery degree of our VTNE Study Materials at any time. The two forms cover the syllabus of the entire test. Our questions and answers include all the questions which may appear in the exam and all the approaches to answer the questions. So we provide the strong backing to help clients to help them pass the test.
NEW QUESTION # 1173
You are being asked to prep a patient for a gastrotomy. It is a 14-year-old MN DSH with a history of chronic vomiting. A linear foreign body is suspected as mild plication was evident on radiographs. The owners elected to forgo ultrasound to confirm and elected exploratory laparotomy. They gave permission for biopsies of the stomach and other areas as needed. This is the first time the cat has eaten anything he shouldn't, and the surgeon and admitting emergency clinician are highly suspicious of gastric neoplasia or other intestinal neoplasia triggering pica.
All the following neoplastic conditions occur gastrically in dogs and cats, except:
Answer: D
Explanation:
The mast cell tumor is the most common dermatological skin tumor seen in dogs, representing 16-19% of all canine dermatological tumors. Skin lesions are most common, but internal disease is also possible. More commonly, we have concerns about GI ulceration secondary to mast cell degranulation, leading to the release of histamine and other ulcerogenic factors in dogs and cats.
In cats, mast cell tumors are the second most commonly seen skin tumor. They can also obtain systemic disease, leukemic forms, GI manifestations, and primary splenic mast cell disease. GI/gastric disease, however, is rare, especially compared to the other types of gastric neoplasms seen.
Gastric tumors, in general, are uncommon in dogs or cats. Gastric tumors represent < 1% of all neoplasia in the species. The most common gastric neoplasias in dogs and cats are malignant adenocarcinomas, lymphosarcomas, leiomyosarcomas, or benign leiomyomas.
NEW QUESTION # 1174
What is the medical term for the bottom/lower jaw?
Answer: A
Explanation:
The mandible is formed from two bones that form the horseshoe-shaped lower jaw. The caudal mandibles articulate with the temporal bones of the skull at the temporomandibular joint. Rostrally, the two bones are joined by a cartilaginous joint called the mandibular symphysis.
The maxilla is composed of numerous bones that form the upper jaw and palate.
The bullae (also called tympanic bullae) are hollow bone structures found on the caudoventral skull and enclose portions of the middle and inner ear.
The zygomatic arches form part of the orbits for the eyes and are easily palpable as the "cheekbones."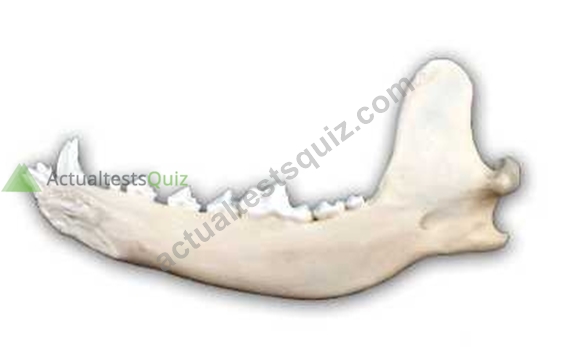
Clinical Anatomy and Physiology for Veterinary Technicians 3rd Edition. Pg 184-187.
NEW QUESTION # 1175
A horse handler brings in an 18-year-old gelding for evaluation. He reports that the horse has been showing intermittent yet progressive lameness. He is still eating and otherwise himself, but the trainer is concerned. You ask the handler if he has noticed any stumbling or a shortened stride, and he replies affirmatively. You recognize from your short interactions with the horse while getting your TPR and talking with the handler that the horse is intermittently shifting his weight off his heels on the right hind. You are suspicious of navicular disease in this horse.
Navicular disease describes a syndrome that can include all of the following, except:
Answer: A
Explanation:
Navicular disease syndrome has many underlying potential contributing factors and is likely multifactorial. Causes can include
*Damage to the navicular bone (distal sesamoid bone)
*Damage to the bone supply of the heel
*Damage to bursa, tendons, and ligaments attached to the navicular bone
*Underrun heels
*Low heel or long toe type confirmation (hoof wall angle is lower than that of the pastern) Contracted heels become a consequence of the disease over time. Contracted heels is a narrowing between the common meeting point of the fleshy part of the hoof wall, the heel, and the coronary band.
Regardless of the underlying cause(s), the net result is that the animal's weight shifts to take the pressure off the heel. This ultimately causes a gait change and may lead to secondary sequelae. The bone ultimately undergoes painful changes and degeneration over time. The disease syndrome is manageable but not curable.
Diagnosis can be a combination of various tests, including:
*Pain response with hoof testers over the foot's sole (pull the foot away)
*Flexion tests
*Nerve blocks
*Radiographs
*MRI
NEW QUESTION # 1176
Which of the following medications would not be beneficial in treating a post-operative patient with signs of either dysphoria or emergence delirium?
Answer: D
Explanation:
Emergence delirium occurs as patients are recovering during the post-operative period as a result of the gas anesthetic. This behavior is very transient and usually resolves within the first few minutes post anesthetic recovery, thus, requiring no intervention.
Dysphoria describes a patient demonstrating signs of anxiety, stress, agitation, depression, or unease that is not attributable to pain. The most common causes of this behavior include medication-related changes. Often, opioids are most commonly associated with dysphoric behavior in veterinary patients. Animals may act dysphoric either because the pain med dose was too high, or they can be nauseated or restless from the medication. However, other factors may play a role, which can happen with drugs other than opioids.
Deciphering whether a patient is painful vs. dysphoric can be difficult. But if evaluations of pain such as palpation at the incision site or other known previously painful areas produce no pain, the patient is not mentally appropriate or reacts inappropriately to normal stimuli, this must be considered. We do not want to administer additional pain meds until this is ruled out. Thus, the pure µ opioid agonist hydromorphone would not be an appropriate choice. Most patients already have an opioid on board, especially when hospitalized post-surgically or for a painful condition such as pancreatitis, parvovirus, or others. Pure opioid agonists commonly can lead to dysphoria, especially in older patients and patients with increased anxiety prior to surgery. Patients with underlying medical conditions may also be more prone to this reaction. Thus, it would not be an appropriate first choice.
Valium or midazolam are benzodiazepines and, as anxiolytics, may help remove any anxiety component to the behavior. However, it will not reverse the negative effects of any opioids on board. If the procedure was relatively short, it might be additive with any previously used Benzodiazepines. However, in low doses and with monitoring, it can be beneficial.
Butorphanol is an opioid agonist-antagonist with sedative properties. We commonly use this to help with anxiety and calm patients down, for example, those in respiratory distress. It has mild pain management properties, though short-lived vs. sedative properties. It may partially reverse any pure µ opioid agonists on board, thus, minimizing the dysphoria while maintaining some pain management.
Finally, if an opioid was used intraoperatively and one is concerned that the patient is not adequately metabolizing it, the patient is not responding to other treatments, or as a first-line, naloxone is the true reversal (antagonist) for pure µ opioid agonists such as fentanyl, hydromorphone, and morphine. Thus, it should be considered. Even patients who had no surgical procedure but received opioids may benefit from this medication. However, note that while it will immediately remove the drug, it is short-acting. We commonly see patients "re-narc," meaning that the opioid will reattach to the receptors once naloxone is out of the system. So care must be taken, and patients should be monitored closely. Often, giving one dose is sufficient to remove the dysphoria. Because enough drug remains, they then have adequate pain management once it is metabolized.
NEW QUESTION # 1177
What is alopecia?
Answer: A
Explanation:
Alopecia refers to partial or complete baldness in areas that should have hair. Alopecia is rarely a primary problem and is usually a clinical sign of a greater underlying illness.
Alopecia does not refer to scaling or flaking skin, severe redness and contact irritation, or abrasions caused by self-trauma.
NEW QUESTION # 1178
......
The VTNE prep torrent we provide will cost you less time and energy. You only need relatively little time to review and prepare. After all, many people who prepare for the VTNE exam, either the office workers or the students, are all busy. But the VTNE test prep we provide are compiled elaborately and it makes you use less time and energy to learn and provide the VTNE Study Materials of high quality and seizes the focus the VTNE exam. It lets you master the most information and costs you the least time and energy.
VTNE Latest Test Report: https://www.actualtestsquiz.com/VTNE-test-torrent.html
BONUS!!! Download part of ActualTestsQuiz VTNE dumps for free: https://drive.google.com/open?id=1NaVT3OCgIhF1PYg_71rUclwE5IAKfh6J