DOWNLOAD the newest PDFDumps CIC PDF dumps from Cloud Storage for free: https://drive.google.com/open?id=1_4h8rSo3SMH4DLQsllsJDirmDCQlEDn8
Nowadays the competition in the society is fiercer and if you don’t have a specialty you can’t occupy an advantageous position in the competition and may be weeded out. Passing the CBIC Certified Infection Control Exam test certification can help you be competent in some area and gain the competition advantages in the labor market. If you buy our CIC Study Materials you will pass the test smoothly. With a high pass rate as 98% to 100%, you will know that our CIC practice engine can provide you with the best pass percentage.
| Section | Weight | Objectives |
|---|---|---|
| Employee/Occupational Health | 10-13% | |
| Preventing/Controlling the Transmission of Infectious Agents | 17-19% | |
| Surveillance and Epidemiologic Investigation | 22-26% | |
| Education and Research | 6-9% | |
| Cleaning, Sterilization, Disinfection, Asepsis | 10-13% | |
| Environment of Care | 10-13% | |
| Identification of Infectious Disease Processes | 17-19% | |
| Management and Communication | 10-13% |
Nowadays everyone is interested in the field of CBIC because it is growing rapidly day by day. The CBIC Certified Infection Control Exam (CIC) credential is designed to validate the expertise of candidates. But most of the students are confused about the right preparation material for CIC Exam Dumps and they couldn't find real CIC exam questions so that they can pass CBIC CIC certification exam in a short time with good grades.
NEW QUESTION # 184
There are four cases of ventilator-associated pneumonia in a surgical intensive care unit with a total of 200 ventilator days and a census of 12 patients. Which of the following BEST expresses how this should be reported?
Answer: A
Explanation:
The standard way to reportventilator-associated pneumonia (VAP) ratesis:
A white paper with black text AI-generated content may be incorrect.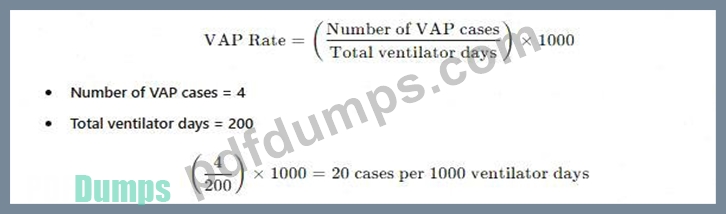
Why the Other Options Are Incorrect?
* A. Ventilator-associated pneumonia rate of 2%- This does not use thecorrect denominator (ventilator days).
* C. Postoperative pneumonia rate of 6% in SICU patients-Not relevant, as the data focuses onVAP, not postoperative pneumonia.
* D. More information is needed regarding ventilator days per patient-The total ventilator days are already provided, so no additional data is required.
CBIC Infection Control Reference
APIC and NHSN recommend reporting VAP rates as cases per 1,000 ventilator days.
NEW QUESTION # 185
The degree of infectiousness of a patient with tuberculosis correlates with
Answer: D
Explanation:
The infectiousness of tuberculosis (TB) is directly related to the number of Mycobacterium tuberculosis organisms expelled into the air by an infected patient.
Step-by-Step Justification:
* TB Transmission Mechanism:
* TB spreads through airborne droplet nuclei, which remain suspended for long periods.
* Factors Affecting Infectiousness:
* High bacterial load in sputum: Smear-positive patients are much more infectious.
* Coughing and sneezing frequency: More expelled droplets increase exposure risk.
* Environmental factors: Poor ventilation increases transmission.
Why Other Options Are Incorrect:
* A. Hand hygiene habits: TB is airborne, not transmitted via hands.
* B. Presence of acid-fast bacilli (AFB) in blood: TB is not typically hematogenous, and blood AFB does not correlate with infectiousness.
* C. Tuberculin skin test (TST) >20 mm: TST indicates prior exposure, not infectiousness.
CBIC Infection Control References:
* APIC Text, "Tuberculosis Transmission and Control Measures".
NEW QUESTION # 186
What question would be appropriate for an infection preventionist to ask when reviewing the discussion section of an original article?
Answer: A
Explanation:
When reviewing the discussion section of an original article, an infection preventionist must focus on critically evaluating the interpretation of the study findings, their relevance to infection control, and their implications for practice. The discussion section typically addresses the meaning of the results, compares them to existing literature, and considers limitations or alternative interpretations. The appropriate question should align with the purpose of this section and reflect the infection preventionist's need to assess the validity and applicability of the research. Let's analyze each option:
* A. Was the correct sample size and analysis method chosen?: This question pertains to the methodology section of a research article, where the study design, sample size, and statistical methods are detailed.
While these elements are critical for assessing the study's rigor, they are not the primary focus of the discussion section, which interprets results rather than re-evaluating the study design. An infection preventionist might ask this during a review of the methods section, but it is less relevant here.
* B. Could alternative explanations account for the observed results?: The discussion section often explores whether the findings can be explained by factors other than the hypothesized cause, such as confounding variables, bias, or chance. This question is highly appropriate for an infection preventionist, as it encourages a critical assessment of whether the results truly support infection control interventions or if other factors (e.g., environmental conditions, patient factors) might be responsible.
This aligns with CBIC's emphasis on evidence-based practice, where understanding the robustness of conclusions is key to applying research to infection prevention strategies.
* C. Is the study question important, appropriate, and stated clearly?: This question relates to the introduction or background section of an article, where the research question and its significance are established. While important for overall study evaluation, it is not specific to the discussion section, which focuses on interpreting results rather than revisiting the initial question. An infection preventionist might consider this earlier in the review process, but it does not fit the context of the discussion section.
* D. Are criteria used to measure the exposure and the outcome explicit?: This question is relevant to the methods section, where the definitions and measurement tools for exposures (e.g., a specific intervention) and outcomes (e.g., infection rates) are described. The discussion section may reference these criteria but focuses more on their implications rather than their clarity. This makes it less appropriate for the discussion section specifically.
The discussion section is where authors synthesize their findings, address limitations, and consider alternative explanations, making option B the most fitting. For an infection preventionist, evaluating alternative explanations is crucial to ensure that recommended practices (e.g., hand hygiene protocols or sterilization techniques) are based on solid evidence and not confounded by unaddressed variables. This critical thinking is consistent with CBIC's focus on applying research to improve infection control outcomes.
References:
* CBIC Infection Prevention and Control (IPC) Core Competency Model (updated 2023), Domain I:
Identification of Infectious Disease Processes, which emphasizes critical evaluation of research evidence.
* CBIC Examination Content Outline, Domain V: Management and Communication, which includes assessing the validity of research findings for infection control decision-making.
NEW QUESTION # 187
An infection preventionist (IP) is notified that a patient who underwent an endoscopic brain biopsy the night before has been diagnosed with prion disease. Because the diagnosis was thought to be unlikely but possible at the time of the biopsy, the endoscope was sequestered. The endoscope manufacturer's instructions for reprocessing indicate that the endoscope can be reprocessed using high-level disinfection or low-temperature sterilization. The IP should recommend that the endoscope be:
Answer: C
Explanation:
The CBIC Certified Infection Control Exam Study Guide (6th edition) identifies prion diseases (such as Creutzfeldt-Jakob disease) as unique and extremely challenging from an infection prevention standpoint due to the extraordinary resistance of prions to conventional disinfection and sterilization methods. Prions are not destroyed by standard high-level disinfection, low-temperature sterilization, ethylene oxide, or hydrogen peroxide gas plasma, even when manufacturer instructions for use suggest these methods for routine pathogens.
Invasive neurologic procedures involving high-risk tissues (brain, spinal cord, posterior eye) pose the greatest transmission risk. When a reusable device such as an endoscope is used on high-risk tissue in a patient with known or suspected prion disease, and the device cannot tolerate validated prion-inactivation protocols, the Study Guide recommends removal from service and disposal.
While harsh chemical treatments such as 1N sodium hydroxide or high-concentration bleach combined with extended steam sterilization may be effective for heat-resistant surgical instruments, flexible endoscopes and similar devices cannot safely undergo these processes without damage. Therefore, reprocessing is not acceptable in this scenario.
Autoclaving alone and low-temperature sterilization methods are ineffective against prions. As a result, the safest and recommended action is to bag the device as biohazardous waste and discard it, preventing any risk of iatrogenic transmission.
For the CIC exam, this question tests recognition that manufacturer IFUs do not supersede prion-specific infection prevention guidance, and patient safety requires device destruction when prion exposure cannot be reliably mitigated.
NEW QUESTION # 188
Respiratory tract flora are BEST characterized by which of the following statements?
Answer: B
Explanation:
The respiratory tract flora refers to the microbial communities inhabiting the respiratory system, and understanding their distribution is essential for infection prevention and diagnosis. The Certification Board of Infection Control and Epidemiology (CBIC) highlights the importance of microbial ecology in the
"Identification of Infectious Disease Processes" domain, which aligns with the Centers for Disease Control and Prevention (CDC) and clinical microbiology principles. The question seeks the best characterization of respiratory tract flora, requiring an evaluation of current scientific understanding.
Option C, "Both the upper and lower airways contain small numbers of organisms," is the most accurate statement. The upper respiratory tract (e.g., nasal passages, pharynx) is naturally colonized by a diverse microbial community, including bacteria like Streptococcus, Staphylococcus, and Corynebacterium, as well as some fungi and viruses, acting as a first line of defense. The lower respiratory tract (e.g., trachea, bronchi, alveoli) was traditionally considered sterile due to mucociliary clearance and immune mechanisms. However, recent advances in molecular techniques (e.g., 16S rRNA sequencing) have revealed a low-biomass microbiome in the healthy lower airway, consisting of small numbers of organisms such as Prevotella and Veillonella, likely introduced via microaspiration from the upper tract. The CDC and studies in journals like the American Journal of Respiratory and Critical Care Medicine (e.g., Dickson et al., 2016) support this view, indicating that both regions contain microbial populations, though the lower airway's flora is less dense and more tightly regulated.
Option A, "The airway is sterile below the larynx," is outdated. While the lower airway was once thought to be sterile, modern research shows a sparse microbial presence, debunking this as a complete characterization.
Option B, "Both the upper and lower airways are sterile throughout," is incorrect. The upper airway is clearly colonized, and the lower airway, though low in microbial load, is not entirely sterile. Option D, "The upper airway is heavily colonized while the lower airway is not," overstates the contrast. The upper airway is indeed heavily colonized, but the lower airway is not sterile; it contains small numbers of organisms rather than being completely free of microbes.
The CBIC Practice Analysis (2022) and CDC guidelines on respiratory infections acknowledge the evolving understanding of respiratory flora, emphasizing that both upper and lower airways host small microbial populations in healthy individuals. Option C best reflects this balanced and evidence-based characterization.
References:
* CBIC Practice Analysis, 2022.
* Dickson, R. P., et al. (2016). The Microbiome and the Respiratory Tract. American Journal of Respiratory and Critical Care Medicine.
* CDC Principles of Epidemiology, 3rd Edition, 2012.
NEW QUESTION # 189
......
The price of our CIC learning guide is among the range which you can afford and after you use our CIC study materials you will certainly feel that the value of the CIC exam questions far exceed the amount of the money you pay for the pass rate of our practice quiz is 98% to 100% which is unmarched in the market. Choosing our CIC Study Guide equals choosing the success and the perfect service.
CIC Latest Dumps: https://www.pdfdumps.com/CIC-valid-exam.html
BTW, DOWNLOAD part of PDFDumps CIC dumps from Cloud Storage: https://drive.google.com/open?id=1_4h8rSo3SMH4DLQsllsJDirmDCQlEDn8