P.S. Free & New EFM dumps are available on Google Drive shared by DumpsKing: https://drive.google.com/open?id=1XKK7hK2jzQabh9gNlwtWd_qCui0N_L77
You might have seen lots of advertisements about EFM learning question, there are so many types of EFM exam material in the market, why you should choose us? Our reasons are as follow. Our EFM test guide is test-oriented, which makes the preparation become highly efficient. Once you purchase our EFM exam material, your time and energy will reach a maximum utilization. Thus at that time, you would not need to afraid of the cruel society and peer pressure with EFM Certification. In conclusion, a career enables you to live a fuller and safer life. So if you want to take an upper hand and get a well-pleasing career our EFM learning question would be your best friend.
| Section | Weight | Objectives |
|---|---|---|
| Topic 1: Professional Issues | 5% | - Clinical Practice and Safety
|
| Topic 2: Physiology | 11% | - Maternal-Fetal Physiology
|
| Topic 3: Fetal Assessment Methods | 9% | - Assessment Techniques
|
| Topic 4: Pattern Recognition and Intervention | 70% | - Fetal Heart Rate Patterns
|
| Topic 5: Electronic Monitoring Equipment | 5% | - Monitoring Systems
|
High as 98 to 100 percent of exam candidates pass the exam after refer to the help of our EFM practice braindumps. So EFM study guide is high-effective, high accurate to succeed. That is the reason why we make it without many sales tactics to promote our EFM Learning Materials, their brand is good enough to stand out in the market. Download our EFM training prep as soon as possible and you can begin your review quickly.
NEW QUESTION # 118
A pattern of recurrent variable decelerations would move from Category II to Category III if what fetal heart rate change occurs?
Answer: C
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
Category III criteria include:
* Absent variability with recurrent variable decelerations
* Absent variability with recurrent lates
* Absent variability with bradycardia
* Sinusoidal pattern
Thus, recurrent variables become Category III when accompanied by absent variability, indicating fetal decompensation.
Why the other answers are wrong:
* B. Late decelerations # Category III only if combined with absent variability.
* C. Tachysystole # Contraction pattern, not a FHR characteristic.
Correct answer: Absent variability.
References:NCC C-EFM Candidate Guide; NICHD Definitions; AWHONN FHMPP.
NEW QUESTION # 119
Maternal-fetal oxygen transfer takes place in the:
Answer: C
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Physiologic Sources:
Oxygen transfer occurs at the maternal-fetal interface within the intervillous space, where:
* Maternal blood from the spiral arteries bathes the chorionic villi
* Diffusion occurs between maternal blood and fetal capillary beds
* Oxygen then travels through fetal circulation via the umbilical vein
Thus:
* Intervillous space = site of gas exchange
* Spiral arteries = deliver maternal blood to that space
* Umbilical vein = fetal vessel carrying oxygenated blood after exchange has occurred Correct answer: A. Intervillous space References:NCC Physiology Domain; AWHONN FHMPP; Creasy & Resnik; Simpson & Creehan.
NEW QUESTION # 120
The pattern on the fetal heart rate tracing shown is likely due to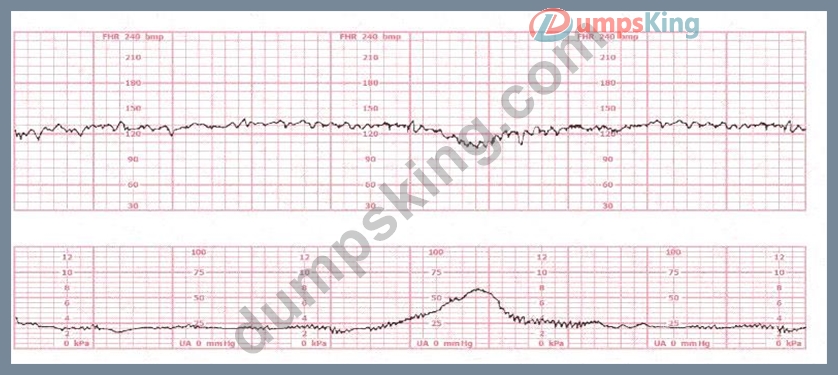
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract Sources:
The tracing demonstrates an abrupt-onset, sharp, V-shaped deceleration, occurring simultaneously with or slightly after a contraction-classic for variable decelerations, which are caused by umbilical cord compression.
According to AWHONN Fetal Heart Monitoring Principles & Practices, variable decelerations are defined by:
* "Abrupt decreases in FHR below baseline of at least 15 bpm, lasting at least 15 seconds and less than 2 minutes."
* "Most commonly associated with umbilical cord compression, whether transient or recurrent." Physiology reference (Simpson & Miller, Pocket Guide):
* Compression of the umbilical vein causes a brief acceleration.
* Compression of the umbilical arteries triggers a vagal response, producing a rapid deceleration.
* This creates the characteristic sharp 'V', 'U', or 'W' shape on the monitor.
Placental insufficiency (Choice B) produces late decelerations, which are gradual, not abrupt.
Fetal head compression (Choice A) produces early decelerations, which mirror contractions and have a gradual pattern.
Thus, the tracing is most consistent with variable decelerations caused by umbilical cord compression.
References:AWHONN Fetal Heart Monitoring Principles & Practices;Simpson - Fetal Monitoring;Menihan
- Electronic Fetal Monitoring;Miller's EFM Pocket Guide;NCC C-EFM Content Outline - Pattern Recognition Domain.
NEW QUESTION # 121
Interventions to decrease uterine activity should take place:
Answer: C
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
Tachysystole = >5 contractions in 10 minutes averaged over 30 minutes (NICHD).
However, NCC and AWHONN intervention guidelines state:
* If tachysystole appears in one or two consecutive 10-minute segments, especially with Category II or III patterns, intervention must begin immediately.
* Intervention includes:
* Stopping/reducing oxytocin
* Maternal repositioning
* IV bolus
* Tocolysis if needed
Why the wrong answers are wrong:
* A. Waiting 30 minutes delays necessary fetal resuscitation.
* C. Stage of labor does not determine when to intervene.
Correct answer: B. If tachysystole is seen for one or two 10-minute segments References:NCC C-EFM Candidate Guide; AWHONN FHMPP; Menihan.
NEW QUESTION # 122
A 45-year-old woman at 36-weeks gestation presents for a nonstress test. Vital signs are: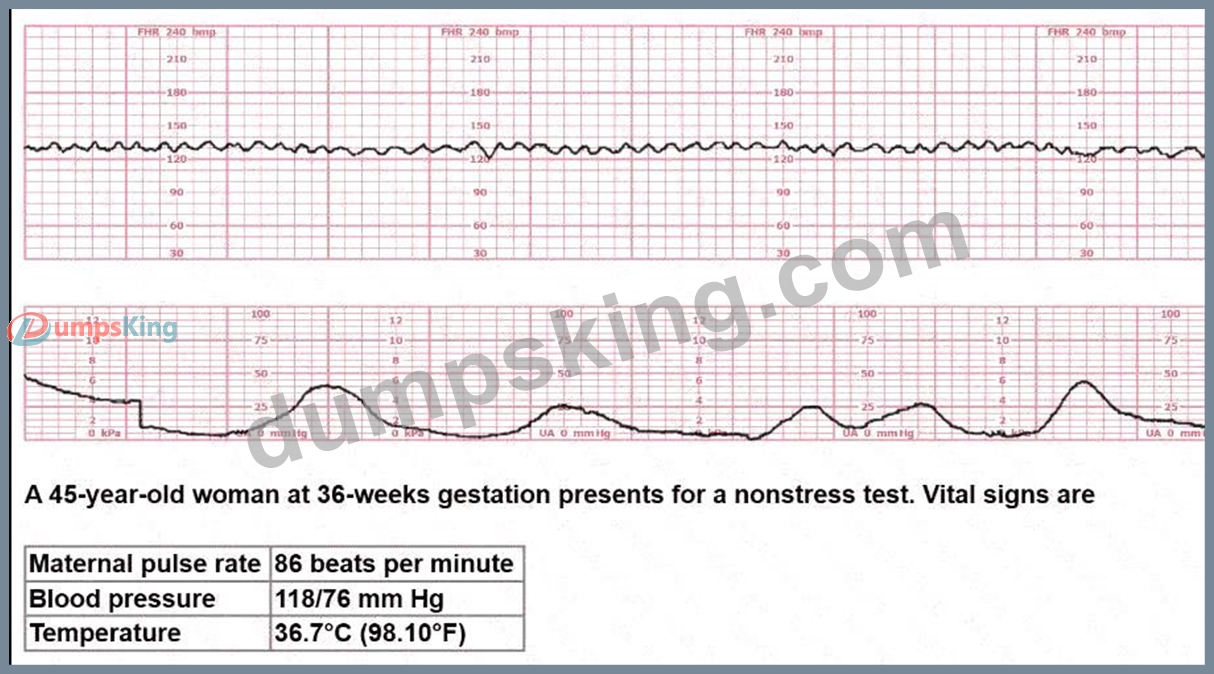
* Maternal pulse rate: 86 beats per minute
* Blood pressure: 118/76 mm Hg
* Temperature: 36.7°C (98.1°F)
The next course of action would include:
Answer: A
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
The NST strip shows:
* Baseline FHR about 140 bpm
* Moderate variability
* Two or more accelerations meeting 15×15 criteria
* No decelerations
* Normal, infrequent contractions
Per NCC and AWHONN, a reactive NST is defined as:
* #2 accelerations of 15 bpm × 15 seconds in a 20-minute period
* With baseline 110-160 and moderate variability
* No recurrent decelerations
A reactive NST at 36 weeks in a hemodynamically stable mother with normal vitals is reassuring, and the appropriate disposition is routine follow-up and discharge.
Why the other options are incorrect:
* B. Induce labor - Not indicated solely on maternal age or a reactive NST.
* C. Kleihauer-Betke test - Used to quantify fetomaternal hemorrhage after trauma or sensitization risk; there is no such history here.
Therefore, the correct action is A. Discharge home.
References:NCC C-EFM Candidate Guide; AWHONN Fetal Heart Monitoring Principles & Practices; Simpson & Creehan; Creasy & Resnik.
NEW QUESTION # 123
......
We have always been known as the superior after sale service provider, since we all tend to take lead of the whole process after you choose our EFM exam questions. So you have no need to trouble about our EFM learning guide. Our EFM training materials will continue to pursue our passion for better performance and comprehensive service of EFM Exam. Our worldwide after sale staff will be online and reassure your rows of doubts as well as exclude the difficulties and anxiety with all the customers. Just let us know your puzzles and we will figure out together.
EFM PDF Guide: https://www.dumpsking.com/EFM-testking-dumps.html
P.S. Free & New EFM dumps are available on Google Drive shared by DumpsKing: https://drive.google.com/open?id=1XKK7hK2jzQabh9gNlwtWd_qCui0N_L77