DOWNLOAD the newest RealValidExam CIC PDF dumps from Cloud Storage for free: https://drive.google.com/open?id=1iTJrmE4vgIB5WrKMs-GalXLXRdCHJPDj
For offline practice, our CBIC Certified Infection Control Exam (CIC) desktop practice test software is ideal. This CBIC Certified Infection Control Exam (CIC) software runs on Windows computers. The CBIC Certified Infection Control Exam (CIC) web-based practice exam is compatible with all browsers and operating systems. No software installation is required to go through the web-based CBIC Certified Infection Control Exam (CIC) practice test.
| Section | Weight | Objectives |
|---|---|---|
| Education, Research, and Quality Improvement | 9% | - Regulatory and accreditation compliance - Performance measurement and quality improvement - Development and delivery of education programs - Evidence-based practice and research application |
| Surveillance and Epidemiologic Investigation | 24% | - Outbreak investigation and response - Benchmarking and reporting - Data collection, validation, and analysis - Surveillance system design and implementation |
| Employee and Occupational Health | 10% | - Exposure management and post-exposure prophylaxis - Workplace safety policies - Immunization programs - Health screening and surveillance |
| Identification of Infectious Disease Processes | 19% | - Microbiology and pathogenesis - Epidemiologic principles - Emerging and re-emerging pathogens - Risk factors and transmission mechanisms |
| Prevention and Control of Transmission of Infectious Agents | 28% | - Hand hygiene and aseptic techniques - Antimicrobial stewardship - Isolation and patient placement - Standard and transmission-based precautions - Cleaning, disinfection, and sterilization |
| Environment of Care | 10% | - Safety and risk assessment - Waste management and environmental services - Facility design, construction, and renovation - Water and air quality management |
It is a prevailing belief for many people that practice separated from theories are blindfold. Our CIC learning quiz is a salutary guidance helping you achieve success. The numerous feedbacks from our clients praised and tested our strength on this career, thus our CIC practice materials get the epithet of high quality and accuracy. We are considered the best ally to our customers who want to pass their CIC exam by their first attempt and achieve the certification successfully!
NEW QUESTION # 41
Which of the following statements is true about the microbial activity of chlorhexidine soap?
Answer: A
Explanation:
Chlorhexidine soap is a widely used antiseptic agent in healthcare settings for hand hygiene and skin preparation due to its effective antimicrobial properties. The Certification Board of Infection Control and Epidemiology (CBIC) underscores the importance of proper hand hygiene and antiseptic use in the
"Prevention and Control of Infectious Diseases" domain, aligning with guidelines from the Centers for Disease Control and Prevention (CDC) and the World Health Organization (WHO). Understanding the microbial activity of chlorhexidine is essential for infection preventionists to recommend its appropriate use.
Option D, "Persistent activity with a broad spectrum effect," is the true statement. Chlorhexidine exhibits a broad spectrum of activity, meaning it is effective against a wide range of microorganisms, including gram- positive and gram-negative bacteria, some fungi, and certain viruses. Its persistent activity is a key feature, as it binds to the skin and provides a residual antimicrobial effect that continues to inhibit microbial growth for several hours after application. This residual effect is due to chlorhexidine's ability to adhere to the skin's outer layers, releasing slowly over time, which enhances its efficacy in preventing healthcare-associated infections (HAIs). The CDC's "Guideline for Hand Hygiene in Healthcare Settings" (2002) and WHO's
"Guidelines on Hand Hygiene in Health Care" (2009) highlight chlorhexidine's prolonged action as a significant advantage over other agents like alcohol.
Option A, "As fast as alcohol," is incorrect. Alcohol (e.g., 60-70% isopropyl or ethyl alcohol) acts rapidly by denaturing proteins and disrupting microbial cell membranes, providing immediate kill rates within seconds.
Chlorhexidine, while effective, has a slower onset of action, requiring contact times of 15-30 seconds or more to achieve optimal microbial reduction. Its strength lies in persistence rather than speed. Option B, "Can be used with any hand lotion," is false. Chlorhexidine's activity can be diminished or inactivated by certain hand lotions or creams containing anionic compounds (e.g., soaps or moisturizers with high pH), which neutralize its cationic properties. The CDC advises against combining chlorhexidine with incompatible products to maintain its efficacy. Option C, "Poor against gram positive bacteria," is incorrect. Chlorhexidine is highly effective against gram-positive bacteria (e.g., Staphylococcus aureus) and is often more potent against them than against gram-negative bacteria due to differences in cell wall structure, though it still has broad-spectrum activity.
The CBIC Practice Analysis (2022) supports the use of evidence-based antiseptics like chlorhexidine, and its persistent, broad-spectrum activity is well-documented in clinical studies (e.g., Larson, 1988, Journal of Hospital Infection). This makes Option D the most accurate statement regarding chlorhexidine soap's microbial activity.
References:
* CBIC Practice Analysis, 2022.
* CDC Guideline for Hand Hygiene in Healthcare Settings, 2002.
* WHO Guidelines on Hand Hygiene in Health Care, 2009.
* Larson, E. (1988). Guideline for Use of Topical Antimicrobial Agents. Journal of Hospital Infection.
NEW QUESTION # 42
The infection preventionist (IP) is working with the Product Evaluation Committee to select a sporicidal disinfectant for Clostridioides difficile. An effective disinfectant for the IP to recommend is
Answer: D
Explanation:
The correct answer is D, "sodium hypochlorite," as it is an effective sporicidal disinfectant for Clostridioides difficile that the infection preventionist (IP) should recommend. According to the Certification Board of Infection Control and Epidemiology (CBIC) guidelines, Clostridioides difficile (C. difficile) is a spore- forming bacterium responsible for significant healthcare-associated infections (HAIs), and its spores are highly resistant to many common disinfectants. Sodium hypochlorite (bleach) is recognized by the Centers for Disease Control and Prevention (CDC) and the Environmental Protection Agency (EPA) as a sporicidal agent capable of inactivating C. difficile spores when used at appropriate concentrations (e.g., 1:10 dilution of household bleach) and with the recommended contact time (CBIC Practice Analysis, 2022, Domain III:
Infection Prevention and Control, Competency 3.4 - Implement environmental cleaning and disinfection protocols). This makes it a preferred choice for environmental disinfection in outbreak settings or areas with known C. difficile contamination.
Option A (quaternary ammonium compound) is effective against many bacteria and viruses but lacks sufficient sporicidal activity against C. difficile spores, rendering it inadequate for this purpose. Option B (phenolic) has broad-spectrum antimicrobial properties but is not reliably sporicidal and is less effective against C. difficile spores compared to sodium hypochlorite. Option C (isopropyl alcohol) is useful for disinfecting surfaces and killing some pathogens, but it is not sporicidal and evaporates quickly, making it ineffective against C. difficile spores.
The IP's recommendation of sodium hypochlorite aligns with CBIC's emphasis on selecting disinfectants based on their efficacy against specific pathogens and adherence to evidence-based guidelines (CBIC Practice Analysis, 2022, Domain III: Infection Prevention and Control, Competency 3.5 - Evaluate the environment for infection risks). Proper use, including correct dilution and contact time, is critical to ensure effectiveness, and the IP should collaborate with the Product Evaluation Committee to ensure implementation aligns with safety and regulatory standards (CDC Guidelines for Environmental Infection Control in Healthcare Facilities, 2019).
References: CBIC Practice Analysis, 2022, Domain III: Infection Prevention and Control, Competencies 3.4 - Implement environmental cleaning and disinfection protocols, 3.5 - Evaluate the environment for infection risks. CDC Guidelines for Environmental Infection Control in Healthcare Facilities, 2019.
NEW QUESTION # 43
When designing a physical construction containment barrier to contain dust as well as potentially infectious microorganisms generated, reduced air pressure in the contained space relative to adjacent occupied spaces results in airflow from the:
Answer: C
Explanation:
The Certification Study Guide (6th edition) explains that during construction, renovation, or maintenance activities in healthcare facilities, negative (reduced) air pressure within the contained work area is a critical engineering control to prevent the spread of dust and potentially infectious microorganisms. When the pressure inside the containment is lower than in adjacent occupied areas, air naturally flows from areas of higher pressure to areas of lower pressure.
As a result, airflow moves from the clean adjacent space into the contained work space, rather than allowing contaminated air to escape outward. Once inside the containment, the air is then exhausted directly to the outside of the building or through appropriate filtration systems. This airflow pattern protects patients, visitors, and healthcare personnel in occupied areas by preventing construction-related contaminants-such as fungal spores (e.g., Aspergillus)-from spreading into patient care environments.
The study guide emphasizes that this principle is foundational to Infection Control Risk Assessments (ICRAs) and construction containment planning. Improper airflow direction can result in airborne contamination and has been associated with outbreaks, particularly among immunocompromised patients.
The incorrect options either reverse the airflow direction or allow contaminated air to re-enter the building, both of which violate infection prevention standards. Understanding airflow dynamics and pressure differentials is a frequently tested concept on the CIC exam and is essential for ensuring safe construction practices in healthcare facilities.
Reference: Certification Study Guide (CBIC/CIC Exam Study Guide), 6th edition, Chapter 9: Environment of Care.
NEW QUESTION # 44
What rate is expressed by the number of patients who acquire infections over a specified time period divided by the population at risk of acquiring an infection during that time period?
Answer: B
Explanation:
The incidence rate measures new cases of infection in a population over a defined time period using the formula: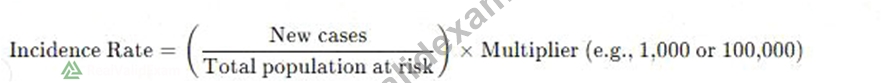
Why the Other Options Are Incorrect?
* B. Disease specific - Refers to infections caused by a particular pathogen, not the general rate of new infections.
* C. Point prevalence - Measures existing cases at a specific point in time, not new cases.
* D. Period prevalence - Includes both old and new cases over a set period, unlike incidence, which only considers new cases.
CBIC Infection Control Reference
APIC defines incidence rate as the number of new infections in a population over a given period.
NEW QUESTION # 45
A healthcare professional in a clinical microbiology laboratory is concerned about routine exposure to Neisseria meningitidis in culture. The healthcare professional last received the Meningococcal vaccine 8 years ago. What recommendation should be given to the healthcare professional regarding their meningococcal vaccination?
Answer: C
Explanation:
The correct answer is B, "They are due for a booster as it has been over 7 years," as this is the appropriate recommendation for the healthcare professional regarding their meningococcal vaccination. According to the Certification Board of Infection Control and Epidemiology (CBIC) guidelines, which align with recommendations from the Centers for Disease Control and Prevention (CDC) and the Advisory Committee on Immunization Practices (ACIP), healthcare professionals with routine exposure to Neisseria meningitidis, such as those in clinical microbiology laboratories, are at increased risk of meningococcal disease due to potential aerosol or droplet exposure during culture handling. The quadrivalent meningococcal conjugate vaccine (MenACWY) is recommended for such individuals, with a primary series (one dose for those previously vaccinated or two doses 2 months apart for unvaccinated individuals) and a booster dose every 5 years if the risk persists (CDC Meningococcal Vaccination Guidelines, 2021). However, for laboratory workers with ongoing exposure, the ACIP specifies a booster interval of every 5 years from the last dose, but this is often interpreted in practice as aligning with the 5-7 year range depending on risk assessment and institutional policy. Since the healthcare professional received the vaccine 8 years ago and works in a high- risk setting, a booster is due, with the 7-year threshold being a practical midpoint for this scenario (CBIC Practice Analysis, 2022, Domain III: Infection Prevention and Control, Competency 3.2 - Implement measures to prevent transmission of infectious agents).
Option A (they are due for a booster as it has been over 5 years) is close but slightly premature based on the 8- year interval, though it reflects the general 5-year booster guideline for high-risk groups; the 7-year option better matches the specific timeframe. Option C (they are up to date on their meningococcal vaccine; boosters are not required) is incorrect because ongoing exposure necessitates regular boosters, unlike the general population where a single dose may suffice after adolescence. Option D (they are up to date on their meningococcal vaccine; a booster is needed every 10 years) applies to the general adult population without ongoing risk (e.g., post-adolescence vaccination), not to laboratory workers with continuous exposure, where the interval is shorter.
The recommendation for a booster aligns with CBIC's emphasis on protecting healthcare personnel from occupational exposure to communicable diseases, ensuring compliance with evidence-based immunization practices (CBIC Practice Analysis, 2022, Domain III: Infection Prevention and Control, Competency 3.1 - Collaborate with organizational leaders). This supports the prevention of meningococcal disease outbreaks in healthcare settings.
References: CBIC Practice Analysis, 2022, Domain III: Infection Prevention and Control, Competencies 3.1 - Collaborate with organizational leaders, 3.2 - Implement measures to prevent transmission of infectious agents. CDC Meningococcal Vaccination Guidelines, 2021. ACIP Recommendations for Meningococcal Vaccines, 2020 (updated 2023).
NEW QUESTION # 46
......
All contents are masterpieces from experts who imparted essence of the exam into our CIC practice materials. So our high quality and high efficiency CIC practice materials conciliate wide acceptance around the world. By incubating all useful content CIC practice materials get passing rate from former exam candidates of 98 which evince our accuracy rate and proficiency. If your problems are divulging during the review you can pick out the difficult one and focus on those parts.
CIC Reliable Dumps Ppt: https://www.realvalidexam.com/CIC-real-exam-dumps.html
2026 Latest RealValidExam CIC PDF Dumps and CIC Exam Engine Free Share: https://drive.google.com/open?id=1iTJrmE4vgIB5WrKMs-GalXLXRdCHJPDj