BONUS!!! Download part of VCE4Plus CIC dumps for free: https://drive.google.com/open?id=1frV939LZTRWItbkHiKGzxXqB_LSGLHAk
CIC Exam Questions of VCE4Plus are ideal for the students who are willing to prepare for the exam in a short time. The CBIC Certified Infection Control Exam (CIC) professionals have worked hard on making this product one of the most successful and user-friendly. This CBIC Certified Infection Control Exam (CIC) exam prep material came into existence after talking to many CBIC professionals and getting their positive feedback. The VCE4Plus guarantees the customers that if they fail to pass the CBIC Certified Infection Control Exam (CIC) exam despite all their efforts they can claim a refund according to some terms and conditions.
| Section | Objectives |
|---|---|
| Cleaning, Disinfection, and Sterilization | - Sterilization methods and validation - Environmental cleaning standards - High-level disinfection practices |
| Infection Prevention and Control Program Management | - Program development and leadership - Regulatory compliance - Policy and guideline implementation |
| Education, Consultation, and Research | - Staff education strategies - Evidence-based practice and guideline interpretation |
| Occupational Health | - Immunization and post-exposure protocols - Healthcare worker exposure prevention |
| Environment of Care | - Air and water quality management - Healthcare facility design and risk reduction |
| Identification of Infectious Disease Processes | - Chain of infection and transmission routes - Host susceptibility factors - Pathogenesis of infectious diseases |
| Surveillance and Epidemiologic Investigation | - Healthcare-associated infection surveillance methods - Data collection and analysis - Outbreak investigation and response |
>> Reliable CIC Study Guide <<
Going through our CBIC CIC certification exam prep material there remains no chance of failure in the CBIC exam. So do not waste your time anymore, avail the best CBIC CIC Exam Practice material and start your journey towards a bright career.
NEW QUESTION # 277
During the last week in June, an emergency department log reveals numerous cases of profuse watery diarrhea in individuals 74 years of age and older. During the same time period, four immunocompromised patients were admitted with possible Cryptosporidium. Which of the following actions should the infection preventionist take FIKST?
Answer: B
Explanation:
When an outbreak of infectious disease is suspected, the first step is to conduct an epidemiologic investigation. This begins with characterizing the outbreak by person, place, and time to establish patterns and trends. This approach, known as descriptive epidemiology, provides critical insights into potential sources and transmission patterns.
Step-by-Step Justification:
* Identify Cases and Patterns:
* The infection preventionist should analyze patient demographics (person), locations of cases (place), and onset of symptoms (time). This helps in defining the outbreak scope and potential exposure sources.
* Create an Epidemic Curve:
* An epidemic curve helps determine whether the outbreak is a point-source or propagated event.
This can indicate whether the infection is spreading person-to-person or originating from a common source.
* Compare with Baseline Data:
* Reviewing historical data ensures that the observed cases exceed the expected norm, confirming an outbreak.
* Guide Further Investigation:
* Establishing basic epidemiologic patterns guides subsequent actions, such as laboratory testing, environmental sampling, and surveillance.
Why Other Options Are Incorrect:
* B. Increase surveillance facility-wide for additional cases:
* While enhanced surveillance is important, it should follow the initial characterization of the outbreak. Surveillance without a defined case profile may lead to misclassification and misinterpretation.
* C. Contact the laboratory to confirm stool identification results:
* Confirming lab results is essential but comes after defining the outbreak's characteristics. Without an epidemiologic link, testing may yield results that are difficult to interpret.
* D. Form a tentative hypothesis about the potential reservoir for this outbreak:
* Hypothesis generation occurs after sufficient epidemiologic data have been collected. Jumping to conclusions without characterization may result in incorrect assumptions and ineffective control measures.
CBIC Infection Control References:
* APIC Text, "Outbreak Investigations," Epidemiology, Surveillance, Performance, and Patient Safety Measures.
* APIC/JCR Infection Prevention and Control Workbook, Chapter 4, Surveillance Program.
* APIC Text, "Investigating Infectious Disease Outbreaks," Guidelines for Epidemic Curve Analysis.
NEW QUESTION # 278
A 36-year-old female presents to the Emergency Department with a petechial rash, meningitis, and cardiac arrest. During the resuscitation, a phlebotomist sustained a needlestick injury. The next day, blood cultures reveal Neisseria meningitidis. The exposure management for the phlebotomist is:
Answer: B
Explanation:
The scenario involves a needlestick injury sustained by a phlebotomist during the resuscitation of a patient diagnosed with Neisseria meningitidis infection, characterized by a petechial rash, meningitis, and cardiac arrest. Neisseria meningitidis is a gram-negative diplococcus that can cause meningococcal disease, including meningitis and septicemia, and is transmitted through direct contact with respiratory secretions or, in rare cases, blood exposure. The exposure management for the phlebotomist must align with infection control guidelines, such as those from the Certification Board of Infection Control and Epidemiology (CBIC) and the CDC, to prevent potential infection. Let's evaluate each option:
* A. Prophylactic rifampin plus isoniazid: Prophylactic antibiotics are recommended for close contacts of individuals with meningococcal disease to prevent secondary cases. Rifampin is a standard prophylactic agent for Neisseria meningitidis exposure, typically administered as a 2-day course (e.g., 600 mg every
12 hours for adults). Isoniazid, however, is used for tuberculosis (TB) prophylaxis and is not indicated for meningococcal disease. Combining rifampin with isoniazid is incorrect, as it reflects a confusion with TB management rather than meningococcal exposure. This option is not appropriate.
* B. A tuberculin skin test now and in ten weeks: A tuberculin skin test (TST) or interferon-gamma release assay (IGRA) is used to screen for latent tuberculosis infection, with a follow-up test at 8-10 weeks to detect conversion after potential TB exposure. Neisseria meningitidis is not related to TB, and a needlestick injury from a meningococcal patient does not warrant TB testing. This option is irrelevant to the scenario and not the correct exposure management.
* C. Work furlough from day ten to day 21 after exposure: Neisseria meningitidis has an incubation period of 2-10 days, with a maximum of about 14 days in rare cases. The CDC and WHO recommend that healthcare workers exposed to meningococcal disease via needlestick or mucosal exposure be monitored for signs of infection (e.g., fever, rash) and, if symptomatic, isolated and treated.
Additionally, a work restriction or furlough from day 10 to day 21 after exposure is advised to cover the potential incubation period, especially if prophylaxis is declined or contraindicated. This allows time to observe for symptoms and prevents transmission to vulnerable patients. This is a standard infection control measure and the most appropriate initial management step pending prophylaxis decision.
* D. A review of the phlebotomist's hepatitis B vaccine status: Reviewing hepatitis B vaccine status is a critical step following a needlestick injury, as hepatitis B can be transmitted through blood exposure.
However, this applies to bloodborne pathogens (e.g., HBV, HCV, HIV) and is not specific to Neisseria meningitidis, which is primarily a respiratory or mucosal pathogen. While hepatitis B management (e.
g., post-exposure prophylaxis with hepatitis B immunoglobulin or vaccine booster) should be addressed as part of a comprehensive needlestick protocol, it is not the first or most relevant priority for meningococcal exposure.
The best answer is C, as the work furlough from day 10 to day 21 after exposure addresses the specific risk of meningococcal disease following a needlestick injury. This aligns with CBIC's focus on timely intervention and work restriction to prevent transmission in healthcare settings. Prophylactic antibiotics (e.g., rifampin) should also be considered, but the question asks for the exposure management, and furlough is a primary control measure. Hepatitis B and TBconsiderations are secondary and managed separately.
:
CBIC Infection Prevention and Control (IPC) Core Competency Model (updated 2023), Domain III:
Prevention and Control of Infectious Diseases, which includes protocols for managing exposure to communicable diseases like meningococcal infection.
CBIC Examination Content Outline, Domain IV: Environment of Care, which addresses work restrictions and exposure management.
CDC Guidelines for Meningococcal Disease Prevention and Control (2023), which recommend work furlough and monitoring for exposed healthcare workers.
NEW QUESTION # 279
There are four cases of ventilator-associated pneumonia in a surgical intensive care unit with a total of 200 ventilator days and a census of 12 patients. Which of the following BEST expresses how this should be reported?
Answer: D
Explanation:
The standard way to report ventilator-associated pneumonia (VAP) rates is: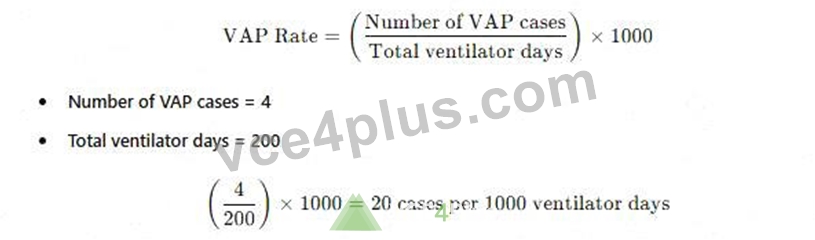
Why the Other Options Are Incorrect?
A). Ventilator-associated pneumonia rate of 2% - This does not use the correct denominator (ventilator days).
C). Postoperative pneumonia rate of 6% in SICU patients - Not relevant, as the data focuses on VAP, not postoperative pneumonia.
D). More information is needed regarding ventilator days per patient - The total ventilator days are already provided, so no additional data is required.
CBIC Infection Control Reference
APIC and NHSN recommend reporting VAP rates as cases per 1,000 ventilator days.
NEW QUESTION # 280
A patient is Hepatitis B surface antigen (HBsAg) negative, Hepatitis B surface antibody (anti-HBs) positive, and Hepatitis B core antibody (anti-HBc) negative. Which of the following explains these results?
Answer: B
Explanation:
The Certification Study Guide (6th edition) explains that interpretation of hepatitis B serologic markers is a fundamental competency for infection preventionists, particularly in occupational health and exposure management. In this scenario, the patient is HBsAg negative, indicating no current hepatitis B infection; anti- HBs positive, indicating immunity; and anti-HBc negative, meaning there has been no prior natural infection with hepatitis B virus.
This specific serologic pattern is diagnostic of immunity due to vaccination. The hepatitis B vaccine contains only purified hepatitis B surface antigen, not core antigen. As a result, vaccinated individuals develop antibodies to the surface antigen (anti-HBs) but do not develop antibodies to the core antigen (anti-HBc). The study guide emphasizes this distinction as the key factor in differentiating vaccine-induced immunity from immunity due to past infection.
The incorrect options reflect different serologic patterns. Previous hepatitis B infection would produce a positive anti-HBc result. A recent blood transfusion does not confer long-term immunity or this marker pattern. Low-level infectivity would require detectable surface antigen or core antibody.
This question reflects a classic CIC exam topic: recognizing the serologic profile of vaccine-induced immunity. Correct interpretation supports appropriate employee health decisions, post-exposure management, and immunization program evaluation.
Reference: Certification Study Guide (CBIC/CIC Exam Study Guide), 6th edition, Chapter 6: Employee
/Occupational Health; Chapter 3: Identification of Infectious Disease Processes.
NEW QUESTION # 281
A 36-year-old female presents to the Emergency Department with a petechial rash, meningitis, and cardiac arrest. During the resuscitation, a phlebotomist sustained a needlestick injury. The next day, blood cultures reveal Neisseria meningitidis. The exposure management for the phlebotomist is:
Answer: B
Explanation:
The scenario involves a needlestick injury sustained by a phlebotomist during the resuscitation of a patient diagnosed with Neisseria meningitidis infection, characterized by a petechial rash, meningitis, and cardiac arrest. Neisseria meningitidis is a gram-negative diplococcus that can cause meningococcal disease, including meningitis and septicemia, and is transmitted through direct contact with respiratory secretions or, in rare cases, blood exposure. The exposure management for the phlebotomist must align with infection control guidelines, such as those from the Certification Board of Infection Control and Epidemiology (CBIC) and the CDC, to prevent potential infection. Let's evaluate each option:
* A. Prophylactic rifampin plus isoniazid: Prophylactic antibiotics are recommended for close contacts of individuals with meningococcal disease to prevent secondary cases. Rifampin is a standard prophylactic agent for Neisseria meningitidis exposure, typically administered as a 2-day course (e.g., 600 mg every
12 hours for adults). Isoniazid, however, is used for tuberculosis (TB) prophylaxis and is not indicated for meningococcal disease. Combining rifampin with isoniazid is incorrect, as it reflects a confusion with TB management rather than meningococcal exposure. This option is not appropriate.
* B. A tuberculin skin test now and in ten weeks: A tuberculin skin test (TST) or interferon-gamma release assay (IGRA) is used to screen for latent tuberculosis infection, with a follow-up test at 8-10 weeks to detect conversion after potential TB exposure. Neisseria meningitidis is not related to TB, and a needlestick injury from a meningococcal patient does not warrant TB testing. This option is irrelevant to the scenario and not the correct exposure management.
* C. Work furlough from day ten to day 21 after exposure: Neisseria meningitidis has an incubation period of 2-10 days, with a maximum of about 14 days in rare cases. The CDC and WHO recommend that healthcare workers exposed to meningococcal disease via needlestick or mucosal exposure be monitored for signs of infection (e.g., fever, rash) and, if symptomatic, isolated and treated.
Additionally, a work restriction or furlough from day 10 to day 21 after exposure is advised to cover the potential incubation period, especially if prophylaxis is declined or contraindicated. This allows time to observe for symptoms and prevents transmission to vulnerable patients. This is a standard infection control measure and the most appropriate initial management step pending prophylaxis decision.
* D. A review of the phlebotomist's hepatitis B vaccine status: Reviewing hepatitis B vaccine status is a critical step following a needlestick injury, as hepatitis B can be transmitted through blood exposure.
However, this applies to bloodborne pathogens (e.g., HBV, HCV, HIV) and is not specific to Neisseria meningitidis, which is primarily a respiratory or mucosal pathogen. While hepatitis B management (e.
g., post-exposure prophylaxis with hepatitis B immunoglobulin or vaccine booster) should be addressed as part of a comprehensive needlestick protocol, it is not the first or most relevant priority for meningococcal exposure.
The best answer is C, as the work furlough from day 10 to day 21 after exposure addresses the specific risk of meningococcal disease following a needlestick injury. This aligns with CBIC's focus on timely intervention and work restriction to prevent transmission in healthcare settings. Prophylactic antibiotics (e.g., rifampin) should also be considered, but the question asks for the exposure management, and furlough is a primary control measure. Hepatitis B and TB considerations are secondary and managed separately.
CBIC Infection Prevention and Control (IPC) Core Competency Model (updated 2023), Domain III:
Prevention and Control of Infectious Diseases, which includes protocols for managing exposure to communicable diseases like meningococcal infection.
CBIC Examination Content Outline, Domain IV: Environment of Care, which addresses work restrictions and exposure management.
CDC Guidelines for Meningococcal Disease Prevention and Control (2023), which recommend work furlough and monitoring for exposed healthcare workers.
NEW QUESTION # 282
......
Our website platform has no viruses and you can download CIC test guide at ease. If you encounter difficulties in installation or use of CIC exam torrent, we will provide you with remote assistance from a dedicated expert to help you and provide 365 days of free updates that you do not have to worry about what you missed. Whether you are a worker or student, you will save much time to do something whatever you want. It only needs 5-10 minutes after you pay for our CIC learn torrent that you can learn it to prepare for your exam. Actually, if you can guarantee that your effective learning time with CIC test preps are up to 20-30 hours, you can pass the exam.
Verified CIC Answers: https://www.vce4plus.com/CBIC/CIC-valid-vce-dumps.html
P.S. Free 2026 CBIC CIC dumps are available on Google Drive shared by VCE4Plus: https://drive.google.com/open?id=1frV939LZTRWItbkHiKGzxXqB_LSGLHAk