P.S. Free 2026 NCC EFM dumps are available on Google Drive shared by PassTorrent: https://drive.google.com/open?id=1R-yTba_PM0tJeENoFBg0GHbDUgR89Mh_
Nowadays in this information-based world the definition of the talents has changed a lot and the talents mean that the personnel boost both the knowledge in EFM area and the practical abilities now. With our EFM exam braindumps, you can get what you want. Our EFM Study Materials are easy to be mastered and boost varied functions. We compile Our EFM preparation questions elaborately and provide the wonderful service to you thus you can get a good learning and preparation for the exam.
| Section | Weight | Objectives |
|---|---|---|
| Topic 1: Fetal Assessment and Methods | 9% | - Correlation with clinical status - Auxiliary assessment techniques - Indications for monitoring |
| Topic 2: Pattern Recognition and Intervention | 70% | - Fetal heart rate patterns classification - Tracing evaluation and management - Interpretation per NICHD standards - Clinical decision-making and interventions |
| Topic 3: Physiology | 11% | - Fetal cardiovascular physiology - Uteroplacental function - Factors affecting fetal oxygenation |
| Topic 4: Professional Issues | 5% | - Safety and quality improvement - Documentation standards - Legal and ethical aspects |
| Topic 5: Electronic Monitoring Equipment | 5% | - Proper application and use - Calibration and accuracy - Troubleshooting artifacts |
Our EFM study materials have enough confidence to provide the best EFM exam torrent for your study to pass it. With many years work experience, we have fast reaction speed to market change and need. In this way, we have the latest EFM guide torrent. You don't worry about that how to keep up with the market trend, just follow us. We can say that our EFM Test Questions are the most suitable for examinee to pass the EFM exam, you will never regret to buy it.
NEW QUESTION # 16
Fetal respiratory acidosis is most likely to present with which of the following fetal heart rate decelerations?
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
NCC and AWHONN physiology teachings:
* Variable decelerations caused by cord compression lead to:
* Transient interruption of umbilical venous flow
* Impaired fetal gas exchange
* Acute rise in CO#
* Respiratory acidosis (early phase of hypoxemia)
This is well documented:
* Early decelerations # head compression # NOT associated with acidemia.
* Late decelerations # uteroplacental insufficiency # metabolic acidosis, not respiratory.
Thus:
* Variable decelerations # respiratory acidosis
* Late decelerations # metabolic acidosis
Correct answer: C. Variable
References:NCC Physiology Domain; AWHONN FHMPP; Menihan EFM; Simpson & Creehan; Creasy & Resnik.
NEW QUESTION # 17
A 30-year-old woman (G2P0) is experiencing preterm labor at 26-weeks gestation. She is receiving magnesium sulfate for neuroprotection. Her external fetal monitoring tracing over the past 30 minutes is shown. The next step would be to: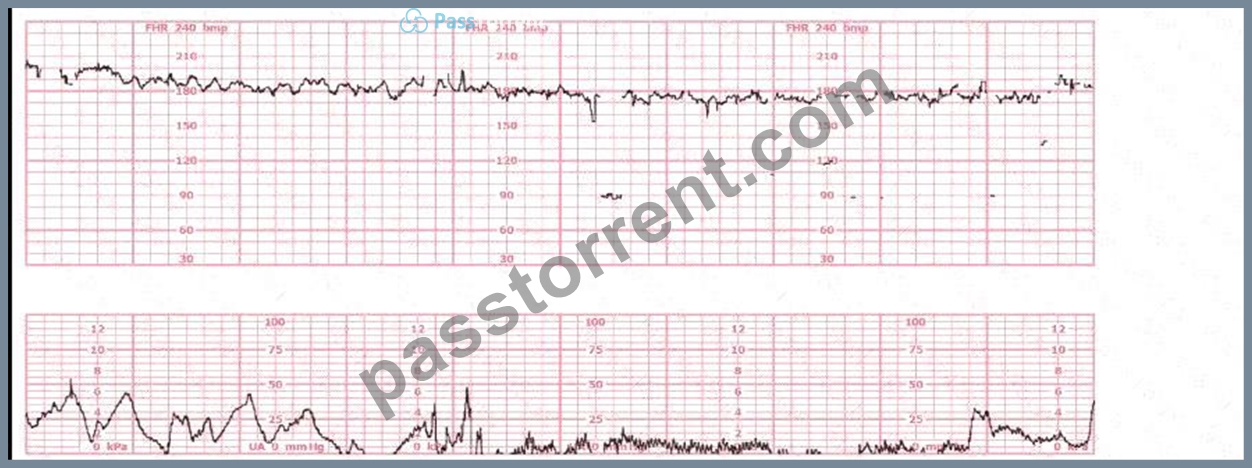
Answer: C
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
This tracing shows:
* Baseline ~170-175 bpm # fetal tachycardia
* Minimal variability
* No contractions of significance
* Maternal treatment with magnesium sulfate, which typically decreases baseline and variability-not increase it NCC and AWHONN physiology guidelines emphasize that fetal tachycardia is most commonly associated with maternal infection, including chorioamnionitis, especially in preterm labor.
Magnesium sulfate does not cause tachycardia; it generally causes:
* # baseline
* # variability
Thus, fetal tachycardia + minimal variability in a preterm patient strongly suggests maternal infection, requiring evaluation for chorioamnionitis.
Why the wrong answers are incorrect:
* A. Acetaminophen # used after confirming fever, not before evaluating the cause.
* B. Discontinuing magnesium # magnesium sulfate does not cause tachycardia; discontinuing it removes fetal neuroprotection.
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; Simpson & Creehan; Menihan EFM; Creasy & Resnik.
NEW QUESTION # 18
In documenting auscultation of the fetal heart rate, it is important to record findings in relationship to:
Answer: C
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
NCC and AWHONN auscultation standards emphasize the need to document FHR findings relative to uterine contractions, including:
* The FHR between contractions (baseline)
* FHR during contractions
* Presence/absence of decelerations
* Recovery after a contraction
Uterine activity determines whether findings are:
* Baseline
* Accelerations
* Early/late/variable decelerations
Why the other options are incorrect:
* A. Fetal position - relevant for Doppler placement, not auscultation documentation.
* B. Stage of labor - affects monitoring frequency but does not change how findings are documented.
Correct answer: C. Uterine activity.
References:NCC C-EFM Candidate Guide; AWHONN Standards for FHR Auscultation; Simpson & Creehan.
NEW QUESTION # 19
This fetal heart rate tracing is obtained upon the woman's admission to labor and delivery. This tracing is most reflective of: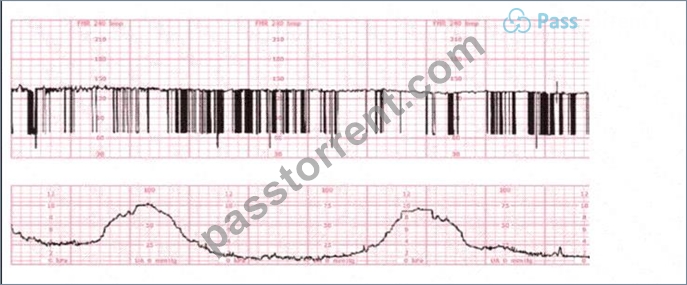
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
When evaluating an admission tracing, NCC emphasizes determining whether the pattern represents baseline variability abnormalities, signal artifact, or an underlying fetal cardiac rhythm disturbance. The strip shown contains clear features of a fetal dysrhythmia, which NCC and AWHONN describe as an irregular rhythm characterized by inconsistent R-R intervals or intermittent missed beats.
Key features in this tracing:
* Extremely irregular FHR signalThe pattern shows abrupt vertical spikes, inconsistent spacing, and intermittent loss of coherent waveform. NCC teaches that this appearance is typical of irregular ventricular conduction or premature atrial/ventricular contractions.
* Wide variability in beat spacingBeat intervals vary significantly, suggesting ectopic beats or conduction abnormalities rather than a stable rhythm such as heart block or atrial flutter.
* Sensor not malfunctioningThe lower uterine activity channel is smooth and consistent, meaning the upper channel's abrupt changes represent true FHR signal irregularity, not artifact.
Why the incorrect answers are ruled out:
A). Atrial flutter - NOT supported
* Atrial flutter produces a very fast, regular atrial rate (typically 300 bpm) with a repetitive saw-tooth pattern.
* It does not produce the highly irregular beat-to-beat pattern seen here.
* FHR in atrial flutter appears more organized, not chaotic.
B). Complete heart block - NOT supported
* Complete heart block (third-degree AV block) produces a very slow, regular ventricular rate, commonly 50-70 bpm, with a dissociation between atrial and ventricular rhythms.
* The tracing here does not show a slow, steady baseline.
* Instead, the rhythm is highly irregular with spikes and losses-not characteristic of AV block.
C). Fetal dysrhythmia - CORRECT
* NCC, AWHONN, Miller, and Menihan describe fetal dysrhythmias as:"Irregular, inconsistent FHR patterns due to premature atrial contractions (PACs), premature ventricular contractions (PVCs), or intermittent conduction disturbances."
* The hallmark is an irregular rhythm, often appearing as abrupt spikes or missing beats on the monitor.
* The tracing shown matches these characteristics precisely.
Therefore, the tracing is most consistent with fetal dysrhythmia, typically benign PACs/PVCs, and is the correct answer.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 20
A woman in labor has been pushing for 4 hours. For the last 2 hours, there have been recurrent variable decelerations. Variability has evolved from moderate to minimal. Cervical exam is 10/100%
/+2, fetal head OP. There has been no fetal descent for the last 45 minutes. Based on the tracing shown, the most reasonable approach is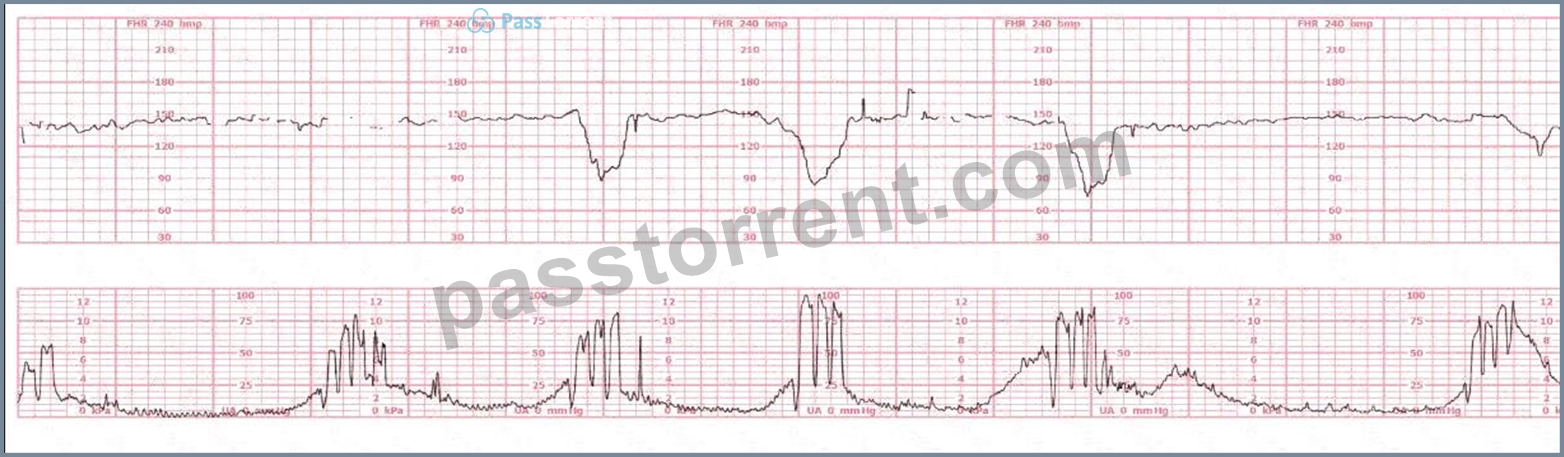
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract (NCC-Referenced Sources) According to the NCC C-EFM Exam Outline and AWHONN Fetal Heart Monitoring (5th & 6th ed.), recurrent variable decelerations with progressive reduction in variability reflect worsening fetal hypoxia, especially when coupled with prolonged second stage and arrest of descent.
AWHONN and Menihan both state that:
* "Minimal variability with recurrent decelerations indicates inability of the fetus to maintain adequate oxygenation."
* "Failure of descent in second stage with non-reassuring patterns requires operative delivery." Creasy & Resnik emphasize that operative vaginal birth requires:
(1) fetal head at +2 station or below,
(2) favorable position,
(3) reassuring fetal status.
Here, the fetus is OP, descent has arrested, and FHR is non-reassuring. This contraindicates vacuum extraction.
Therefore, the appropriate management under NCC competencies is cesarean birth.
NEW QUESTION # 21
......
When you decide to pass the EFM exam and get relate certification, you must want to find a reliable exam tool to prepare for exam. That is the reason why I want to recommend our EFM prep guide to you, because we believe this is what you have been looking for. Moreover we are committed to offer you with data protect act and guarantee you will not suffer from virus intrusion and information leakage after purchasing our EFM Guide Torrent. The last but not least we have professional groups providing guidance in terms of download and installment remotely.
Relevant EFM Answers: https://www.passtorrent.com/EFM-latest-torrent.html
BONUS!!! Download part of PassTorrent EFM dumps for free: https://drive.google.com/open?id=1R-yTba_PM0tJeENoFBg0GHbDUgR89Mh_