P.S. Free & New CIC dumps are available on Google Drive shared by Real4Prep: https://drive.google.com/open?id=149lePdyZX_lZZrF8A60DmKZnG3Wn8sNA
Our company is a professional certificate study materials provider. We have occupied in this field for years, we are in the leading position of providing exam materials. CIC training materials of us is high-quality and accurate, for we have a profession team to verify and update the CIC answers and questions. We have received many good feedbacks from our customers for helping pass the exam successfully. Furthermore, we provide you free update for one year after purchasing CIC exam dumps from us.
| Section | Weight | Objectives |
|---|---|---|
| Topic 1: Identification of Infectious Disease Processes | 17-19% | |
| Topic 2: Management and Communication | 10-13% | |
| Topic 3: Environment of Care | 10-13% | |
| Topic 4: Surveillance and Epidemiologic Investigation | 22-26% | |
| Topic 5: Cleaning, Sterilization, Disinfection, Asepsis | 10-13% | |
| Topic 6: Preventing/Controlling the Transmission of Infectious Agents | 17-19% | |
| Topic 7: Employee/Occupational Health | 10-13% | |
| Topic 8: Education and Research | 6-9% |
It is the best choice to accelerate your career by getting qualified by CIC certification. Real4Prep provides the most updated and accurate CIC study pdf for clearing your actual test. The quality of CIC practice training torrent is checked by our professional experts. The high pass rate and high hit rate of CBIC pdf vce can ensure you 100% pass in the first attempt. What’s more, if you fail the CIC test unfortunately, we will give you full refund without any hesitation.
NEW QUESTION # 145
An infection preventionist (IP) is asked to participate on a team to decrease ventilator-associated pneumonia (VAP) rates in a 20-bed ICU. The IP provides the following information. What is the first quarter ventilator utilization ratio?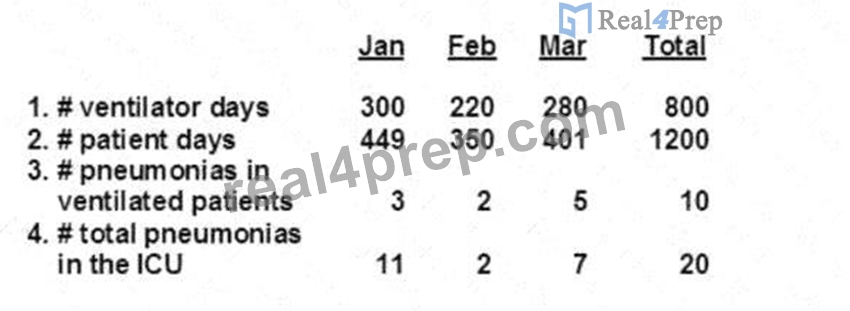
Data Provided (First Quarter):
Ventilator days (Jan-Mar total): 800
Patient days (Jan-Mar total): 1200
Answer: A
Explanation:
The Certification Study Guide (6th edition) defines the ventilator utilization ratio (VUR) as a device utilization measure used in surveillance to describe the proportion of patient time during which a specific medical device-in this case, mechanical ventilation-is in use. It is calculated by dividing the total number of ventilator days by the total number of patient days for the same location and time period.
Using the first-quarter data provided, the calculation is as follows:
Ventilator Utilization Ratio = Ventilator Days ÷ Patient Days
Ventilator Utilization Ratio = 800 ÷ 1200 = 0.67
This means that ventilators were in use for 67% of all patient days in the ICU during the first quarter. The study guide emphasizes that device utilization ratios are essential for interpreting device-associated infection data, such as VAP rates, because they reflect the level of patient exposure to the device. Higher utilization increases the population at risk and can influence infection rates independently of prevention practices.
The other answer options are incorrect because they do not reflect the correct calculation. A ratio greater than
1.0 (options C and D) would imply more device days than patient days, which is not possible in this context.
Option A underestimates utilization and does not match the provided data.
Understanding and correctly calculating utilization ratios is a core CIC exam competency, as these metrics support accurate surveillance, benchmarking, and performance improvement efforts.
Reference: Certification Study Guide (CBIC/CIC Exam Study Guide), 6th edition, Chapter 4: Surveillance and Epidemiologic Investigation.
NEW QUESTION # 146
An infection preventionist (IP) is reviewing blood cultures and notices several results with Arcanobacterium, coagulase-negative Staphylococcus, and Corynebacterium. What action is needed from the IP?
Answer: A
Explanation:
The CBIC Certified Infection Control Exam Study Guide (6th edition) emphasizes that certain organisms commonly recovered from blood cultures-such as Arcanobacterium, coagulase-negative Staphylococcus, and Corynebacterium-are frequently associated with skin contamination rather than true bloodstream infection. When multiple blood cultures yield these organisms, the infection preventionist must assess whether the findings represent contamination related to collection practices rather than immediately assuming infection or outbreak.
The most appropriate action is to collaborate with the laboratory manager and clinical teams to evaluate potential trends, specimen collection techniques, and changes in practice. This includes reviewing blood culture contamination rates, assessing skin antisepsis procedures, evaluating staff competency, and determining whether there has been an increase associated with a specific unit, shift, or collection method.
Surveillance data and laboratory quality indicators are essential tools in this evaluation.
Option A is incorrect because results should never be disregarded without assessment. Option B is premature, as the organisms listed are not typical outbreak pathogens and require further analysis before escalation.
Option C is inappropriate because these organisms do not automatically meet criteria for healthcare- associated bloodstream infection without supporting clinical evidence.
This scenario reflects a core CIC exam concept: infection preventionists must apply epidemiologic principles, collaborate with laboratory services, and use data-driven analysis to differentiate contamination from infection and to guide quality improvement efforts.
=========
NEW QUESTION # 147
The annual report for Infection Prevention shows a dramatic decrease in urinary catheter days, a decrease in the catheter utilization ratio, and a slight decrease in the number of catheter-associated urinary tract infections (CAUTIs). The report does not show an increase in the overall rate of CAUTI. How would the infection preventionist explain this to the administration?
Answer: D
Explanation:
The correct answer is B, "The rate may be higher if the denominator is very small," as this provides the most plausible explanation for the observed data in the annual report. According to the Certification Board of Infection Control and Epidemiology (CBIC) guidelines, the CAUTI rate is calculated as the number of CAUTIs per 1,000 catheter days, where catheter days serve as the denominator. The report indicates a dramatic decrease in urinary catheter days and a slight decrease in the number of CAUTIs, yet the overall CAUTI rate has not increased. This discrepancy can occur if the denominator (catheter days) becomes very small, which can inflate or destabilize the rate, potentially masking an actual increase in the infection risk per catheter day (CBIC Practice Analysis, 2022, Domain II: Surveillance and Epidemiologic Investigation, Competency 2.2 - Analyze surveillance data). A smaller denominator amplifies the impact of even a slight change in the number of infections, suggesting that the rate may be higher than expected or less reliable, necessitating further investigation.
Option A (the rate is incorrect and needs to be recalculated) assumes an error in the calculation without evidence, which is less specific than the denominator effect explanation. Option C (the rate is not affected by the number of catheter days) is incorrect because the CAUTI rate is directly influenced by the number of catheter days as the denominator; a decrease in catheter days should typically lower the rate if infections decrease proportionally, but the lack of an increase here suggests a calculation or interpretation issue. Option D (decreasing catheter days will not have an effect on decreasing CAUTI) contradicts evidence-based practice, as reducing catheter days is a proven strategy to lower CAUTI incidence, though the rate's stability here indicates a potential statistical artifact.
The explanation focusing on the denominator aligns with CBIC's emphasis on accurate surveillance and data analysis to guide infection prevention strategies, allowing the infection preventionist to advise administration on the need to review data trends or adjust monitoring methods (CBIC Practice Analysis, 2022, Domain II:
Surveillance and Epidemiologic Investigation, Competency 2.5 - Use data to guide infection prevention and control strategies). This insight can prompt a deeper analysis to ensure the CAUTI rate reflects true infection risk.
References: CBIC Practice Analysis, 2022, Domain II: Surveillance and Epidemiologic Investigation, Competencies 2.2 - Analyze surveillance data, 2.5 - Use data to guide infection prevention and control strategies.
NEW QUESTION # 148
Which of the following is an essential element of practice when sending biohazardous samples from one location to another?
Answer: C
Explanation:
The safe transport of biohazardous samples, such as infectious agents, clinical specimens, or diagnostic materials, is a critical aspect of infection prevention and control to prevent exposure and environmental contamination. The Certification Board of Infection Control and Epidemiology (CBIC) emphasizes adherence to regulatory and safety standards in the "Prevention and Control of Infectious Diseases" domain, which includes proper handling and shipping of biohazardous materials. The primary guideline governing this practice is the U.S. Department of Transportation (DOT) Hazardous Materials Regulations (HMR) and the International Air Transport Association (IATA) Dangerous Goods Regulations, which align with global biosafety standards.
Option A, "Ship using triple-containment packaging," is the essential element of practice. Triple-containment packaging involves three layers: a primary watertight container holding the sample, a secondary leak-proof container with absorbent material, and an outer rigid packaging (e.g., a box) that meets shipping regulations.
This system ensures that biohazardous materials remain secure during transport, preventing leaks or breaches that could expose handlers or the public. The CDC and WHO endorse this method as a fundamental requirement for shipping Category A (high-risk) and Category B (moderate-risk) infectious substances, making it the cornerstone of safe transport practice.
Option B, "Electronically log and send via overnight delivery," is a useful administrative and logistical step to track shipments and ensure timely delivery, but it is not the essential element. While documentation and rapid delivery are important for maintaining chain of custody and sample integrity, they are secondary to the physical containment provided by triple packaging. Option C, "Transport by an authorized biohazard transporter," is a necessary step to comply with regulations, as only trained and certified transporters can handle biohazardous materials. However, this is contingent on proper packaging; without triple containment, transport authorization alone is insufficient. Option D, "Store in a cooler that is labeled as a health hazard," may be part of preparation (e.g., maintaining sample temperature), but labeling alone does not address the containment or transport safety required during shipment. Coolers are often used, but the focus on labeling as a health hazard is incomplete without the triple-containment structure.
The CBIC Practice Analysis (2022) supports compliance with federal and international shipping regulations, which prioritize triple-containment packaging as the foundational practice to mitigate risks. The CDC's Biosafety in Microbiological and Biomedical Laboratories (BMBL, 6th Edition, 2020) and IATA guidelines further specify that triple packaging is mandatory for all biohazardous shipments, reinforcing Option A as the correct answer.
References:
* CBIC Practice Analysis, 2022.
* CDC Biosafety in Microbiological and Biomedical Laboratories (BMBL), 6th Edition, 2020.
* U.S. DOT Hazardous Materials Regulations (49 CFR Parts 171-180).
* IATA Dangerous Goods Regulations, 2023.
NEW QUESTION # 149
An infection preventionist (IP) is asked to monitor the use of preoperative antibiotics for patients undergoing hip replacement surgery. The IP should:
Answer: D
Explanation:
The Certification Study Guide (6th edition) emphasizes that effective monitoring of surgical antimicrobial prophylaxis focuses on process measures that are directly linked to prevention of surgical site infections (SSIs). For hip replacement surgery, one of the most critical evidence-based practices is the timely administration of prophylactic antibiotics, typically within the recommended time frame prior to surgical incision.
Monitoring the timing of prophylactic antibiotics allows the infection preventionist to assess compliance with nationally accepted standards and guidelines. Numerous studies cited in infection prevention literature, and reinforced in the study guide, demonstrate that inappropriate timing-either too early or after incision- significantly reduces the effectiveness of prophylaxis and increases SSI risk. Because timing is a modifiable process under the control of the surgical team, it represents a high-value performance indicator.
The other options are less appropriate. Reviewing antibiotic use only in patients who develop SSIs is retrospective and does not support prevention. Receiving daily pharmacy reports identifies antibiotic exposure but does not evaluate whether prophylaxis was administered correctly. Monitoring all postoperative antibiotic use does not specifically address preoperative prophylaxis and may dilute focus from the most critical prevention measure.
CIC exam questions frequently distinguish between process monitoring versus outcome review. In this scenario, monitoring the timing of prophylactic antibiotics aligns with best practices, supports targeted feedback to surgical teams, and directly contributes to SSI reduction.
Reference: Certification Study Guide (CBIC/CIC Exam Study Guide), 6th edition, Chapter 5: Preventing
/Controlling the Transmission of Infectious Agents; Chapter 4: Surveillance and Epidemiologic Investigation.
NEW QUESTION # 150
......
Real4Prep's products can not only help you successfully pass CBIC certification CIC Exams, but also provide you a year of free online update service, which will deliver the latest product to customers at the first time to let them have a full preparation for the exam. If you fail the exam, we will give you a full refund.
CIC Questions Pdf: https://www.real4prep.com/CIC-exam.html
DOWNLOAD the newest Real4Prep CIC PDF dumps from Cloud Storage for free: https://drive.google.com/open?id=149lePdyZX_lZZrF8A60DmKZnG3Wn8sNA