P.S. Free & New EFM dumps are available on Google Drive shared by ExamDumpsVCE: https://drive.google.com/open?id=1JeiZqQYcSFZQD3QhFBCkqaJoRm03ixDx
The NCC EFM exam questions are designed and verified by experienced and qualified NCC EFM exam trainers. They work together and share their expertise to maintain the top standard of NCC EFM Exam Practice test. So you can get trust on NCC EFM exam questions and start preparing today.
| Section | Weight | Objectives |
|---|---|---|
| Professional Issues | 5% | - Clinical Practice and Safety
|
| Fetal Assessment Methods | 9% | - Assessment Techniques
|
| Physiology | 11% | - Maternal-Fetal Physiology
|
| Electronic Monitoring Equipment | 5% | - Monitoring Systems
|
| Pattern Recognition and Intervention | 70% | - Maternal and Fetal Complications
|
>> Latest Braindumps EFM Book <<
All of these advantages, you can avail of after passing the EFM exam. You must find the best resource to prepare for the NCC EFM test if you want to pass the NCC EFM Certification Exam. Without proper NCC EFM exam preparation, getting success in the NCC EFM exam is impossible.
NEW QUESTION # 104
This fetal heart rate pattern is classified as Category III based on: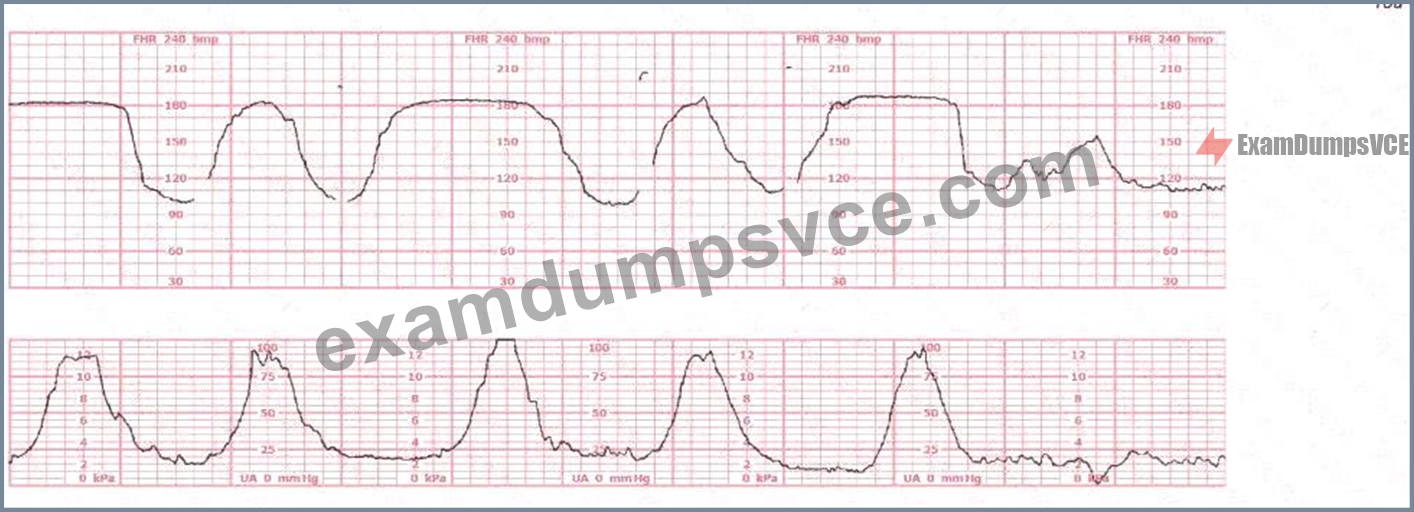
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
This tracing shows recurrent late decelerations accompanied by absent variability.
Per NICHD/NCC, a tracing is Category III if ANY of the following are present:
* Absent variability AND recurrent late decelerations
* Absent variability AND recurrent variable decelerations
* Absent variability AND bradycardia
* Sinusoidal pattern
In this strip:
* Variability is absent
* Decelerations are recurrent and late
The determining feature for the classification is absent variability, which indicates significant risk for fetal acidemia.
The contraction pattern (option B) does not determine category.
The deceleration type alone (option C) does not determine Category III without absent variability.
Thus, the classification is Category III because of absent variability.
References:NCC C-EFM Candidate Guide; NICHD Three-Tier System; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring.
NEW QUESTION # 105
A woman at 34-weeks gestation is in active labor after spontaneous rupture of membranes.
Accelerations should be documented as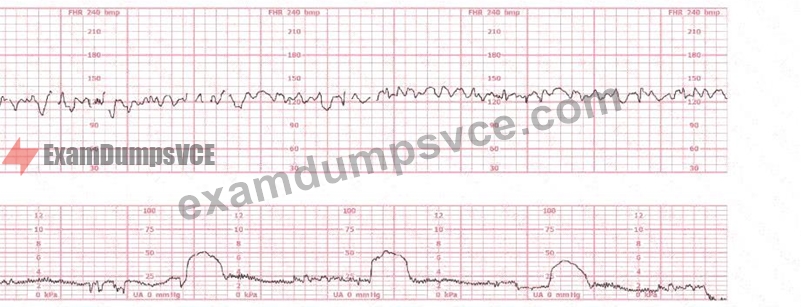
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract (No URLs)
For fetuses before 32-34 weeks, the National Certification Corporation (NCC) follows the physiologic standards established by AWHONN, Simpson & Creehan, Menihan, and Creasy & Resnik, which emphasize that preterm fetuses have less mature autonomic nervous system development, resulting in smaller and shorter accelerations.
According to the NCC C-EFM Exam Content Outline (Pattern Recognition & Intervention) and the AWHONN Fetal Heart Monitoring Principles (2022-2024):
* Preterm fetuses (<32 weeks) normally demonstrate 10 bpm × 10 sec accelerations.
* By approximately 32-34 weeks, accelerations may begin transitioning toward 15×15, but the accepted standard for documentation at 34 weeks remains 10×10, unless clearly meeting 15×15 criteria.
* NCC emphasizes using gestational-age-appropriate criteria for documenting accelerations, because autonomic reactivity increases gradually and is not fully comparable to term until after
32-34 weeks.
Menihan's Electronic Fetal Monitoring also states that preterm fetuses "should be evaluated with the
10×10 rule until it is clear that the fetus is demonstrating mature 15×15 acceleratory capacity." Simpson & Creehan reinforce this point, noting that accelerations in late preterm gestations "may not consistently reach 15 bpm for 15 seconds, and thus 10×10 remains the appropriate designation." Since the patient is 34 weeks, the fetus is late-preterm and may not reliably meet the full 15×15 criteria; therefore, the correct documentation standard remains 10×10.
Thus, accelerations should be charted as:
"Present 10×10."
References
* NCC C-EFM Candidate Guide 2025 - Content Domain: Pattern Recognition and Intervention
* AWHONN Fetal Heart Monitoring Principles & Practices, 2022-2024
* Menihan: Electronic Fetal Monitoring: Concepts and Applications
* Simpson & Creehan: Perinatal Nursing
* Miller: Fetal Monitoring Pocket Guide
* Creasy & Resnik: Maternal-Fetal Medicine
NEW QUESTION # 106
(Full question)
This tracing would be categorized as a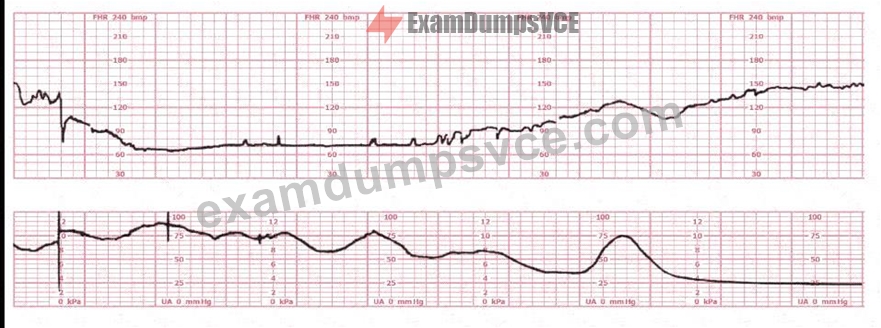
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract (No URLs):
According to AWHONN Fetal Heart Monitoring Principles & Practice, Simpson & Miller, and the NCC C-EFM Content Outline, fetal heart rate categories are assigned based on baseline, variability, presence
/absence of accelerations, and type of decelerations.
A Category II tracing includes any pattern that is not clearly normal (Category I) or clearly abnormal (Category III). Classic Category II features include:
* Bradycardia NOT accompanied by absent variability
* Tachycardia
* Minimal variability
* Marked variability
* Absence of accelerations after stimulation
* Recurrent variable decelerations with minimal or moderate variability
* Prolonged decelerations (#2 min but <10 min)
In this tracing, the fetus demonstrates:
- A prolonged deceleration with subsequent recovery,
- Presence of baseline variability,
- Return toward baseline but not immediately normal.
AWHONN and Simpson state that any prolonged deceleration automatically places the tracing in Category II unless variability is absent (which would escalate it to Category III). Because variability is present, it cannot be Category III.
Therefore, by NCC standards, this tracing is Category II.
NEW QUESTION # 107
The decelerations seen in the fetal monitoring tracing shown are best described as: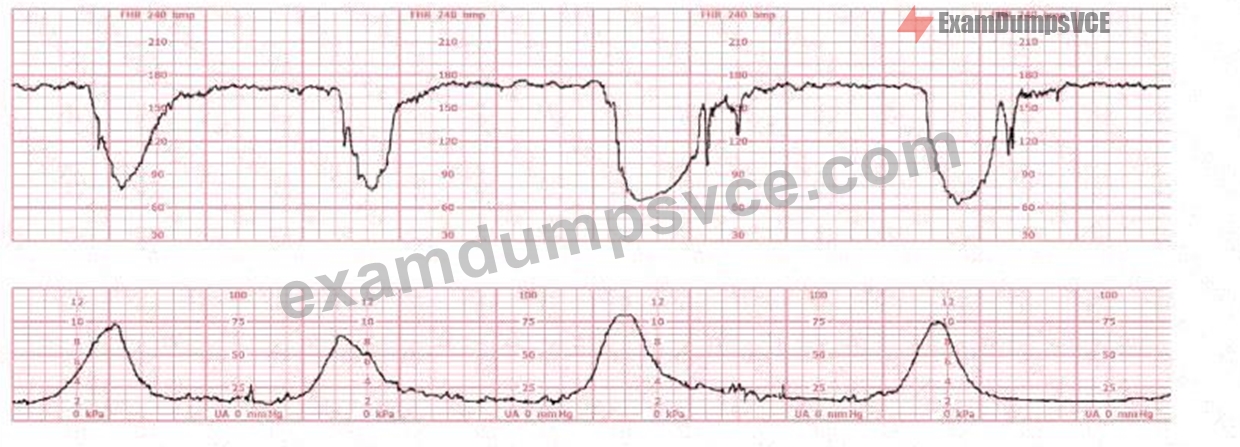
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
Accurate classification of decelerations requires evaluating their shape, onset, nadir, recovery, relationship to contractions, and variability characteristics. NCC uses the NICHD standardized definitions, reinforced across AWHONN, Miller's Pocket Guide, Menihan, Simpson, and Creasy & Resnik.
Key features in this tracing:
* Abrupt onsetThe FHR drops rapidly from baseline to nadir in less than 30 seconds-this is the defining hallmark of a variable deceleration per NICHD.
* Sharp V-shape and deep amplitudeThe tracing shows steep descents and ascents, characteristic of cord compression-type variable decelerations.
* Inconsistent timing with contractionsThe decelerations do not begin at the start of contractions (as early decelerations would) and do not consistently begin after the peak of contractions (as late decelerations would). Variable decelerations can occur before, during, or after a contraction-exactly what is demonstrated here.
* Rapid return to baselineAnother core feature of variable decelerations in NICHD/NCC definitions.
* No uniform contraction relationshipEarly decelerations are symmetrical and mirror contractions.
Late decelerations begin after the peak of the contraction. This strip does not match either pattern.
Differentiation per NCC-aligned definitions:
* Early Decelerations:Gradual onset (>30 sec), nadir mirrors contraction peak, shallow, uniform.Not present.
* Late Decelerations:Gradual descent, nadir after contraction peak, smooth shape.Not present.
* Variable Decelerations:Abrupt onset (<30 sec), variable timing, sharp V-shape, rapid recovery, often with shoulders.Exactly matches the tracing.
Therefore, according to NICHD/NCC criteria, the decelerations shown are variable decelerations.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline; NICHD Standardized Definitions; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 108
The most highly oxygenated blood in the fetal circulation is found in the
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract Sources:
In fetal physiology, the highest oxygen saturation exists in the umbilical vein, which then flows through the ductus venosus before entering the right atrium.
According to Creasy & Resnik Maternal-Fetal Medicine, and AWHONN physiologic foundations:
* The umbilical vein carries oxygen-rich blood from the placenta (approx. 80% saturation).
* Most of this blood bypasses the liver via the ductus venosus, which therefore contains the most highly oxygenated blood within the fetal circulatory system.
By contrast:
* The descending aorta contains mixed blood with significantly lower oxygen content due to mixing after passage through the ductus arteriosus.
* The pulmonary arteries in the fetus carry predominantly deoxygenated blood, since fetal lungs are fluid-filled and have high pulmonary vascular resistance.
Thus, the structure containing the highest fetal oxygen concentration is the ductus venosus.
References:Creasy & Resnik - Maternal Fetal Medicine;AWHONN Fetal Monitoring;Simpson & Miller - Fetal Monitoring Physiology;NCC C-EFM Content Outline - Physiology Domain.
NEW QUESTION # 109
......
Computers have made their appearance providing great speed and accuracy for our work. IT senior engine is very much in demand in all over the world. Now NCC EFM latest dumps files will be helpful for your career. ExamDumpsVCE produces the best products with high quality and high passing rate. Our valid EFM Latest Dumps Files help a lot of candidates pass exam and obtain certifications, so that we are famous and authoritative in this filed.
Latest EFM Test Simulator: https://www.examdumpsvce.com/EFM-valid-exam-dumps.html
BONUS!!! Download part of ExamDumpsVCE EFM dumps for free: https://drive.google.com/open?id=1JeiZqQYcSFZQD3QhFBCkqaJoRm03ixDx