P.S. Free & New EFM dumps are available on Google Drive shared by Real4dumps: https://drive.google.com/open?id=1_CgsnP8Jn2At_p4xCsc32B4tR7UfMHGm
NCC is one of the most powerful and rapidly growing fields nowadays. Everyone is trying to get the NCC EFM certification to improve their futures with it. Success in the test plays an important role in the up gradation of your CV and getting a good job or working online to achieve your dreams. The students are making up their minds for the NCC EFM test but they are mostly confused about where to prepare for it successfully on the first try. This confusion leads to choosing outdated material and ultimately failure in the test. The best way to avoid failure is using updated and real questions.
| Section | Objectives |
|---|---|
| Topic 1: Intrapartum Assessment and Monitoring | - External and internal monitoring techniques - Risk assessment during labor |
| Topic 2: Uterine Activity | - Tachysystole and abnormal contraction patterns - Normal uterine contraction patterns |
| Topic 3: Fetal Heart Rate Interpretation | - Category I, II, and III tracing interpretation - Accelerations and decelerations - Baseline rate and variability |
| Topic 4: Fetal Physiology and Oxygenation | - Oxygen transport and acid-base balance - Fetal cardiovascular physiology |
| Topic 5: Intrauterine Resuscitation and Interventions | - Fluid management and medication adjustments - Maternal position changes and oxygen administration |
| Topic 6: Maternal and Fetal Complications | - Hypoxia and uteroplacental insufficiency - High-risk obstetric conditions affecting fetal monitoring |
>> Valid EFM Test Pass4sure <<
Our EFM exam materials are formally designed for the exam. With its help, you don't have to worry about the exam any more for it almost guarantees you get what you want. If you think i'm exaggerating, you might as well take a look at our EFM Actual Exam. With a high pass rate as 98% to 100%, you will be bound to pass the exam. And our EFM training questions are popular in the market. We believe you will make the right choice.
NEW QUESTION # 23
The pattern on the fetal heart rate tracing shown is likely due to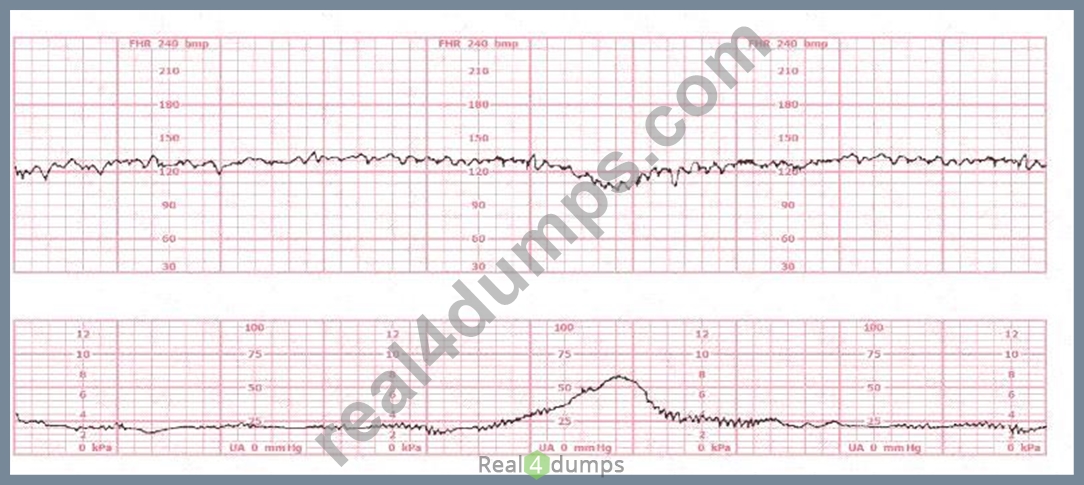
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract Sources:
The tracing demonstrates an abrupt-onset, sharp, V-shaped deceleration, occurring simultaneously with or slightly after a contraction-classic for variable decelerations, which are caused by umbilical cord compression.
According to AWHONN Fetal Heart Monitoring Principles & Practices, variable decelerations are defined by:
* "Abrupt decreases in FHR below baseline of at least 15 bpm, lasting at least 15 seconds and less than 2 minutes."
* "Most commonly associated with umbilical cord compression, whether transient or recurrent." Physiology reference (Simpson & Miller, Pocket Guide):
* Compression of the umbilical vein causes a brief acceleration.
* Compression of the umbilical arteries triggers a vagal response, producing a rapid deceleration.
* This creates the characteristic sharp 'V', 'U', or 'W' shape on the monitor.
Placental insufficiency (Choice B) produces late decelerations, which are gradual, not abrupt.
Fetal head compression (Choice A) produces early decelerations, which mirror contractions and have a gradual pattern.
Thus, the tracing is most consistent with variable decelerations caused by umbilical cord compression.
References:AWHONN Fetal Heart Monitoring Principles & Practices;Simpson - Fetal Monitoring;Menihan
- Electronic Fetal Monitoring;Miller's EFM Pocket Guide;NCC C-EFM Content Outline - Pattern Recognition Domain.
NEW QUESTION # 24
A pattern of recurrent variable decelerations would move from Category II to Category III if what fetal heart rate change occurs?
Answer: C
NEW QUESTION # 25
A woman is admitted at 41-weeks gestation for fetal evaluation following a motor vehicle accident. She reports that she hit her abdomen on the steering wheel. The underlying physiology of the tracing is most likely: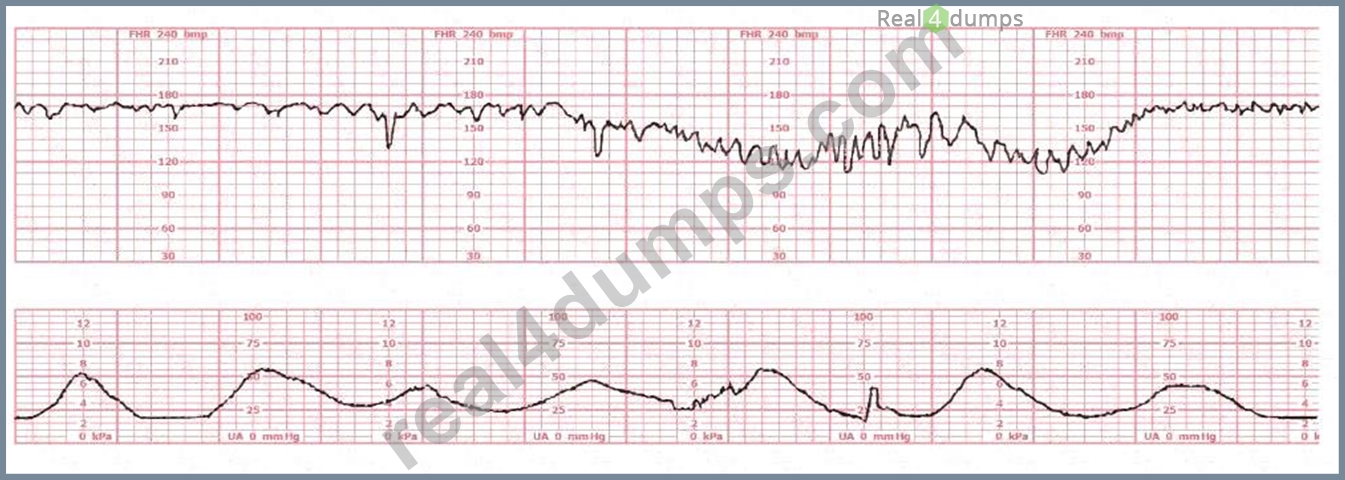
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
This tracing shows recurrent late decelerations, decreased variability, and subtle baseline shifts-findings that strongly correspond to uteroplacental insufficiency. In trauma cases, NCC emphasizes that placental abruption is the most common fetal complication, caused by shearing forces separating the placenta from the uterine wall.
Key physiologic points per NCC/AWHONN/Menihan:
* Maternal blunt abdominal trauma frequently leads to partial or concealed abruption.
* Abruption produces decreased uteroplacental blood flow, resulting in:
* Late decelerations
* Minimal/absent variability
* Baseline shifts or instability
Cord accident (option A) typically produces variable decelerations, not late-pattern decelerations.
Fetal trauma (option B) is extremely rare and does not produce a consistent deceleration pattern.
Thus, the physiology most consistent with this tracing and mechanism of injury is placental abruption.
References:NCC C-EFM Candidate Guide (2025); NCC Physiology Domain; AWHONN Fetal Heart Monitoring Principles & Practices; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 26
Stimulation of the vagus nerve in a healthy fetus will cause:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
Vagal stimulation is part of the parasympathetic nervous system, which causes:
* Slowing of the fetal heart rate (FHR)
* Rapid but temporary changes in HR
* Seen with head compression, scalp stimulation, or fetal movement
NICHD/NCC physiology explains:
* Vagus nerve activation # acetylcholine release # slowed SA node firing # decrease in FHR
* This mechanism is responsible for early decelerations during labor due to head compression.
Why the incorrect answers are wrong:
* B. Increased cardiac contractility # sympathetic effect, not vagal.
* C. Increased fetal blood pressure # also a sympathetic effect.
Correct answer: A. Decreased fetal heart rate
References:NCC Candidate Guide; AWHONN FHMPP; Menihan; Miller's Pocket Guide; Simpson & Creehan.
NEW QUESTION # 27
The tracing shown is a: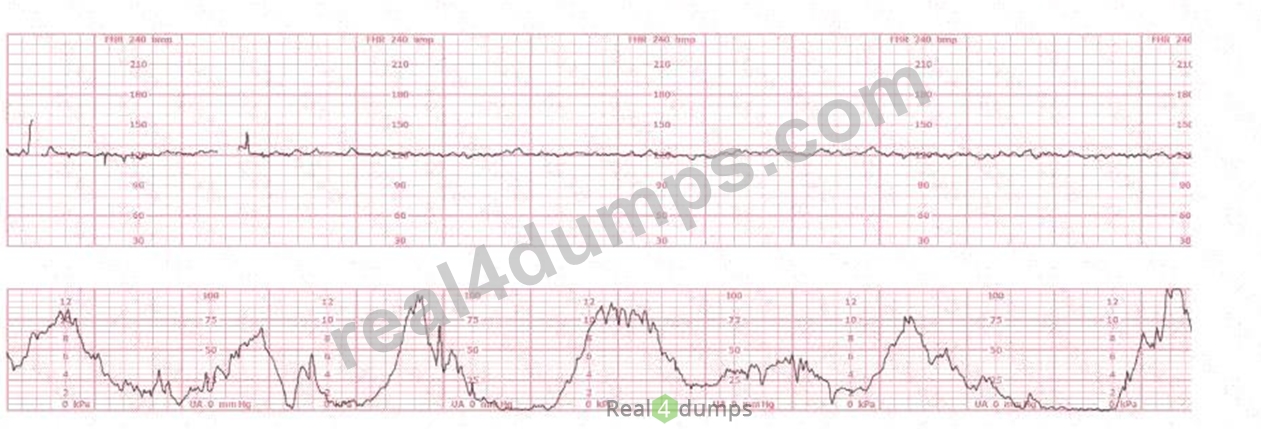
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References (No URLs):
Interpretation of fetal heart rate (FHR) tracings in the NCC C-EFM exam follows the standardized NICHD three-tier classification, which is fully adopted in NCC's content outline and recommended references such as AWHONN Fetal Heart Monitoring Principles & Practices, Miller's EFM Pocket Guide, Menihan, Simpson' s Perinatal Nursing, and Creasy & Resnik.
Baseline:
The tracing demonstrates an FHR baseline around 145-150 bpm, which falls within the normal range of 110-
160 bpm. NCC references define baseline as the mean FHR rounded to increments of 5 bpm over a 10-minute window.
Variability:
The strip shows minimal variability, with amplitude fluctuations approximately 0-2 bpm.
According to NCC-aligned definitions:
* Moderate variability: 6-25 bpm
* Minimal variability: 1-5 bpm
* Absent variability: undetectable amplitude
This tracing shows minimal variability, not moderate, so it cannot be Category I.
Accelerations:
No accelerations are present. Lack of accelerations alone does not classify the tracing as Category III.
Decelerations:
There are no recurrent late decelerations, no recurrent variable decelerations, and no prolonged decelerations. Without these, and with minimal variability, the tracing does not meet Category III criteria.
Category III criteria (per NICHD/NCC):
Must include at least one of the following:
* Absent variability with recurrent late decelerations
* Absent variability with recurrent variable decelerations
* Absent variability with bradycardia
* Sinusoidal pattern
None of these are present.
Category II criteria (per NICHD/NCC):
Category II includes tracings that are not Category I or III.
Examples specifically listed include:
* Minimal variability
* Absent accelerations after fetal stimulation
* Tachycardia
* Bradycardia without absent variability
* Variable or late decelerations occurring intermittently
Because this tracing shows minimal variability, a normal baseline, no accelerations, and no recurrent decelerations, it fits squarely into Category II.
Therefore, the correct classification is Category II.
References:NCC C-EFM Candidate Guide and Content Outline (2025); AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine; NICHD Three-Tier FHR Interpretation System.
NEW QUESTION # 28
......
On a regular basis, we update the PDF version to improve the EFM Questions and accurately reflect any changes that have been made to the test content. We know that Certified - Electronic Fetal Monitoring (EFM) certification exam costs can be high, with registration fees often running between $100 and $1000. We provide a free demo version of our product to ensure you are completely satisfied with our NCC Certification Exams preparation material. The purpose of this free demo is to help you make a well-informed decision.
Exam EFM Flashcards: https://www.real4dumps.com/EFM_examcollection.html
BONUS!!! Download part of Real4dumps EFM dumps for free: https://drive.google.com/open?id=1_CgsnP8Jn2At_p4xCsc32B4tR7UfMHGm