BONUS!!! Download part of ExamsTorrent EFM dumps for free: https://drive.google.com/open?id=1OZxjx71lXUSZaEKZfKPNugvnAmK3UyEu
The ExamsTorrent EFM exam questions are being offered in three different formats. These formats are EFM PDF dumps files, desktop practice test software, and web-based practice test software. All these three EFM exam dumps formats contain the Real EFM Exam Questions that assist you in your Certified - Electronic Fetal Monitoring practice exam preparation and finally, you will be confident to pass the final Certified - Electronic Fetal Monitoring (EFM) exam easily.
| Section | Weight | Objectives |
|---|---|---|
| Physiology | 11% | - Fetal cardiovascular physiology - Uteroplacental function - Factors affecting fetal oxygenation |
| Electronic Monitoring Equipment | 5% | - Calibration and accuracy - Troubleshooting artifacts - Proper application and use |
| Professional Issues | 5% | - Safety and quality improvement - Documentation standards - Legal and ethical aspects |
| Pattern Recognition and Intervention | 70% | - Tracing evaluation and management - Clinical decision-making and interventions - Interpretation per NICHD standards - Fetal heart rate patterns classification |
| Fetal Assessment and Methods | 9% | - Auxiliary assessment techniques - Correlation with clinical status - Indications for monitoring |
We believe that if you trust our EFM exam simulator and we will help you obtain EFM certification easily. After purchasing, you can receive our EFM training material and download within 10 minutes. Besides, we provide one year free updates of our EFM learning guide for you and money back guaranteed policy so that we are sure that it will give you free-shopping experience. Now choose our EFM practic braindump, you will not regret.
NEW QUESTION # 23
Maternal fever can cause fetal tachycardia because the increased maternal temperature:
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
Maternal hyperthermia-most commonly from infection-causes a rise in fetal temperature, which increases fetal metabolic rate. The fetus responds by increasing heart rate to meet the increased oxygen demand.
Effects include:
* Increased fetal oxygen consumption
* Enhanced fetal cardiac output
* Resultant tachycardia, often 160-180 bpm
This mechanism is repeatedly outlined in NCC's physiology domain, AWHONN, Menihan, Simpson, and Creasy & Resnik.
Option A is incorrect because maternal fever does not reduce perfusion.
Option C is incorrect because catecholamines are often elevated, not inhibited.
Thus, the mechanism is increased fetal metabolism.
References:NCC C-EFM Candidate Guide; NCC Physiology Domain; AWHONN Fetal Heart Monitoring Principles & Practices; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy
& Resnik Maternal-Fetal Medicine.
NEW QUESTION # 24
A woman at 38-weeks gestation is admitted to labor and delivery following a fall down the stairs three hours ago. She started feeling contractions in the ambulance. The fetal heart rate tracing shown is on initial evaluation and represents 25 minutes. This tracing is most consistent with a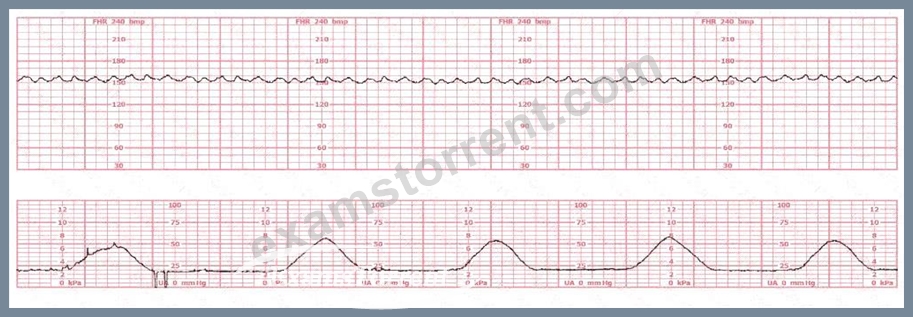
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract without any URL or Links According to the NCC C-EFM 2025 Candidate Guide, Pattern Recognition and Intervention requires the candidate to classify fetal heart rate (FHR) patterns using the NICHD 2008 three-tier system, which NCC endorses across all recommended resources (AWHONN Fetal Heart Monitoring Principles and Practices, Menihan Electronic Fetal Monitoring, Simpson & Creasy, Miller's Pocket Guide).
A Category II tracing is defined as "indeterminate" and includes any FHR pattern that is not Category I and not Category III. NCC references indicate that Category II may include:
* Minimal or marked variability
* Absence of accelerations after fetal stimulation
* Recurrent variable decelerations with moderate variability
* Prolonged decelerations lasting 2-10 minutes
* Baseline tachycardia or bradycardia without absent variability
In the tracing provided:
* The baseline FHR is approximately 135-145 bpm, within normal limits.
* Moderate variability is not consistently present; variability is borderline minimal-moderate at times.
* No significant accelerations are seen over the 25-minute evaluation period.
* No recurrent late or prolonged decelerations are present.
* There are occasional subtle variable-type dips, but not enough to meet criteria for Category III.
NCC-endorsed texts (such as AWHONN and Menihan) state that a tracing with minimal variability for less than 40 minutes and without recurrent decelerations is Category II, as it fails to meet the requirements for Category I (must have moderate variability and accelerations absent decelerations) and lacks the criteria for Category III (must have absent variability with recurrent late decels, recurrent variable decels, bradycardia, or sinusoidal pattern).
Therefore, this pattern is indeterminate, consistent with Category II, and requires continued surveillance and evaluation, which aligns with NCC-recommended clinical decision-making competencies.
NEW QUESTION # 25
A 20-year-old woman (G1P0) at 40-weeks gestation was admitted for cervical ripening with dinoprostone (Cervidil) four hours ago. She developed the pattern shown one hour ago. She has been changed to a lateral position and given a fluid bolus, and the pattern continues. An appropriate intervention would be to: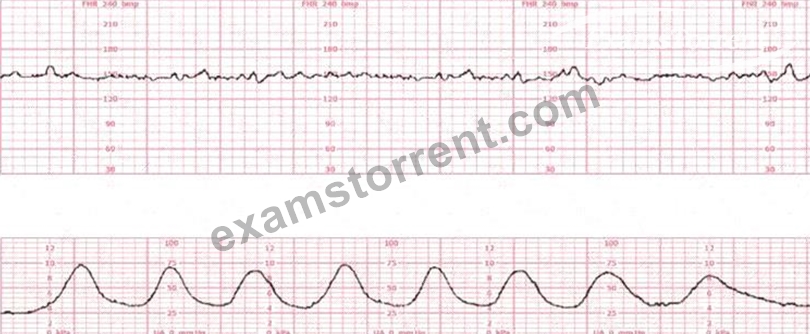
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The tracing shows tachysystole (more than 5 contractions in 10 minutes) with minimal variability and recurrent decelerations consistent with uteroplacental insufficiency caused by excessive uterine activity.
Dinoprostone (Cervidil) is a uterotonic prostaglandin, and one of its known complications is uterine tachysystole with Category II or III fetal heart rate patterns.
NCC/AWHONN guidance for tachysystole caused by prostaglandins:
* FIRST intervention: Remove the dinoprostone insert.
* Reposition the patient (already done).
* IV fluid bolus (already done).
* Consider terbutaline only if tachysystole persists after removal of the agent.
Since maternal repositioning and IV fluids have already failed, the next step is to remove the cervical ripening agent.
Why other answers are incorrect:
* A. Continue to observe - Never acceptable with tachysystole + fetal intolerance.
* B. Terbutaline - May be used after prostaglandin removal, not before.
Thus, the correct answer is C. Remove the dinoprostone insert.
References:NCC C-EFM Candidate Guide; AWHONN Fetal Heart Monitoring Principles & Practices; Menihan; Miller's Pocket Guide; NICHD Definitions; Creasy & Resnik.
NEW QUESTION # 26
(Full question statement)
Interobserver reliability in interpretation of fetal heart rate tracings is greatest when the tracing is:
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract Without Links:
NCC examination standards and AWHONN clearly state that normal Category I patterns have the highest interobserver agreement because they contain objective, easily identifiable components:
* baseline 110-160 bpm
* moderate variability
* absence of late or variable decelerations
* presence or absence of accelerations
Simpson highlights that Category II tracings have poor reliability due to multiple combinations of variability and decelerations, while Category III patterns have higher agreement but occur far less frequently, limiting reliability measures.
Research cited within NCC-endorsed materials confirms that clinicians demonstrate the greatest agreement in identifying normal Category I patterns, making normal the correct answer.
NEW QUESTION # 27
Nonstress testing is used more frequently for antepartum testing than contraction stress testing because contraction stress testing has a:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
NCC and AWHONN explain that Contraction Stress Testing (CST):
* Has a higher rate of equivocal ("equivocal-suspicious" or "equivocal-hyperstimulation") results
* Frequently must be repeated or replaced with other tests
* Requires inducing contractions, which carries risk (hyperstimulation, preterm labor, uterine rupture in scarred uterus) NST is used more commonly because it is:
* Noninvasive
* Easier to perform
* Has fewer contraindications
* Has a lower rate of equivocal results
Why the others are incorrect:
* B - CST does detect fetal compromise reliably and is NOT limited in its reporting structure.
* C - A negative CST actually has very high negative predictive value for 7 days, making this answer incorrect.
Thus the correct choice is A. Higher frequency of equivocal results.
References:NCC C-EFM Candidate Guide; AWHONN; Menihan; Simpson & Creehan; Creasy & Resnik.
NEW QUESTION # 28
......
One of the top features of NCC EFM exam dumps is the EFM exam passing a money-back guarantee. In other words, your investments with NCC EFM exam questions are secured with the 100 Certified - Electronic Fetal Monitoring EFM exam passing a money-back guarantee. Due to any reason, if you did not succeed in the final NCC EFM exam despite using NCC EFM PDF Questions and practice tests, we will return your whole payment without any deduction. While practicing on Certified - Electronic Fetal Monitoring EFM practice test software you will experience the real-time Certified - Electronic Fetal Monitoring EFM exam environment for preparation. This will help you to understand the pattern of final NCC EFM exam questions and answers.
Valid EFM Test Syllabus: https://www.examstorrent.com/EFM-exam-dumps-torrent.html
2026 Latest ExamsTorrent EFM PDF Dumps and EFM Exam Engine Free Share: https://drive.google.com/open?id=1OZxjx71lXUSZaEKZfKPNugvnAmK3UyEu