BTW, DOWNLOAD part of Exams4Collection EFM dumps from Cloud Storage: https://drive.google.com/open?id=1v5gNQ0QRLVOYjPlr5tLSfvVYNShQZzLF
When candidates decide to pass the EFM exam, the first thing that comes to mind is to look for a study material to prepare for their exam. The most people will consider that choose EFM question torrent, because it has now provided thousands of online test papers for the majority of test takers to perform simulation exercises, helped tens of thousands of candidates pass the EFM Exam, and got their own dream industry certificates. That is to say, there is absolutely no mistake in choosing our EFM test guide to prepare your exam, you will pass your exam in first try and achieve your dream soon.
| Section | Objectives |
|---|---|
| Uterine Activity | - Tachysystole and abnormal contraction patterns - Normal uterine contraction patterns |
| Intrapartum Assessment and Monitoring | - External and internal monitoring techniques - Risk assessment during labor |
| Fetal Heart Rate Interpretation | - Accelerations and decelerations - Category I, II, and III tracing interpretation - Baseline rate and variability |
| Intrauterine Resuscitation and Interventions | - Maternal position changes and oxygen administration - Fluid management and medication adjustments |
| Fetal Physiology and Oxygenation | - Fetal cardiovascular physiology - Oxygen transport and acid-base balance |
| Maternal and Fetal Complications | - High-risk obstetric conditions affecting fetal monitoring - Hypoxia and uteroplacental insufficiency |
>> EFM New Braindumps Questions <<
Our EFM exam braindumps are famous for the advantage of high-efficiency and high-effective. And it is proved by the high pass rate. The 99% pass rate is a very proud result for us. If you join, you will become one of the 99% to pass the EFM Exam and achieve the certification. Believe in yourself, you can do it! Buy EFM study guide now and we will help you. Believe it won't be long before, you are the one who succeeded!
NEW QUESTION # 122
The fetal heart rate baseline is
Answer: C
Explanation:
Comprehensive and Detailed Explanation (From NCC C-EFM-Referenced Sources) The NCC C-EFM exam outline, along with AWHONN and Miller's Pocket Guide, define baseline fetal heart rate as the mean FHR rounded to increments of 5 bpm, measured over a 10-minute window, excluding:
* accelerations
* decelerations
* periods of marked variability
* any segments differing by >25 bpm
This aligns with ACOG, AWHONN, and Simpson's interpretation standards.
Option A is incorrect: the baseline is not documented as a 15-bpm range; it is documented as a single value (e.g., 140 bpm).
Option C is incorrect: the correct NCC/ACOG standardized normal baseline is 110-160 bpm, not 170.
Exact Extract Concepts Referenced:
- "Baseline is determined over a 10-minute period excluding periodic or episodic changes." (AWHONN FHR Principles)
- "Baseline is the mean FHR rounded to 5-bpm increments." (Miller's Pocket Guide)
- "Normal baseline is 110-160 bpm." (Simpson & Menihan; Creasy & Resnik)
NEW QUESTION # 123
A woman has been 5 cm dilated for the past 3 hours. The tracing shown has developed over the last 30 minutes. The best initial course of action is to: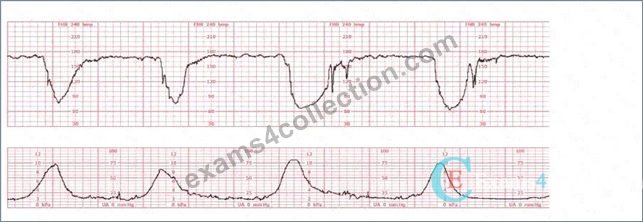
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The fetal heart rate tracing demonstrates recurrent deep variable decelerations with a rapid drop in FHR, a V-shaped pattern, and slow return to baseline. These are classic signs of cord compression. According to NCC, AWHONN, Miller, Menihan, and Simpson, recurrent variable decelerations require immediate intrauterine resuscitative interventions before any decision regarding operative birth.
NCC-aligned intervention steps include:
* Maternal repositioning (first-line for cord compression)
* Reducing or stopping oxytocin if infusing
* IV fluid bolus
* Amnioinfusion (if appropriate and recurrent deep variables persist)
* Oxygen only if other measures fail (per NCC/AWHONN updated guidance)
The cervix has remained unchanged at 5 cm for 3 hours (a prolonged latent or early active labor pattern), but the fetal tracing shows Category II-recurrent variable decelerations. Category II dictates corrective action, not immediate delivery unless it progresses to Category III.
Cesarean birth (option C) is reserved for:
* Persistent Category III
* Failure of intrauterine resuscitation
* Proven fetal intoleranceNone of these conditions have been met yet.
Thus, the correct initial management is B. Perform intrauterine resuscitative measures.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline; NICHD FHR Definitions; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 124
This tracing reflects: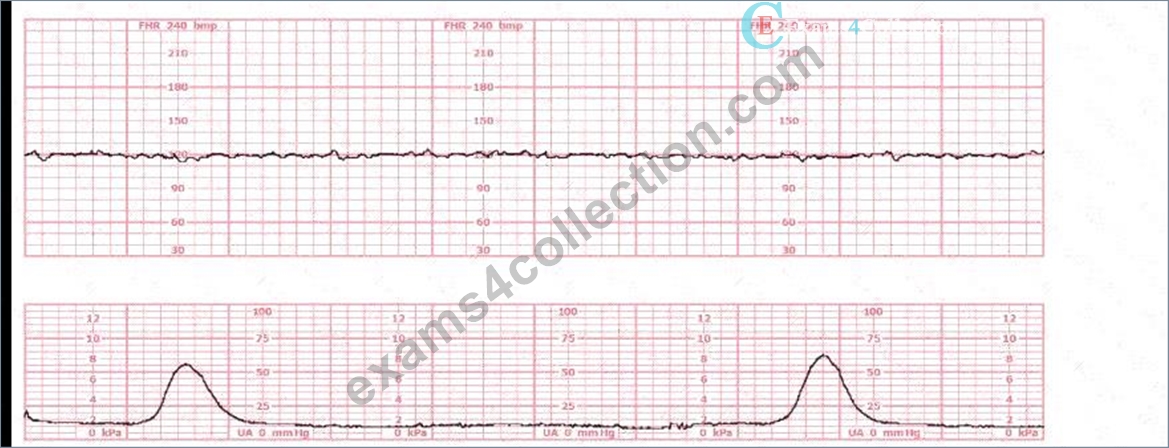
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
In NCC C-EFM interpretation, classification of a fetal heart tracing is based on NICHD's three-tier system:
Category I, II, and III. Category III represents an abnormal tracing requiring immediate evaluation and prompt intervention.
Key findings in this tracing:
* Baseline:Baseline is approximately 140 bpm, within the normal range (110-160 bpm).Baseline alone does not determine category.
* Variability:The tracing shows absent variability:
* No beat-to-beat oscillations
* Flat, minimal fluctuationNICHD and NCC define absent variability as amplitude range undetectable.
* Accelerations:No accelerations are present.
* Decelerations:The strip does not show decelerations or bradycardia.However, absent variability alone with no accelerations for 20 minutes is highly concerning.
Category Classification per NICHD/NCC:
Category III criteria include ANY of the following:
* Absent variability with recurrent late decelerations
* Absent variability with recurrent variable decelerations
* Absent variability with bradycardia
* Sinusoidal pattern
Also recognized as Category III:
* Persistent absent variability lasting #20 minutes with no accelerations, which is strongly suggestive of fetal acidemia when sustained.
This tracing shows:
* Absent variability (flat line)
* No accelerations
* Persisting over an extended period
Under NCC and AWHONN guidance:
A persistently flat tracing must be classified as Category III unless proven otherwise (e.g., fetal sleep, maternal medications), and it requires immediate intrauterine resuscitation and evaluation for potential expedited delivery.
Why Category I is NOT correct:
Category I requires:
* Moderate variability
* No late or variable decelerationsThis tracing does not have moderate variability.
Why Category II is NOT correct:
Category II includes minimal variability, marked variability, intermittent variables/lates, absence of accelerations after stimulation.
This tracing is worse than Category II because variability is absent, not minimal.
Thus, the tracing fits Category III.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline; NICHD Three-Tier FHR Interpretation System; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 125
A fetus displays a baseline heart rate of 125 beats per minute with moderate variability. During a contraction, the baseline rate drops abruptly to 80 beats per minute with gradual return to baseline over 90 seconds. This is classified as:
Answer: A
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
NICHD definitions:
A variable deceleration is identified by:
* Abrupt onset(drop from baseline to nadir in <30 seconds)
* Depth #15 bpm
* Duration #15 seconds and <2 minutes
* Variable timing relative to contractions
* Variable shape (sharp drop, jagged descents, rapid recovery)
The scenario describes:
* Abrupt drop from 125 # 80 bpm (rapid onset)
* Lasting 90 seconds (still <2 minutes)
* Gradual return but still within variable range
* Occurring during a contraction
* Depth >15 bpm
This meets ALL criteria for a variable deceleration.
Why the other options are wrong:
* A. Early deceleration
* Requires gradual onset (>30 seconds).
* Mirrors contraction shape.
* Caused by head compression.
* This decel is abrupt, so NOT early.
* B. Prolonged deceleration
* Requires #2 minutes and <10 minutes.
* This decel lasts 90 seconds, which is below the threshold.
Correct classification: Variable deceleration.
References:NICHD FHR Definitions; NCC Pattern Recognition Domain; AWHONN FHMPP; Menihan; Simpson & Creehan.
NEW QUESTION # 126
When accelerations precede a variable deceleration pattern, this is caused by
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract (No URLs or Links) NCC-recommended physiologic texts (AWHONN, Menihan, Simpson, Creasy & Resnik) explain that variable decelerations are caused by umbilical cord compression. This process occurs in a three-step sequence, well known in fetal monitoring physiology:
* Umbilical vein occlusion occurs first # decreases fetal venous return # brief fetal acceleration (a compensatory sympathetic response).
* Umbilical artery occlusion follows # increases fetal systemic vascular resistance # variable deceleration as vagal stimulation lowers the fetal heart rate.
* Release of compression # post-deceleration acceleration may occur.
Thus, an acceleration immediately before a variable deceleration represents the initial compression of the umbilical vein, not a hypoxic response. This is a normal physiologic response to transient cord compression, often described in AWHONN and Menihan's physiologic explanation of "shoulders" around variable decelerations.
Oligohydramnios can contribute to cord compression but does not explain accelerations preceding the deceleration. A "hypoxic reflex" would not produce a pre-deceleration acceleration.
Therefore, the correct physiologic cause is:
Umbilical vein occlusion.
References (No URLs)
* NCC C-EFM Candidate Guide 2025 - Physiology
* AWHONN Fetal Heart Monitoring Principles
* Menihan: Electronic Fetal Monitoring
* Simpson & Creehan: Perinatal Nursing
* Creasy & Resnik: Maternal-Fetal Medicine
NEW QUESTION # 127
......
They work together and put all their expertise to ensure the top standard of Channel Partner Program Certified - Electronic Fetal Monitoring EFM valid dumps. Now the Certified - Electronic Fetal Monitoring EFM exam dumps have become the first choice of NCC EFM Exam candidates. With the top-notch and updated NCC EFM test questions you can pass your Certified - Electronic Fetal Monitoring EFM exam successfulily
Latest EFM Test Pdf: https://www.exams4collection.com/EFM-latest-braindumps.html
P.S. Free & New EFM dumps are available on Google Drive shared by Exams4Collection: https://drive.google.com/open?id=1v5gNQ0QRLVOYjPlr5tLSfvVYNShQZzLF