What's more, part of that ValidExam EFM dumps now are free: https://drive.google.com/open?id=1nfks5Ot6ML5FQen6NQ_CrhOJpJeMqlok
People always do things that will benefit them, so as get a certificate of the EFM test dumps. Obtaining a certificate means more opportunity, a good job, a better salary, and a bright. The benefits are numerous, and we give you a quicker method to achieve this. Our EFM Questions and answers list the knowledge point for you, and you just need to speed some of your time to practice. We are pass guarantee and money back guarantee. And the pass rate is98.
| Section | Weight | Objectives |
|---|---|---|
| Fetal Assessment Methods | 9% | - Assessment Techniques
|
| Physiology | 11% | - Maternal-Fetal Physiology
|
| Electronic Monitoring Equipment | 5% | - Monitoring Systems
|
| Pattern Recognition and Intervention | 70% | - Maternal and Fetal Complications
|
| Professional Issues | 5% | - Clinical Practice and Safety
|
>> EFM Current Exam Content <<
If you are a workman and you want to pass EFM exam quickly, ValidExam will be your best choice. EFM dumps and answers from our ValidExam site are all created by the IT talents with more than 10-year experience in IT certification. It can not only save your time, but also help you pass the EFM Exam easily.
NEW QUESTION # 35
Prenatal diagnosis shows that a fetus has renal agenesis. During delivery, what type of electronic fetal heart rate pattern is most likely to be seen due to a common complication associated with this syndrome?
Answer: B
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
Renal agenesis # severe oligohydramnios (due to absent fetal urine production).
Oligohydramnios causes:
* Cord compression
* Recurrent variable decelerations
* Possible prolonged decels from cord entrapment
This is one of the hallmark FHR complications in renal agenesis.
Why the other options are incorrect:
* A. Heart block - associated with maternal autoimmune antibodies, not renal anomalies.
* B. Late decelerations - associated with uteroplacental insufficiency, not fluid deficiency.
Correct answer: C. Variable decelerations.
References:NCC Physiology & Pattern Recognition; AWHONN FHMPP; Menihan; Simpson & Creehan; Creasy & Resnik.
NEW QUESTION # 36
During amnioinfusion, the infusion should be stopped periodically to assess changes in:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
During amnioinfusion, NCC emphasizes monitoring for uterine overdistention, which can lead to uterine hypertonus, uterine rupture, or placental separation. The primary way to evaluate overdistention is by measuring baseline uterine pressure via IUPC.
* Rising resting tone (>20-25 mmHg) indicates accumulating fluid and risk.
* Stopping the infusion intermittently allows recalibration and assessment of uterine baseline pressure.
* Contraction pattern (option B) is important but not the primary safety parameter.
* Pain (option C) is nonspecific and not a reliable indicator of uterine overdistention.
Thus, the infusion is stopped to assess baseline uterine pressure.
References:NCC C-EFM Candidate Guide; AWHONN Fetal Heart Monitoring Principles & Practices; Miller' s Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring.
NEW QUESTION # 37
Sustained fetal supraventricular tachycardia that goes untreated is most likely to result in:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
Sustained fetal supraventricular tachycardia (SVT) often produces heart rates > 200-240 bpm, causing:
* Poor ventricular filling
* Decreased stroke volume
* Reduced cardiac output
* Congestive heart failure
* Progressive fluid accumulation
NCC and AWHONN emphasize that untreated SVT leads to hydrops fetalis, characterized by:
* Ascites
* Pleural effusion
* Pericardial effusion
* Skin edema
Why the other answers are incorrect:
* A. Fetal anemia - Causes tachycardia but is not caused by SVT.
* C. Neonatal pacemaker - Pacemakers treat heart block, not SVT.
Correct answer: B. Hydrops fetalis
References:NCC C-EFM Candidate Guide; AWHONN Principles & Practices; Simpson & Creehan; Creasy
& Resnik Maternal-Fetal Medicine.
NEW QUESTION # 38
Based on the fetal heart rate tracing shown, the expected fetal pH would be: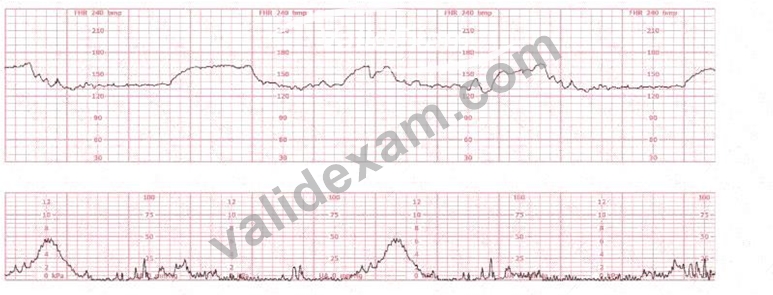
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
Assessment of likely fetal acid-base status is grounded in NCC-aligned principles that correlate fetal pH with fetal heart rate patterns, especially variability, presence/absence of accelerations, and type and depth of decelerations.
This tracing shows the following features:
Baseline:
The fetal heart rate baseline is approximately 140-150 bpm, within the normal 110-160 bpm range.
Variability:
Moderate variability is present-approximately 6-25 bpm amplitude.
Per NCC and NICHD definitions, moderate variability is strongly associated with normal fetal oxygenation and normal fetal pH > 7.20-7.25.
Accelerations:
There are occasional small accelerations, another strong indicator of normal fetal acid-base status.
Decelerations:
The tracing shows occasional variable decelerations, shallow and brief, recovering rapidly, typical of intermittent cord compression.
NCC references emphasize that intermittent, non-recurrent variables with moderate variability do not correlate with acidemia.
Uterine activity:
Contractions are present but not excessive, and fetal response remains reassuring.
Correlating tracing features with fetal pH (per NCC, AWHONN, Simpson, Menihan):
Moderate variability is the strongest intrapartum indicator of normal fetal pH.
The NICHD/NCC consensus repeatedly states that:
"The presence of moderate variability reliably predicts adequate fetal oxygenation and a fetal pH above the threshold associated with metabolic acidemia." Fetal pH below 7.15 is associated with:
Absent variability
Recurrent late decelerations
Recurrent deep variable decelerations
Prolonged bradycardia
None are present in this tracing.
Because the tracing demonstrates moderate variability, intermittent uncomplicated variables, and no recurrent late decelerations, the physiologic expectation is that the fetal pH remains normal, significantly above 7.15.
Therefore, the correct answer is: A (above 7.15).
References:
NCC C-EFM Candidate Guide (2025); NCC Content Outline; NICHD Interpretation System; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 39
The baseline fetal heart rate decreases with gestational age as a result of an increase in:
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
As gestation advances:
* Vagal (parasympathetic) control increases,
* Sympathetic dominance decreases,
* Resulting in a lower baseline heart rate.
NCC physiology teaching:
"Baseline FHR decreases with advancing gestational age due to maturation and increasing parasympathetic tone." Why the others are incorrect:
* Catecholamines increase heart rate, not decrease it.
* Intrinsic ventricular rate does not change significantly with gestational age.
Thus, the correct physiologic factor is increased parasympathetic tone.
References:NCC Physiology Domain; AWHONN; Menihan; Simpson & Creehan; Creasy & Resnik.
NEW QUESTION # 40
......
We provide online customer service to the customers for 24 hours per day and we provide professional personnel to assist the client in the long distance online. If you have any questions and doubts about the Certified - Electronic Fetal Monitoring guide torrent we provide before or after the sale, you can contact us and we will send the customer service and the professional personnel to help you solve your issue about using EFM Exam Materials. The client can contact us by sending mails or contact us online. We will solve your problem as quickly as we can and provide the best service. Our after-sales service is great as we can solve your problem quickly and won’t let your money be wasted. If you aren’t satisfied with our EFM exam torrent you can return back the product and refund you in full.
EFM New Soft Simulations: https://www.validexam.com/EFM-latest-dumps.html
BTW, DOWNLOAD part of ValidExam EFM dumps from Cloud Storage: https://drive.google.com/open?id=1nfks5Ot6ML5FQen6NQ_CrhOJpJeMqlok