2026 Latest ActualTestsIT CIC PDF Dumps and CIC Exam Engine Free Share: https://drive.google.com/open?id=1438_kBddSnGCvZqo6benvvaZH97aS7Kf
Do you want to earn the CBIC CIC certification to land a well-paying job or a promotion? Prepare with CIC real exam questions to crack the test on the first try. We offer our CBIC Certified Infection Control Exam (CIC) Dumps in the form of a real CIC Questions PDF file, a web-based CBIC CIC Practice Questions, and CIC desktop practice test software. Now you can clear the CBIC Certified Infection Control Exam test in a short time without wasting time and money with actual CIC questions of ActualTestsIT.
| Section | Weight | Objectives |
|---|---|---|
| Topic 1: Management and Communication | 10-13% | |
| Topic 2: Surveillance and Epidemiologic Investigation | 22-26% | |
| Topic 3: Preventing/Controlling the Transmission of Infectious Agents | 17-19% | |
| Topic 4: Employee/Occupational Health | 10-13% | |
| Topic 5: Environment of Care | 10-13% | |
| Topic 6: Cleaning, Sterilization, Disinfection, Asepsis | 10-13% | |
| Topic 7: Education and Research | 6-9% | |
| Topic 8: Identification of Infectious Disease Processes | 17-19% |
We are glad to introduce the CIC study materials from our company to you. We believe our study materials will be very useful and helpful for all people who are going to prepare for the CIC exam. There are a lot of excellent experts and professors in our company. In the past years, these experts and professors have tried their best to design the CIC Study Materials for all customers.
NEW QUESTION # 57
Which of the following stains is used to identify mycobacteria?
Answer: A
Explanation:
Mycobacteria, including species such as Mycobacterium tuberculosis and Mycobacterium leprae, are a group of bacteria known for their unique cell wall composition, which contains a high amount of lipid-rich mycolic acids. This characteristic makes them resistant to conventional staining methods and necessitates the use of specialized techniques for identification. The acid-fast stain is the standard method for identifying mycobacteria in clinical and laboratory settings. This staining technique, developed by Ziehl-Neelsen, involves the use of carbol fuchsin, which penetrates the lipid-rich cell wall of mycobacteria. After staining, the sample is treated with acid-alcohol, which decolorizes non-acid-fast organisms, while mycobacteria retain the red color due to their resistance to decolorization-hence the term "acid-fast." This property allows infection preventionists and microbiologists to distinguish mycobacteria from other bacteria under a microscope.
Option B, the Gram stain, is a common differential staining technique used to classify most bacteria into Gram-positive or Gram-negative based on the structure of their cell walls. However, mycobacteria do not stain reliably with the Gram method due to their thick, waxy cell walls, rendering it ineffective for their identification. Option C, methylene blue, is a simple stain used to observe bacterial morphology or as a counterstain in other techniques (e.g., Gram staining), but it lacks the specificity to identify mycobacteria.
Option D, India ink, is used primarily to detect encapsulated organisms such as Cryptococcus neoformans by creating a negative staining effect around the capsule, and it is not suitable for mycobacteria.
The CBIC's "Identification of Infectious Disease Processes" domain underscores the importance of accurate diagnostic methods in infection control, including the use of appropriate staining techniques to identify pathogens like mycobacteria. The acid-fast stain is specifically recommended by the CDC and WHO for the initial detection of mycobacterial infections, such as tuberculosis, in clinical specimens (CDC, Laboratory Identification of Mycobacteria, 2008). This aligns with the CBIC Practice Analysis (2022), which emphasizes the role of laboratory diagnostics in supporting infection prevention strategies.
References:
* CBIC Practice Analysis, 2022.
* CDC Laboratory Identification of Mycobacteria, 2008.
* WHO Guidelines for the Laboratory Diagnosis of Tuberculosis, 2014.
NEW QUESTION # 58
An infection preventionist is asked to recommend a product for disinfection of bronchoscopes. Which of the following agents would be appropriate?
Answer: A
Explanation:
The correct answer is D, "Peracetic acid," as this agent is appropriate for the disinfection of bronchoscopes.
According to the Certification Board of Infection Control and Epidemiology (CBIC) guidelines, bronchoscopes are semi-critical devices that require high-level disinfection (HLD) to eliminate all microorganisms except high levels of bacterial spores, as they come into contact with mucous membranes but not sterile tissues. Peracetic acid is recognized by the Centers for Disease Control and Prevention (CDC) and the Association for the Advancement of Medical Instrumentation (AAMI) as an effective high-level disinfectant for endoscopes, including bronchoscopes, due to its broad-spectrum antimicrobial activity, rapid action, and compatibility with the delicate materials (e.g., optics and channels) of these devices (CBIC Practice Analysis, 2022, Domain III: Infection Prevention and Control, Competency 3.3 - Ensure safe reprocessing of medical equipment). It is commonly used in automated endoscope reprocessors, ensuring thorough disinfection when combined with proper cleaning and rinsing protocols.
Option A (iodophor) is typically used for intermediate-level disinfection and skin antisepsis, but it is not sufficient for high-level disinfection of bronchoscopes unless specifically formulated and validated for this purpose, which is uncommon. Option B (alcohol) is effective against some pathogens but evaporates quickly, fails to penetrate organic material, and is not recommended for HLD of endoscopes due to potential damage to internal components and inadequate sporicidal activity. Option C (phenolic) is suitable for surface disinfection but lacks the efficacy required for high-level disinfection of semi-critical devices like bronchoscopes, as it does not reliably eliminate all microbial threats, including mycobacteria.
The selection of peracetic acid aligns with CBIC's emphasis on evidence-based reprocessing practices to prevent healthcare-associated infections (HAIs) associated with endoscope use (CBIC Practice Analysis,
2022, Domain III: Infection Prevention and Control, Competency 3.4 - Implement environmental cleaning and disinfection protocols). This choice ensures patient safety by adhering to manufacturer and regulatory guidelines, such as those in AAMI ST91 (AAMI ST91:2015, Flexible and semi-rigid endoscope processing in health care facilities).
References: CBIC Practice Analysis, 2022, Domain III: Infection Prevention and Control, Competencies 3.3 - Ensure safe reprocessing of medical equipment, 3.4 - Implement environmental cleaning and disinfection protocols. AAMI ST91:2015, Flexible and semi-rigid endoscope processing in health care facilities. CDC Guidelines for Disinfection and Sterilization in Healthcare Facilities, 2019.
NEW QUESTION # 59
An infection preventionist (IP) observes an increase in primary bloodstream infections in patients admitted through the Emergency Department. Poor technique is suspected when peripheral intravenous (IV) catheters are inserted. The IP should FIRST stratify infections by:
Answer: A
Explanation:
When an infection preventionist (IP) identifies an increase in primary bloodstream infections (BSIs) associated with peripheral intravenous (IV) catheter insertion, the initial step in outbreak investigation and process improvement is to stratify the data to identify potential sources or patterns of infection. According to the Certification Board of Infection Control and Epidemiology (CBIC), the "Surveillance and Epidemiologic Investigation" domain emphasizes the importance of systematically analyzing data to pinpoint contributing factors, such as location, technique, or equipment use, in healthcare-associated infections (HAIs). The question specifies poor technique as a suspected cause, and the first step should focus on contextual factors that could influence technique variability.
Option A, stratifying infections by the location of IV insertion (pre-hospital, Emergency Department, or in- patient unit), is the most logical first step. Different settings may involve varying levels of training, staffing, time pressure, or adherence to aseptic technique, all of which can impact infection rates. For example, pre- hospital settings (e.g., ambulance services) may have less controlled environments or less experienced personnel compared to in-patient units, potentially leading to technique inconsistencies. The CDC's Guidelines for the Prevention of Intravascular Catheter-Related Infections (2017) recommend evaluating the context of catheter insertion as a critical initial step in investigating BSIs, making this a priority for the IP to identify where the issue is most prevalent.
Option B, stratifying by the type of dressing used (gauze, CHG impregnated sponge, or transparent), is important but should follow initial location-based analysis. Dressings play a role in maintaining catheter site integrity and preventing infection, but their impact is secondary to the insertion technique itself. Option C, stratifying by the site of insertion (hand, forearm, or antecubital fossa), is also relevant, as anatomical sites differ in infection risk (e.g., the hand may be more prone to contamination), but this is a more specific factor to explore after broader contextual data is assessed. Option D, stratifying by the type of skin preparation used (alcohol, CHG/alcohol, or iodophor), addresses antiseptic efficacy, which is a key component of technique.
However, without first understanding where the insertions occur, it's premature to focus on skin preparation alone, as technique issues may stem from systemic factors across locations.
The CBIC Practice Analysis (2022) supports a stepwise approach to HAI investigation, starting with broad stratification (e.g., by location) to guide subsequent detailed analysis (e.g., technique-specific factors). This aligns with the CDC's hierarchical approach to infection prevention, where contextual data collection precedes granular process evaluation. Therefore, the IP should first stratify by location to establish a baseline for further investigation.
References:
* CBIC Practice Analysis, 2022.
* CDC Guidelines for the Prevention of Intravascular Catheter-Related Infections, 2017.
NEW QUESTION # 60
Surgical site infection (SSI) data for the previous quarter reveal the following numbers. The surgeon with the highest infection rate is Doctor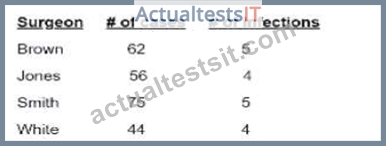
Answer: C
Explanation:
To determine which surgeon has the highest surgical site infection (SSI) rate, use the following formula: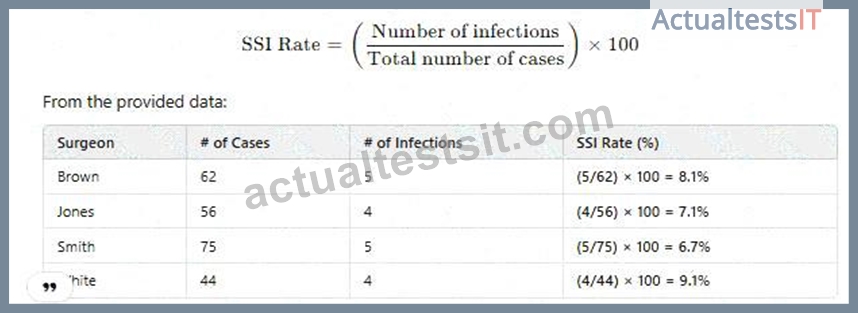
Since Dr. White has the highest SSI rate at 9.1%, the correct answer is D. White.
CBIC Infection Control Reference
SSI rates are calculated using infection count per total procedures and reported as percentage values.
NEW QUESTION # 61
A 17-year-old presents to the Emergency Department with fever, stiff neck, and vomiting. A lumbar puncture is done. The Gram stain shows Gram negative diplocooci. Presumptive identification of the organism is
Answer: D
Explanation:
The Gram stain showing Gram-negative diplococci in cerebrospinal fluid (CSF) is characteristic of Neisseria meningitidis, a leading cause of bacterial meningitis in adolescents and young adults.
Step-by-Step Justification:
* Gram Stain Interpretation:
* Gram-negative diplococci in CSF strongly suggest Neisseria meningitidis.
* Classic Symptoms of Meningitis:
* Fever, stiff neck, and vomiting are hallmark signs of meningococcal meningitis.
* Neisseria meningitidis vs. Other Bacteria:
* Haemophilus influenzae (Option A) # Gram-negative coccobacilli.
* Listeria monocytogenes (Option C) # Gram-positive rods.
* Streptococcus pneumoniae (Option D) # Gram-positive diplococci.
CBIC Infection Control References:
* APIC Ready Reference for Microbes, "Neisseria meningitidis and Meningitis".
NEW QUESTION # 62
......
Genius is 99% of sweat plus 1% of inspiration. You really don't need to think that you can succeed for nothing. If you still have a trace of enterprise, you really want to start working hard! Our CIC exam questions are the most effective helpers on your path. As the high pass rate of our CIC study braindumps is as 98% to 100%, you can pass the exam without any doubt. And with the CIC certification, you will lead a better life!
Latest CIC Test Notes: https://www.actualtestsit.com/CBIC/CIC-exam-prep-dumps.html
BTW, DOWNLOAD part of ActualTestsIT CIC dumps from Cloud Storage: https://drive.google.com/open?id=1438_kBddSnGCvZqo6benvvaZH97aS7Kf