DOWNLOAD the newest ExamDiscuss EFM PDF dumps from Cloud Storage for free: https://drive.google.com/open?id=1N-gPGFhqQFyFY9Pg9Oofcktjdjt49zPO
If you are having the same challenging problem, don't worry; NCC is here to help. Our direct and dependable NCC Treasury with Certified - Electronic Fetal Monitoring Exam Questions in three formats will surely help you pass the NCC Treasury with EFM certification exam. Because this is a defining moment in your career, do not undervalue the importance of our Treasury with Certified - Electronic Fetal Monitoring (EFM) exam dumps. Profit from the opportunity to get these top-notch exam questions for the EFM certification test.
| Section | Weight | Objectives |
|---|---|---|
| Topic 1: Pattern Recognition and Intervention | 70% | - Fetal Heart Rate Patterns
|
| Topic 2: Physiology | 11% | - Maternal-Fetal Physiology
|
| Topic 3: Electronic Monitoring Equipment | 5% | - Monitoring Systems
|
| Topic 4: Professional Issues | 5% | - Clinical Practice and Safety
|
| Topic 5: Fetal Assessment Methods | 9% | - Assessment Techniques
|
Our EFM exam question is widely known throughout the education market. Almost all the candidates who are ready for the qualifying examination know our EFM exam questions. Even when they find that their classmates or colleagues are preparing a EFM exam, they will introduce our study materials to you. So, our learning materials help users to be assured of the EFM Exam. Currently, my company has introduced three versions of EFM learning materials, covering almost all the needs of the different customers.
NEW QUESTION # 106
A woman is being induced with oxytocin. The tracing shown is representative of 20 minutes. Based on this tracing, the next step would be to: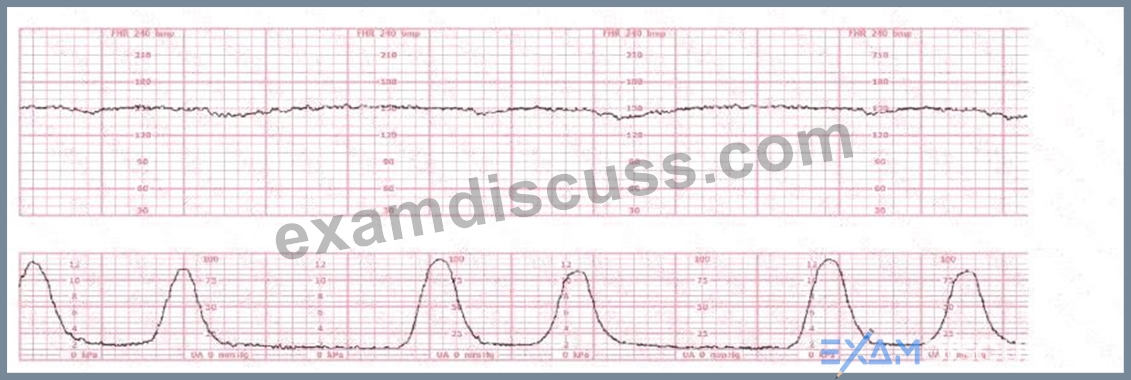
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
Evaluation of a tracing during oxytocin induction requires analysis of fetal status (baseline, variability, accelerations, decelerations) and uterine activity, with attention to tachysystole and fetal intolerance. NCC, AWHONN, Miller, Menihan, Simpson, and the NICHD guidelines all emphasize that oxytocin must be adjusted based on fetal response and contraction frequency.
Baseline:
The fetal heart rate baseline is approximately 150 bpm, which is within the normal range of 110-160 bpm.
Variability:
The tracing shows minimal variability (approximately 1-4 bpm amplitude). Minimal variability for a sustained period is categorized as a Category II pattern under NCC/NICHD classification.
Accelerations:
No accelerations are present during the 20-minute representative segment.
Decelerations:
There are no recurrent variable, no recurrent late, and no prolonged decelerations.
Uterine Activity:
The tracing shows very frequent contractions-approximately every 1½ to 2 minutes, which meets the NCC definition of tachysystole when averaged over 10 minutes (more than 5 contractions in 10 minutes).
According to NCC and AWHONN standards, when tachysystole is present with minimal variability, oxytocin must be reduced or discontinued even in the absence of late decelerations.
Clinical decision-making (per NCC principles):
NCC emphasizes that management of Category II patterns during induction starts with intrauterine resuscitative measures, including decreasing or stopping oxytocin when uterine activity is excessive or fetal response is suboptimal. Minimal variability with tachysystole requires correction of uterine stimulation before escalating to invasive monitoring or considering operative birth.
Option B (place a spiral electrode) is not indicated because the pattern is clearly visible and the priority is correcting uterine overstimulation, not refining the tracing.
Option C (operative birth) is not indicated; there is no Category III pattern or recurrent decelerations.
Option A (discontinue oxytocin) is the correct first-line action according to NCC-aligned guidelines when tachysystole and minimal variability occur.
References:
NCC C-EFM Candidate Guide (2025); NCC Content Outline; NICHD Three-Tier FHR Interpretation System; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 107
A woman at 39-weeks gestation is in early labor, 2-3 cm dilated, 85% effaced, and -2 station. Based on the fetal heart rate tracing shown, what is the most appropriate first intervention?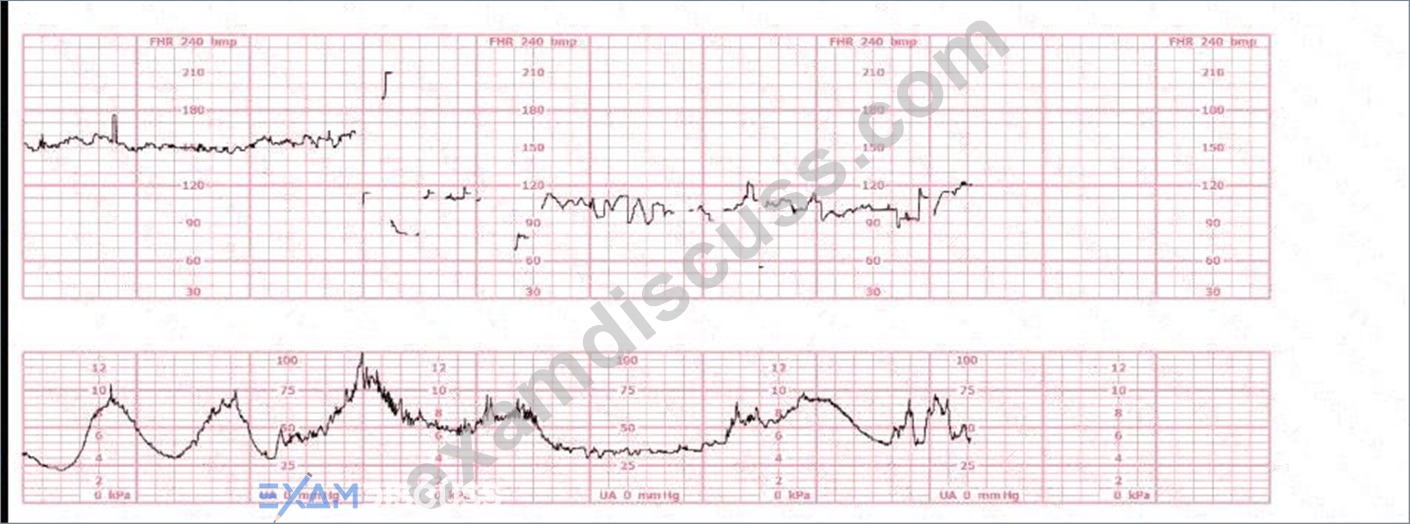
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The tracing shows significant artifact, periods of signal loss, and abrupt changes inconsistent with physiologic fetal patterns. This is typical of poor signal quality, not actual fetal decelerations. In early labor at -2 station, external FHR monitoring often loses contact due to fetal position and maternal movement.
NCC and AWHONN emphasize the following when artifact is present:
* Correct signal quality before interpreting the tracing.
* Troubleshooting steps include:- Adjusting transducer location- Ensuring adequate ultrasound gel- Repositioning the mother- Checking for maternal heart rate contamination Why the other options are incorrect:
* B. IV fluid bolus - Indicated for hypotension or late decelerations, not for artifact.
* C. Terbutaline - Used for tachysystole with fetal intolerance; there is no tachysystole shown.
Thus, the correct first step is A. Adjust the fetal monitor.
References:NCC C-EFM Candidate Guide; AWHONN Fetal Heart Monitoring Principles & Practices; Miller' s Pocket Guide; Menihan; Simpson & Creehan.
NEW QUESTION # 108
A characteristic of early decelerations is that they
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract (No URLs or Links):
Early decelerations are defined in NCC and AWHONN resources as gradual, uniform decelerations that mirror uterine contractions and are associated with fetal head compression. AWHONN's Fetal Heart Monitoring Principles states: "Early decelerations are a benign pattern caused by vagal stimulation secondary to fetal head compression." Menihan similarly notes: "The mechanism of early decelerations is a vagal reflex response; they do not reflect hypoxia." They are periodic, not episodic, because they occur with contractions-which rules out option A.
They typically remain within a normal heart rate range and do not usually fall below 100 bpm; this eliminates option C. NCC Candidate Guide emphasizes that early decelerations are considered a normal physiologic response, not a pathologic pattern, and are categorized as "Category I" when variability is present.
Thus, the correct characteristic is that they are caused by a vagal reflex, making B the correct answer.
References:AWHONN Fetal Heart Monitoring ProgramMenihan: Electronic Fetal MonitoringSimpson & Creasy: Fetal PhysiologyNCC C-EFM Content Domains - Physiology
NEW QUESTION # 109
A 20-year-old woman (G1P0) at 40-weeks gestation was admitted for cervical ripening with dinoprostone (Cervidil) four hours ago. She developed the pattern shown one hour ago. She has been changed to a lateral position and given a fluid bolus, and the pattern continues. An appropriate intervention would be to: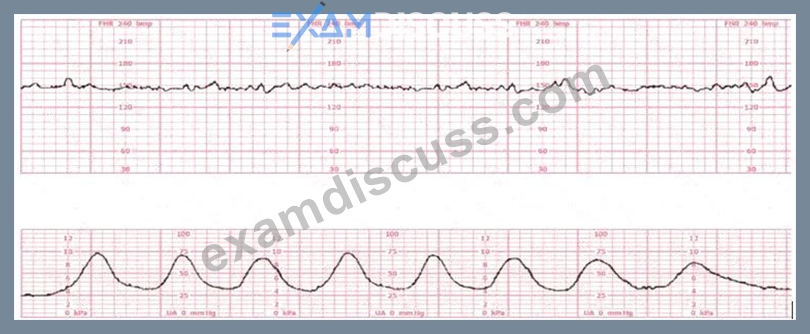
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The tracing shows tachysystole (more than 5 contractions in 10 minutes) with minimal variability and recurrent decelerations consistent with uteroplacental insufficiency caused by excessive uterine activity.
Dinoprostone (Cervidil) is a uterotonic prostaglandin, and one of its known complications is uterine tachysystole with Category II or III fetal heart rate patterns.
NCC/AWHONN guidance for tachysystole caused by prostaglandins:
* FIRST intervention: Remove the dinoprostone insert.
* Reposition the patient (already done).
* IV fluid bolus (already done).
* Consider terbutaline only if tachysystole persists after removal of the agent.
Since maternal repositioning and IV fluids have already failed, the next step is to remove the cervical ripening agent.
Why other answers are incorrect:
* A. Continue to observe - Never acceptable with tachysystole + fetal intolerance.
* B. Terbutaline - May be used after prostaglandin removal, not before.
Thus, the correct answer is C. Remove the dinoprostone insert.
References:NCC C-EFM Candidate Guide; AWHONN Fetal Heart Monitoring Principles & Practices; Menihan; Miller's Pocket Guide; NICHD Definitions; Creasy & Resnik.
NEW QUESTION # 110
A woman reports 12 fetal movements over one hour. The best recommendation is to:
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
NCC and AWHONN consider fetal movement counts normal when:
* #10 distinct movements occur within 2 hours
* Or #4 movements in 1 hour for certain protocols
* Or #10 movements in 1 hour (common triage threshold)
This patient reports 12 movements in 1 hour, which is reassuring and requires no further testing.
Thus, recommending she continue daily kick counts at home is appropriate.
Why the other options are incorrect:
* A. NST is not needed because movements are normal.
* B. Continue to monitor is unnecessary; the test is already reassuring.
Correct choice: C. Count again the next day.
References:NCC C-EFM Candidate Guide; AWHONN Fetal Assessment guidelines; Simpson & Creehan.
NEW QUESTION # 111
......
If you obtain a golden EFM certificate, you should have more opportunities for new jobs or promotions. That's why large quantity of candidates spend much time or money on EFM qualification exams even most exams are expensive and have low pass rate. So our reliable EFM Guide Torrent will be the savior for you if you are headache about your exam. Our valid EFM test torrent materials have 99% pass rate. Sometimes choice is as important as effort. Success always belongs to a person who has the preparation.
Exam EFM Questions Pdf: https://www.examdiscuss.com/NCC/exam/EFM/
What's more, part of that ExamDiscuss EFM dumps now are free: https://drive.google.com/open?id=1N-gPGFhqQFyFY9Pg9Oofcktjdjt49zPO