2026 Latest Braindumpsqa EFM PDF Dumps and EFM Exam Engine Free Share: https://drive.google.com/open?id=1Jy8Z_21NbsgH4NehzV-a6r-WPcjNiZen
Our products boost 3 versions and varied functions. The 3 versions include the PDF version, PC version, APP online version. You can use the version you like and which suits you most to learn our EFM study materials. The 3 versions support different equipment and using method and boost their own merits and functions. For example, the PC version supports the computers with Window system and can stimulate the real exam. Our products also boost multiple functions which including the self-learning, self-evaluation, statistics report, timing and stimulation functions. Each function provides their own benefits to help the clients learn the EFM Study Materials efficiently. For instance, the self-learning and self-evaluation functions can help the clients check their results of learning the Certified - Electronic Fetal Monitoring study materials.
| Section | Weight | Objectives |
|---|---|---|
| Professional Issues | 5% | - Clinical Practice and Safety
|
| Pattern Recognition and Intervention | 70% | - Maternal and Fetal Complications
|
| Fetal Assessment Methods | 9% | - Assessment Techniques
|
| Physiology | 11% | - Maternal-Fetal Physiology
|
| Electronic Monitoring Equipment | 5% | - Monitoring Systems
|
Take a look at our Free NCC EFM Exam Questions and Answers to check how perfect they are for your exam preparation. Once you buy it, you will be able to get free updates for NCC EFMl exam questions for up to 12 months. We also ensure that our support team and the core team of EFM provide services to resolve all your issues. There is a high probability that you will be successful in the NCC EFM exam on the first attempt after buying our prep material.
NEW QUESTION # 121
Uterine contraction intensity is manually measured by degree of uterine:
Answer: C
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Equipment Concepts:
When using external tocodynamometry, uterine contraction intensity cannot be measured in mmHg. It is assessed manually, using palpation. NCC and AWHONN teach:
* Contraction intensity is estimated by palpating the fundus during a contraction.
* The degree of firmness versus indentation determines intensity:
* Mild # uterus easily indented
* Moderate # firm, difficult to indent
* Strong # rigid, cannot be indented
Why the incorrect answers are wrong:
* B. Muscle strength - Not measurable by external or manual exam.
* C. Pain - Not a reliable indicator; pain perception varies widely and does not correlate with uterine intensity.
Thus, the correct manual measurement is done through uterine indentation, making A correct.
References:NCC C-EFM Candidate Guide; AWHONN Principles & Practices; Menihan EFM; Miller's Pocket Guide; Simpson & Creehan.
NEW QUESTION # 122
A 30-year-old woman (G2P0) is experiencing preterm labor at 26-weeks gestation. She is receiving magnesium sulfate for neuroprotection. Her external fetal monitoring tracing over the past 30 minutes is shown. The next step would be to: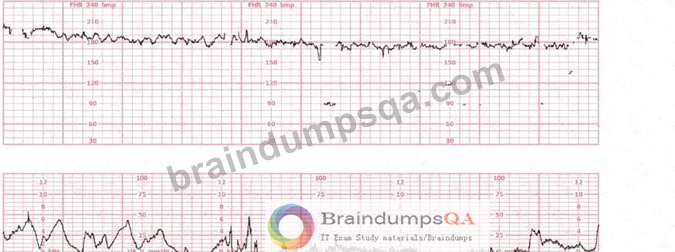
Answer: C
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
This tracing shows:
* Baseline ~170-175 bpm # fetal tachycardia
* Minimal variability
* No contractions of significance
* Maternal treatment with magnesium sulfate, which typically decreases baseline and variability-not increase it NCC and AWHONN physiology guidelines emphasize that fetal tachycardia is most commonly associated with maternal infection, including chorioamnionitis, especially in preterm labor.
Magnesium sulfate does not cause tachycardia; it generally causes:
* # baseline
* # variability
Thus, fetal tachycardia + minimal variability in a preterm patient strongly suggests maternal infection, requiring evaluation for chorioamnionitis.
Why the wrong answers are incorrect:
* A. Acetaminophen # used after confirming fever, not before evaluating the cause.
* B. Discontinuing magnesium # magnesium sulfate does not cause tachycardia; discontinuing it removes fetal neuroprotection.
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; Simpson & Creehan; Menihan EFM; Creasy & Resnik.
NEW QUESTION # 123
To differentiate a fetal dysrhythmia from artifact, it is important to recognize that artifact appears as deflections that are:
Answer: A
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
Artifact on fetal monitoring:
* Appears erratic, disorganized, and without physiologic pattern
* Shows random amplitude changes
* Often correlates with maternal movement, monitor displacement, or poor signal
* Lacks cyclical, repetitive characteristics seen in true dysrhythmias
Fetal dysrhythmias, by contrast:
* Have repetitive, patterned, predictable rhythm disturbances
* May show uniform premature beats, bigeminy, or sudden rate shifts
Therefore, varied and disorganized = artifact.
References:NCC Candidate Guide; AWHONN FHMPP; Menihan; Miller's Pocket Guide.
NEW QUESTION # 124
A reliable indicator of fetal oxygenation is fetal
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources AWHONN and NICHD definitions state that fetal accelerations are a strong indicator of adequate fetal oxygenation and neurologic integrity. Accelerations reflect intact sympathetic and parasympathetic balance and adequate oxygen reserve.
Simpson & Creehan emphasize accelerations as "the most reliable sign of fetal well-being," because they require intact autonomic function, sufficient pH, and adequate oxygenation. Menihan also identifies accelerations as the most reassuring feature on a fetal heart tracing.
Fetal movement is helpful but not directly reflective of oxygenation, as movements can decline for non- hypoxic reasons (sleep cycles, maternal sedation). Regular sleep-wake cycles are normal developmental neurologic patterns and not oxygenation markers.
Creasy & Resnik reinforce that "presence of accelerations reliably indicates absence of metabolic acidemia." References:
AWHONN - Fetal Heart Monitoring Principles & PracticesSimpson & Creehan - Perinatal NursingMenihan
- Electronic Fetal MonitoringCreasy & Resnik - Maternal-Fetal MedicineMiller's Pocket Guide
NEW QUESTION # 125
The decelerations seen in the fetal monitoring tracing shown are best described as: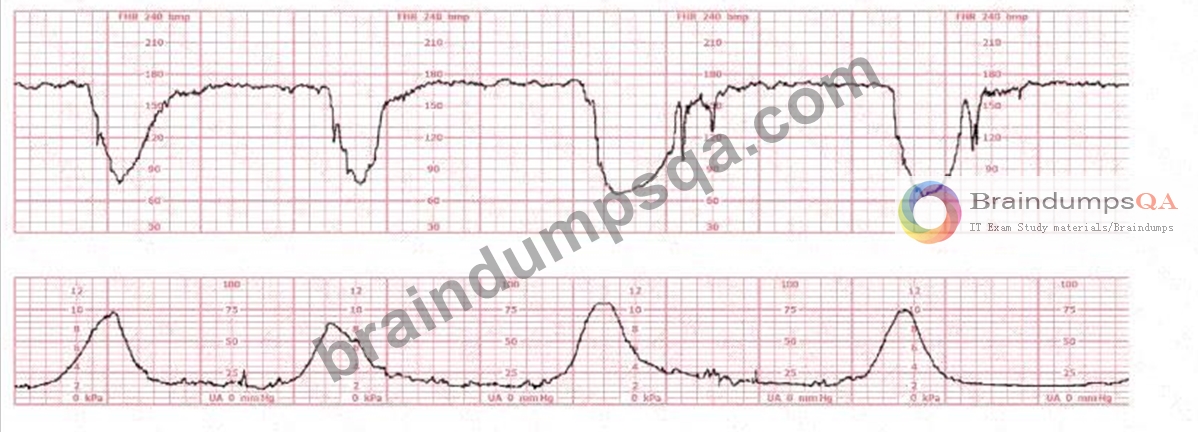
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
Accurate classification of decelerations requires evaluating their shape, onset, nadir, recovery, relationship to contractions, and variability characteristics. NCC uses the NICHD standardized definitions, reinforced across AWHONN, Miller's Pocket Guide, Menihan, Simpson, and Creasy & Resnik.
Key features in this tracing:
* Abrupt onsetThe FHR drops rapidly from baseline to nadir in less than 30 seconds-this is the defining hallmark of a variable deceleration per NICHD.
* Sharp V-shape and deep amplitudeThe tracing shows steep descents and ascents, characteristic of cord compression-type variable decelerations.
* Inconsistent timing with contractionsThe decelerations do not begin at the start of contractions (as early decelerations would) and do not consistently begin after the peak of contractions (as late decelerations would). Variable decelerations can occur before, during, or after a contraction-exactly what is demonstrated here.
* Rapid return to baselineAnother core feature of variable decelerations in NICHD/NCC definitions.
* No uniform contraction relationshipEarly decelerations are symmetrical and mirror contractions.
Late decelerations begin after the peak of the contraction. This strip does not match either pattern.
Differentiation per NCC-aligned definitions:
* Early Decelerations:Gradual onset (>30 sec), nadir mirrors contraction peak, shallow, uniform.Not present.
* Late Decelerations:Gradual descent, nadir after contraction peak, smooth shape.Not present.
* Variable Decelerations:Abrupt onset (<30 sec), variable timing, sharp V-shape, rapid recovery, often with shoulders.Exactly matches the tracing.
Therefore, according to NICHD/NCC criteria, the decelerations shown are variable decelerations.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline; NICHD Standardized Definitions; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 126
......
Originating the EFM exam questions of our company from tenets of offering the most reliable backup for customers, and outstanding results have captured exam candidates’ heart for their functions. Our practice materials can be subdivided into three versions. All those versions of usage has been well-accepted by them. There is not much disparity among these versions of EFM simulating practice, but they do helpful to beef up your capacity and speed up you review process to master more knowledge about the EFM exam, so the review process will be unencumbered.
EFM Exam Discount: https://www.braindumpsqa.com/EFM_braindumps.html
P.S. Free 2026 NCC EFM dumps are available on Google Drive shared by Braindumpsqa: https://drive.google.com/open?id=1Jy8Z_21NbsgH4NehzV-a6r-WPcjNiZen