DOWNLOAD the newest ActualTestsQuiz EFM PDF dumps from Cloud Storage for free: https://drive.google.com/open?id=18r_2qv0-PGQPZ7gu913Eptdj_PvcrHDN
If you are the first time to buy the EFM learning material online, or you have bought them for many times, there may be some problem that puzzle you, if you have any questions about the EFM exam dumps, you can ask our service stuff for help. They have the professional knowledge of EFM Training Materials, and they will be very helpful for solving your problem. In addition, we have free demo for you to try before buying the product, and you can have a try before purchasing.
| Section | Weight | Objectives |
|---|---|---|
| Fetal Assessment Methods | 9% | - Assessment Techniques
|
| Physiology | 11% | - Maternal-Fetal Physiology
|
| Electronic Monitoring Equipment | 5% | - Monitoring Systems
|
| Pattern Recognition and Intervention | 70% | - Maternal and Fetal Complications
|
| Professional Issues | 5% | - Clinical Practice and Safety
|
The EFM practice exam we offered is designed with the real questions that will help you in enhancing your knowledge about the EFM certification exam. Our online test engine will improve your ability to solve the difficulty of EFM Real Questions and get used to the atmosphere of the formal test. Our experts created the valid EFM study guide for most of candidates to help them get good result with less time and money.
NEW QUESTION # 91
The most highly oxygenated blood in the fetal circulation is found in the
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract Sources:
In fetal physiology, the highest oxygen saturation exists in the umbilical vein, which then flows through the ductus venosus before entering the right atrium.
According to Creasy & Resnik Maternal-Fetal Medicine, and AWHONN physiologic foundations:
* The umbilical vein carries oxygen-rich blood from the placenta (approx. 80% saturation).
* Most of this blood bypasses the liver via the ductus venosus, which therefore contains the most highly oxygenated blood within the fetal circulatory system.
By contrast:
* The descending aorta contains mixed blood with significantly lower oxygen content due to mixing after passage through the ductus arteriosus.
* The pulmonary arteries in the fetus carry predominantly deoxygenated blood, since fetal lungs are fluid-filled and have high pulmonary vascular resistance.
Thus, the structure containing the highest fetal oxygen concentration is the ductus venosus.
References:Creasy & Resnik - Maternal Fetal Medicine;AWHONN Fetal Monitoring;Simpson & Miller - Fetal Monitoring Physiology;NCC C-EFM Content Outline - Physiology Domain.
NEW QUESTION # 92
The tracing shown is a: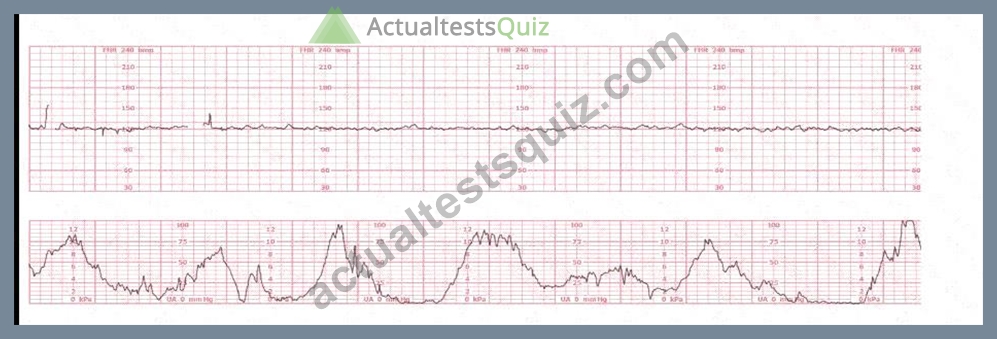
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References (No URLs):
Interpretation of fetal heart rate (FHR) tracings in the NCC C-EFM exam follows the standardized NICHD three-tier classification, which is fully adopted in NCC's content outline and recommended references such as AWHONN Fetal Heart Monitoring Principles & Practices, Miller's EFM Pocket Guide, Menihan, Simpson' s Perinatal Nursing, and Creasy & Resnik.
Baseline:
The tracing demonstrates an FHR baseline around 145-150 bpm, which falls within the normal range of 110-
160 bpm. NCC references define baseline as the mean FHR rounded to increments of 5 bpm over a 10-minute window.
Variability:
The strip shows minimal variability, with amplitude fluctuations approximately 0-2 bpm.
According to NCC-aligned definitions:
* Moderate variability: 6-25 bpm
* Minimal variability: 1-5 bpm
* Absent variability: undetectable amplitude
This tracing shows minimal variability, not moderate, so it cannot be Category I.
Accelerations:
No accelerations are present. Lack of accelerations alone does not classify the tracing as Category III.
Decelerations:
There are no recurrent late decelerations, no recurrent variable decelerations, and no prolonged decelerations. Without these, and with minimal variability, the tracing does not meet Category III criteria.
Category III criteria (per NICHD/NCC):
Must include at least one of the following:
* Absent variability with recurrent late decelerations
* Absent variability with recurrent variable decelerations
* Absent variability with bradycardia
* Sinusoidal pattern
None of these are present.
Category II criteria (per NICHD/NCC):
Category II includes tracings that are not Category I or III.
Examples specifically listed include:
* Minimal variability
* Absent accelerations after fetal stimulation
* Tachycardia
* Bradycardia without absent variability
* Variable or late decelerations occurring intermittently
Because this tracing shows minimal variability, a normal baseline, no accelerations, and no recurrent decelerations, it fits squarely into Category II.
Therefore, the correct classification is Category II.
References:NCC C-EFM Candidate Guide and Content Outline (2025); AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine; NICHD Three-Tier FHR Interpretation System.
NEW QUESTION # 93
A nulliparous woman at term presents with leaking fluid. Rupture of membranes confirmed. After 6 hours she is completely dilated, +2 station, has been pushing 2 hours with oxytocin at 10 mU/min. The fetal tracing is shown. What is the next step in management?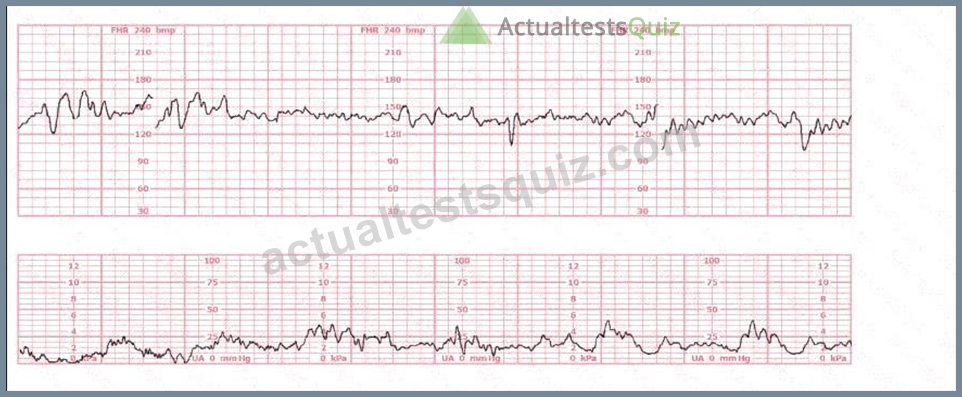
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract Without Any URLs or Links:
According to the NCC C-EFM 2025 Exam Content Outline and recommended references such as AWHONN Fetal Heart Monitoring Principles, Simpson & Miller (Fetal Monitoring Text), and Menihan's EFM Guide, recurrent variable or late decelerations with minimal or moderate variability during the second stage of labor-particularly when the patient has been pushing for #2 hours-indicate progressive fetal intolerance of labor.
AWHONN states that when the fetal tracing displays recurrent variable decelerations with ongoing stress from long second stage, the recommended intervention is operative or expedited vaginal birth, provided the fetal station is at +2 or lower. AWHONN and Simpson emphasize that reducing oxytocin is insufficient when the tracing demonstrates ongoing significant decelerations during active pushing with adequate descent.
The NCC blueprint within Pattern Recognition & Intervention emphasizes:
* Identifying worsening recurrent decelerations
* Acting when fetal tolerance is decreasing
* Prioritizing timely intervention when the second stage exceeds standard limits with a non-reassuring tracing Because she is fully dilated, vertex at +2, and tracing shows recurrent decelerations during pushing, the evidence-based next step is expediting birth, typically via operative vaginal delivery.
References:AWHONN Fetal Heart Monitoring Principles & PracticesSimpson & Miller: Fetal MonitoringMenihan: Electronic Fetal MonitoringNCC C-EFM Exam Content Outline 2025
NEW QUESTION # 94
(Full question statement)
A dysrhythmia is noted. The pregnancy and labor course has been normal with no complications. The next step in management is to
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract (NCC C-EFM sources: AWHONN, Miller's Pocket Guide, Menihan, Simpson, Creasy & Resnik, 2025 Candidate Guide) AWHONN and Menihan emphasize that most fetal dysrhythmias detected intrapartum are premature atrial contractions (PACs)-the most common benign rhythm variation. They typically appear as intermittent, irregular deflections on the fetal heart rate tracing without affecting variability or baseline.
Miller's Pocket Guide to Fetal Monitoring states that PACs are usually transient, self-limiting, and require only observation unless accompanied by tachyarrhythmia or hemodynamic compromise. When variability is preserved and no repetitive pattern or sustained tachycardia occurs, no intrauterine resuscitation measures are indicated.
Simpson and Creehan describe that oxygen administration and fluid boluses are not recommended for benign dysrhythmias, as they do not improve fetal conduction patterns and may contribute to unnecessary interventions.
The NCC 2025 Candidate Guide specifies that correct management requires distinguishing benign arrhythmias from pathologic tachyarrhythmias, which would require escalation. In the absence of fetal compromise or maternal pathology, the appropriate action is continued observation.
Therefore, the correct management is to continue to observe.
NEW QUESTION # 95
A reliable indicator of fetal oxygenation is fetal
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources AWHONN and NICHD definitions state that fetal accelerations are a strong indicator of adequate fetal oxygenation and neurologic integrity. Accelerations reflect intact sympathetic and parasympathetic balance and adequate oxygen reserve.
Simpson & Creehan emphasize accelerations as "the most reliable sign of fetal well-being," because they require intact autonomic function, sufficient pH, and adequate oxygenation. Menihan also identifies accelerations as the most reassuring feature on a fetal heart tracing.
Fetal movement is helpful but not directly reflective of oxygenation, as movements can decline for non- hypoxic reasons (sleep cycles, maternal sedation). Regular sleep-wake cycles are normal developmental neurologic patterns and not oxygenation markers.
Creasy & Resnik reinforce that "presence of accelerations reliably indicates absence of metabolic acidemia." References:
AWHONN - Fetal Heart Monitoring Principles & PracticesSimpson & Creehan - Perinatal NursingMenihan
- Electronic Fetal MonitoringCreasy & Resnik - Maternal-Fetal MedicineMiller's Pocket Guide
NEW QUESTION # 96
......
In addition to the PDF questions ActualTestsQuiz offers desktop Certified - Electronic Fetal Monitoring (EFM) practice exam software and web-based Certified - Electronic Fetal Monitoring (EFM) practice exam, to help you cope with Certified - Electronic Fetal Monitoring (EFM) exam anxiety. These NCC EFM Practice Exams simulate the actual NCC EFM exam conditions and provide you with an accurate assessment of your readiness for the EFM exam.
EFM Valid Exam Fee: https://www.actualtestsquiz.com/EFM-test-torrent.html
P.S. Free 2026 NCC EFM dumps are available on Google Drive shared by ActualTestsQuiz: https://drive.google.com/open?id=18r_2qv0-PGQPZ7gu913Eptdj_PvcrHDN