Are you worried about insufficient time to prepare the exam? Do you have a scientific learning plan? Maybe you have set a series of to-do list, but it’s hard to put into practice for there are always unexpected changes during the CCDS exam. Here we recommend our CCDS test prep to you. With innovative science and technology, our study materials have grown into a powerful and favorable product that brings great benefits to all customers. We are committed to designing a kind of scientific study material to balance your business and study schedule. With our CCDS Exam Guide, all your learning process includes 20-30 hours. As long as you spare one or two hours a day to study with our latest CCDS quiz prep, we assure that you will have a good command of the relevant knowledge before taking the exam. What you need to do is to follow the CCDS exam guide system at the pace you prefer as well as keep learning step by step.
| Section | Weight | Objectives |
|---|---|---|
| Topic 1: Medical record documentation | 19.17% | - Documentation requirements and diagnosis or procedure code assignment - Documentation clarification and compliant physician queries |
| Topic 2: Impact of reportable diagnoses on quality of care | 8.33% | - Quality metrics, reporting programs, and financial impact - Mortality, severity of illness, and risk of mortality |
| Topic 3: Communication skills | 9.17% | - Physician education and effective communication - CDI and coding roles and interdisciplinary collaboration |
| Topic 4: Professionalism, ethics, and compliance | 9.17% | - Query compliance, DRG creep, and audit risks - Confidentiality, DRG compliance, and ethical CDI practices |
| Topic 5: Healthcare regulations, reimbursement, and documentation requirements related to the IPPS | 12.5% | - CC/MCC, CMI, Medicare contractors, and compliance - IPPS, MS-DRGs, reimbursement, and medical necessity |
| Topic 6: Official Guidelines for Coding and Reporting | 14.17% | - Coding guidelines, AHA Coding Clinic, HACs, and POA indicators - Principal and secondary diagnosis assignment |
| Topic 7: Anatomy and physiology, pathophysiology, pharmacology, and medical terminology | 19.17% | - Anatomy, physiology, pathophysiology, pharmacology, and terminology - Clinical conditions and clinical indicators |
| Topic 8: Healthcare facility CDI program analysis | 8.33% | - Data analysis, forecasting, and performance measurement - CDI productivity, provider response, CMI, and program metrics |
Once you get the ACDIS CCDS certificate, you can quickly quit your current job and then change a desirable job. The ACDIS CCDS certificate can prove that you are a competent person. So it is easy for you to pass the interview and get the job. The assistance of our CCDS practice quiz will change your life a lot.
NEW QUESTION # 71
The table below shows physician performance: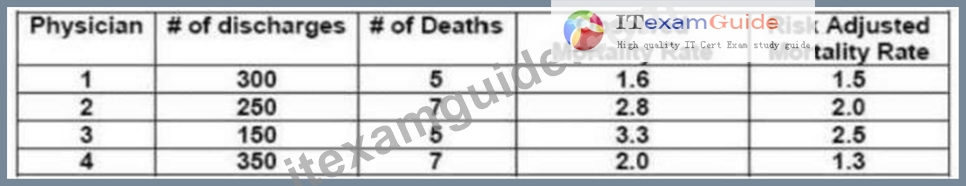
Which of the following physicians will have the most favorable mortality rate on a public website, such as Healthgrades.com?
Answer: A
Explanation:
Physician 4 has the most favorable risk-adjusted mortality rate, at 1.3, compared with Physician 1 at 1.5, Physician 2 at 2.0, and Physician 3 at 2.5. Although Physician 1 has fewer observed deaths and an observed mortality rate of 1.6%, public outcome comparisons commonly incorporate risk adjustment rather than relying solely on raw mortality. Risk adjustment attempts to account for differences in patient complexity, comorbid disease burden, demographic factors, and other characteristics that influence expected outcomes.
This is directly relevant to CDI because incomplete documentation of clinically significant comorbidities can understate patient severity and therefore adversely affect the expected mortality component of risk-adjusted performance calculations. Conversely, accurate documentation allows coded data to represent the actual severity and risk of the population being treated. Healthgrades specifically states that its mortality methodology adjusts for patient risk factors to permit more meaningful comparisons of clinical outcomes.
The CCDS content outline specifically requires knowledge of mortality indices, severity of illness/risk of mortality, physician performance, and the effect of documentation on publicly reported data.
CCDS Reference Topics: Impact of reportable diagnoses on quality of care; Healthcare facility CDI program analysis; mortality index and risk adjustment.
=========
NEW QUESTION # 72
A patient experienced a type 1 STEMI 10 days ago. The patient is readmitted and develops a new type 1 NSTEMI during the four-week acute myocardial infarction period. Which ICD-10-CM concept applies?
Answer: D
Explanation:
ICD-10-CM provides category I22 for a subsequent acute myocardial infarction occurring within four weeks-28 days-of an initial acute MI, when the qualifying MI types and circumstances meet the classification requirements.
The FY 2026 Official Guidelines specify that when a patient with a type 1 or unspecified acute MI experiences a new type 1 or unspecified MI within four weeks of the initial MI, a code from category I22 is used together with the appropriate I21 code. Sequencing depends on the circumstances of the encounter.
This rule requires care because type 2 MI and certain other myocardial infarction classifications do not follow the same I22 subsequent-MI logic. CDI specialists therefore need accurate documentation of MI type, anatomic location when applicable, timing, and whether the current event represents a genuinely new infarction rather than ongoing care for the original MI.
The prior STEMI does not become an "old MI" merely because the patient left the hospital; the ICD-10-CM acute MI period extends for four weeks from onset.
CCDS Reference Topics: Acute MI; subsequent MI; I21/I22; four-week rule; cardiovascular coding.
=========
NEW QUESTION # 73
A patient's baseline creatinine is 1.0 mg/dL. Following prolonged hypotension, creatinine rises to 3.8 mg/dL.
Urinalysis demonstrates granular casts, and the nephrologist documents "acute renal failure" but does not specify the underlying renal lesion. Which condition would be MOST appropriate to consider in a clinically supported clarification query?
Answer: D
Explanation:
The clinical pattern supports consideration of acute tubular necrosis (ATN) as a clarification opportunity.
Prolonged hypotension can cause renal ischemia severe enough to injure tubular epithelial cells. A substantial acute creatinine increase and granular or "muddy brown" casts are classic clinical findings associated with ATN.
The provider has already documented acute renal failure, so the purpose of the query would be to clarify the underlying type of acute kidney injury when clinically appropriate-not to create AKI from laboratory data alone.
Stage 5 chronic kidney disease requires evidence of chronic, persistent severe renal dysfunction and cannot be inferred from an acute creatinine rise following hypotension. Nephrotic syndrome is characterized principally by substantial proteinuria, hypoalbuminemia, edema, and other findings not described here. Pyelonephritis would ordinarily require evidence of upper urinary infection.
A CDI specialist should review the complete clinical record, including baseline renal function, hemodynamic course, nephrology notes, urinalysis, fluid management, nephrotoxic exposures, and renal replacement therapy when applicable.
The CCDS competency framework includes renal failure, laboratory interpretation, and recognition of clinically supported opportunities for diagnostic specificity.
CCDS Reference Topics: Acute kidney injury; acute tubular necrosis; renal pathophysiology; clinical indicators; diagnostic specificity.
=========
NEW QUESTION # 74
A patient is admitted for UTI with AMS. The physician documents "UTI due to Escherichia coli." CT scan of the head is negative, with AMS improving and family reporting the patient is now at baseline. Admission creatinine is 1.2 mg/dL and sodium is 146 mEq/L. Plan is discharge home today.
The CDI specialist should query for the:
Answer: C
Explanation:
The clinically meaningful documentation gap concerns what condition actually occasioned the inpatient admission and whether the altered mental status represents a defined diagnosis associated with the episode.
The record identifies a UTI due to E. coli, but the patient also presented with AMS significant enough to undergo head CT evaluation. The AMS subsequently resolved to baseline.
A creatinine of 1.2 mg/dL alone does not establish acute kidney injury because AKI requires evidence of an acute change from baseline and appropriate clinical context. Similarly, sodium of 146 mEq/L is only minimally elevated and, without clinical evaluation or treatment demonstrating significance, does not justify a query designed to generate hypernatremia.
Merely clarifying AMS as acute versus chronic is also less useful than determining the actual diagnosis explaining the altered mental state and its relationship to the admission. Depending on provider judgment and supporting evidence, possibilities could include an acute encephalopathic process, delirium, symptoms associated with infection, or another condition.
The query should remain neutral and should not presume that the UTI caused the AMS.
CCDS Reference Topics: Principal diagnosis clarification; AMS; clinical indicators; query prioritization; documentation integrity.
=========
NEW QUESTION # 75
What type of query is needed to compliantly address a scenario in which clinical indicators of a diagnosis exist, but for which no diagnosis has been documented in the medical record?
Answer: D
Explanation:
A multiple-choice query is appropriate when clinical indicators support the possibility of a condition but the diagnosis itself has not yet been documented. The query may present clinically reasonable diagnostic choices supported by the patient's record while also allowing an alternative response such as "other, please specify" or an inability to determine.
A yes/no query is not the appropriate format for introducing a new, previously undocumented diagnosis.
AHIMA/ACDIS guidance has specifically distinguished this situation from circumstances where yes/no clarification may be used for an already documented condition, POA determination, cause-and-effect clarification, or similar defined purposes.
A clinical-validation query addresses the opposite problem: a diagnosis is already documented, but the health record appears to lack sufficient clinical support for that diagnosis. Therefore, option C does not match the scenario.
A cause-and-effect query would be appropriate when two documented conditions require clarification of their relationship, not when the fundamental issue is the absence of a diagnosis.
Current AHIMA/ACDIS guidance continues to permit multiple-choice queries supported by relevant clinical indicators and emphasizes neutral wording.
CCDS Reference Topics: Compliant query formats; missing diagnosis; clinical validation; nonleading queries.
=========
NEW QUESTION # 76
......
Itexamguide is driven by the ambition of making you succeed. Our ACDIS CCDS study material offers you high-quality training material and helps you have a good knowledge of the CCDS actual test. The team members of Itexamguide work with a passion to guarantee your success and make you prosperous. We provide the CCDS Test Engine with self-assessment features for enhanced progress.
Exam CCDS Flashcards: https://www.itexamguide.com/CCDS_braindumps.html