P.S. JpexamがGoogle Driveで共有している無料かつ新しいCICダンプ:https://drive.google.com/open?id=1Jbe4xzi020zrOdiz-qTem70-Vl6O_iyr
IT業界の中でたくさんの野心的な専門家がいって、IT業界の中でより一層頂上まで一歩更に近く立ちたくてCBICのCIC試験に参加して認可を得たくて、CBIC のCIC試験が難度の高いので合格率も比較的低いです。CBICのCIC試験を申し込むのは賢明な選択で今のは競争の激しいIT業界では、絶えず自分を高めるべきです。しかし多くの選択肢があるので君はきっと悩んでいましょう。
| Section | Weight | Objectives |
|---|---|---|
| Surveillance and Epidemiologic Investigation | 24% | - Surveillance system design and implementation - Outbreak investigation and response - Benchmarking and reporting - Data collection, validation, and analysis |
| Employee and Occupational Health | 10% | - Workplace safety policies - Health screening and surveillance - Exposure management and post-exposure prophylaxis - Immunization programs |
| Environment of Care | 10% | - Waste management and environmental services - Facility design, construction, and renovation - Safety and risk assessment - Water and air quality management |
| Identification of Infectious Disease Processes | 19% | - Epidemiologic principles - Risk factors and transmission mechanisms - Microbiology and pathogenesis - Emerging and re-emerging pathogens |
| Education, Research, and Quality Improvement | 9% | - Regulatory and accreditation compliance - Development and delivery of education programs - Performance measurement and quality improvement - Evidence-based practice and research application |
| Prevention and Control of Transmission of Infectious Agents | 28% | - Hand hygiene and aseptic techniques - Isolation and patient placement - Cleaning, disinfection, and sterilization - Standard and transmission-based precautions - Antimicrobial stewardship |
Jpexam一連の調査と研究の結果、教科書の詳細な研究に合格することを希望する学生は、しばしば怠け者であり、学習が怠けていることがわかりました(CICテスト教材)。 一部の学生は、教科書で理解するのが難しい内容を読むときに頭痛を感じることさえあります。 私たちの研究資料は、実際のテスト環境をシミュレートする模擬試験製品の研究に焦点を当てたシニア業界の専門家によって構成された優れた試験レビュー製品です(CIC準備急流)。 専門家は、異なる専攻間の学習方法と試験モデルの違いを十分に検討し、最終的に完全なレビューシステムを形成しました。 CBIC Certified Infection Control Exam一連の演習、エラーの修正、および自己改善の後、CBIC CIC試験に合格するのに役立ちます。
質問 # 183
Operating room records indicate that 130 joint replacements have been performed. These include 70 total hip replacements, 55 total knee replacements, and 5 shoulder replacements. Two postoperative surgical site infections (SSIs) were identified in total hip replacements. What is the infection rate/100 procedures for total hip replacements?
正解:C
解説:
To determine the infection rate per 100 procedures for total hip replacements, use the following formula:
A white paper with black text and numbers AI-generated content may be incorrect.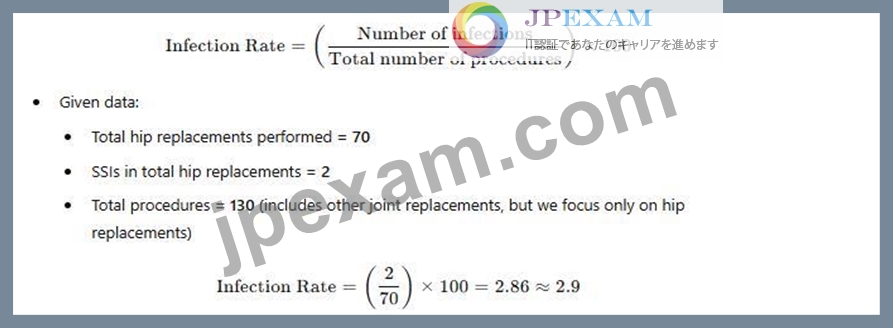
Thus, the correct answer is B. 2.9 per 100 procedures.
CBIC Infection Control Reference
The methodology of calculating SSI rates aligns with guidelines from the National Healthcare Safety Network (NHSN) and standardized infection ratio (SIR) models used for hospital-specific SSI rates.
質問 # 184
The intensive care unit has noted an increase in patients with ventilator-associated events (VAEs). Which of the following may be contributing to the increase in these events?
正解:C
解説:
Ventilator-associated events (VAEs) are complications that occur in patients receiving mechanical ventilation and include conditions such as ventilator-associated pneumonia (VAP), pulmonary edema, and atelectasis.
The CBIC Certified Infection Control Exam Study Guide (6th edition) emphasizes that patient positioning plays a critical role in preventing aspiration and subsequent respiratory complications in mechanically ventilated patients.
Maintaining patients in a supine position, particularly during transport, increases the risk of aspiration of gastric contents and oropharyngeal secretions. Aspiration is a well-recognized contributing factor to the development of VAEs because it can lead to infection, inflammation, and worsening oxygenation. The Study Guide recommends maintaining the head of the bed elevated (generally 30-45 degrees) whenever feasible, including during care activities and transport, to reduce aspiration risk.
The other options listed-daily sedation vacation, daily weaning assessment, and daily oral care with chlorhexidine-are evidence-based prevention strategies that are part of ventilator care bundles. These interventions are designed to reduce the duration of mechanical ventilation, improve pulmonary function, and decrease microbial colonization, all of which lower the risk of VAEs rather than contribute to them.
Therefore, supine positioning during transport is the most likely factor contributing to an increase in ventilator-associated events and represents a deviation from recommended infection prevention practices.
質問 # 185
An infection preventionist (IP) encounters a surgeon at the nurse's station who loudly disagrees with the IP's surgical site infection findings. The IP's BEST response is to:
正解:C
解説:
The scenario involves a conflict between an infection preventionist (IP) and a surgeon regarding surgical site infection (SSI) findings, occurring in a public setting (the nurse's station). The IP's response must align with professional communication standards, infection control priorities, and the principles of collaboration and conflict resolution as emphasized by the Certification Board of Infection Control and Epidemiology (CBIC).
The "best" response should de-escalate the situation, maintain professionalism, and facilitate a constructive dialogue. Let's evaluate each option:
* A. Report the surgeon to the chief of staff: Reporting the surgeon to the chief of staff might be considered if the behavior escalates or violates policy (e.g., harassment or disruption), but it is an escalation that should be a last resort. This action does not address the immediate disagreement about the SSI findings or attempt to resolve the issue collaboratively. It could also strain professional relationships and is not the best initial response, as it bypasses direct communication.
* B. Calmly explain that the findings are credible: Explaining the credibility of the findings is important and demonstrates the IP's confidence in their work, which is based on evidence-based infection control practices. However, doing so in a public setting like the nurse's station, especially with a loud disagreement, may not be effective. The surgeon may feel challenged or defensive, potentially worsening the situation. While this response has merit, it lacks consideration of the setting and the need for privacy to discuss sensitive data.
* C. Ask the surgeon to speak in a more private setting to review their concerns: This response is the most appropriate as it addresses the immediate need to de-escalate the public confrontation and move the discussion to a private setting. It shows respect for the surgeon's concerns, maintains professionalism, and allows the IP to review the SSI findings (e.g., data collection methods, definitions, or surveillance techniques) in a controlled environment. This aligns with CBIC's emphasis on effective communication and collaboration with healthcare teams, as well as the need to protect patient confidentiality and maintain a professional atmosphere. It also provides an opportunity to educate the surgeon on the evidence behind the findings, which is a key IP role.
* D. Ask the surgeon to change their tone and leave the nurses' station if they refuse: Requesting a change in tone is reasonable given the loud disagreement, but demanding the surgeon leave if they refuse is confrontational and risks escalating the conflict. This approach could damage the working relationship and does not address the underlying disagreement about the SSI findings. While maintaining a respectful environment is important, this response prioritizes control over collaboration and is less constructive than seeking a private discussion.
The best response is C, as it promotes a professional, collaborative approach by moving the conversation to a private setting. This allows the IP to address the surgeon's concerns, explain the SSI surveillance methodology (e.g., NHSN definitions or CBIC guidelines), and maintain a positive working relationship, which is critical for effective infection prevention programs. This strategy reflects CBIC's focus on leadership, communication, and teamwork in healthcare settings.
CBIC Infection Prevention and Control (IPC) Core Competency Model (updated 2023), Domain V:
Management and Communication, which stresses effective interpersonal communication and conflict resolution.
CBIC Examination Content Outline, Domain V: Leadership and Program Management, which includes collaborating with healthcare personnel and addressing disagreements professionally.
CDC Guidelines for SSI Surveillance (2023), which emphasize the importance of clear communication of findings to healthcare teams.
質問 # 186
An infection preventionist (IP) is asked to participate on a team to decrease ventilator-associated pneumonia (VAP) rates in a 20-bed ICU. The IP provides the following information. What is the first quarter ventilator utilization ratio?
Data Provided (First Quarter):
* Ventilator days (Jan-Mar total): 800
* Patient days (Jan-Mar total): 1200
正解:D
解説:
The Certification Study Guide (6th edition) defines the ventilator utilization ratio (VUR) as a device utilization measure used in surveillance to describe the proportion of patient time during which a specific medical device-in this case, mechanical ventilation-is in use. It is calculated by dividing the total number of ventilator days by the total number of patient days for the same location and time period.
Using the first-quarter data provided, the calculation is as follows:
Ventilator Utilization Ratio = Ventilator Days ÷ Patient Days
Ventilator Utilization Ratio = 800 ÷ 1200 = 0.67
This means that ventilators were in use for 67% of all patient days in the ICU during the first quarter. The study guide emphasizes that device utilization ratios are essential for interpreting device-associated infection data, such as VAP rates, because they reflect the level of patient exposure to the device. Higher utilization increases the population at risk and can influence infection rates independently of prevention practices.
The other answer options are incorrect because they do not reflect the correct calculation. A ratio greater than
1.0 (options C and D) would imply more device days than patient days, which is not possible in this context.
Option A underestimates utilization and does not match the provided data.
Understanding and correctly calculating utilization ratios is a core CIC exam competency, as these metrics support accurate surveillance, benchmarking, and performance improvement efforts.
Reference: Certification Study Guide (CBIC/CIC Exam Study Guide), 6th edition, Chapter 4: Surveillance and Epidemiologic Investigation.
質問 # 187
Healthcare-associated transmission of methicillin-resistant Staphylococcus aureus (MRSA) is commonly associated with which of the following?
正解:D
解説:
The CBIC Certified Infection Control Exam Study Guide (6th edition) identifies inadequate hand hygiene as the most common and significant factor associated with healthcare-associated transmission of methicillin- resistant Staphylococcus aureus (MRSA). MRSA is primarily transmitted via direct contact, most often through the hands of healthcare personnel after contact with colonized or infected patients or contaminated environmental surfaces.
While MRSA-infected or colonized patients serve as reservoirs for the organism, transmission does not occur unless there is a breakdown in infection prevention practices, particularly hand hygiene. Numerous studies and surveillance findings cited in the Study Guide demonstrate that adherence to hand hygiene protocols- before and after patient contact, after contact with bodily fluids, and after contact with the patient environment-is the single most effective measure to reduce MRSA spread within healthcare facilities.
Improper ventilation (Option A) is associated with airborne pathogens, not MRSA, which is not transmitted via the airborne route. MRSA-colonized healthcare workers (Option D) are far less commonly implicated in transmission than transient hand contamination, and routine screening of staff is not recommended except during specific outbreak investigations. Option B describes a reservoir, not the primary mechanism of transmission.
For CIC exam purposes, this question reinforces a foundational principle of infection prevention: failure to perform appropriate hand hygiene is the leading cause of healthcare-associated MRSA transmission, making it the correct and best answer.
質問 # 188
......
当社Jpexamは、製品の品質が非常に重要であることを深く知っているため、CICテストトレントの高品質の開発に注力しています。当社の製品を購入したすべてのお客様は、CICガイド急流に深い印象を残しています。もちろん、顧客は製品の高品質だけでなく、製品の効率性にも深い印象を残しています。 CIC試験の質問は多くの時間を節約するのに役立ちます。CIC試験準備を使用する場合、学習に20〜30時間を費やすだけで、CIC試験に合格できます。
CIC試験問題集: https://www.jpexam.com/CIC_exam.html
P.S.JpexamがGoogle Driveで共有している無料の2026 CBIC CICダンプ:https://drive.google.com/open?id=1Jbe4xzi020zrOdiz-qTem70-Vl6O_iyr