DOWNLOAD the newest PDFDumps CPHQ PDF dumps from Cloud Storage for free: https://drive.google.com/open?id=1HsZ5dHENW9zajq65hMEfyyh3-S3_BsE2
At the same time, our service guidelines have always been customer first. As long as you choose CPHQ real exam, we will be responsible for you in the end. Every CPHQ exam practice’s staff member is your family they will accompany you to achieve your dream! Our company's service aim is to make every customer satisfied! CPHQ Training Materials are looking forward to being able to accompany you on such an important journey.
| Section | Objectives |
|---|---|
| Performance and Process Improvement | - Quality improvement methodologies - Process mapping and workflow optimization |
| Health Data Analytics | - Statistical analysis and interpretation - Data collection and measurement systems |
| Patient Safety | - Risk management and safety systems - Adverse event analysis and prevention |
| Organizational Leadership | - Healthcare quality leadership and governance - Regulatory and accreditation compliance |
You will be cast in light of career acceptance and put individual ability to display. When you apply for a job you could have more opportunities than others. What is more, there is no interminable cover charge for our CPHQ practice engine priced with reasonable prices for your information. Considering about all benefits mentioned above, you must have huge interest to our CPHQ Study Materials. You should take the look at our CPHQ simulating questions right now.
NEW QUESTION # 16
An emergency department's quality improvement report for the first quarter showed the following data: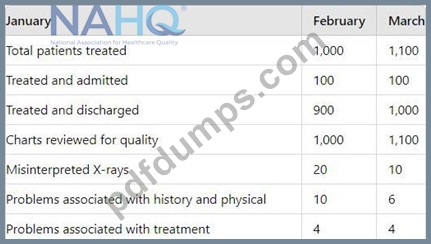
Which of the following additional information should be included in this report for each month?
Answer: A
Explanation:
In reviewing the emergency department's quality improvement report that lists data such as the total number of patients treated, those admitted or discharged, chart reviews for quality, misinterpreted X- rays, and problems associated with history, physical, and treatment, additional information that could significantly enhance the understanding and context of the provided data would be valuable.
Number of X-rays performed: Given the data already includes misinterpreted X-rays, knowing the total number of X-rays performed would provide context to the rate of misinterpretations, offering a clearer picture of the performance concerning this diagnostic tool.
Considering the existing data points in the report, the most pertinent additional information would be: D.
Number of X-rays performed. This metric would allow for calculating the percentage of misinterpreted X- rays relative to the total performed, thus giving a clearer insight into the quality and accuracy of radiological diagnostics in the emergency department.
NEW QUESTION # 17
Which of the following regulatory agencies oversee development of electronic clinical quality measures (eCQMs)?
Answer: D
NEW QUESTION # 18
A hospital has just implemented a physician order entry system. Three days into implementation, the users begin having major technical issues with the system. The nurse manager instructs staff to submit troubleshooting requests to the help desk. This is an example of which high-reliability principle?
Answer: A
Explanation:
Directing staff to the help desk for technical issues exemplifies deference to expertise (D), relying on specialized knowledge. Resilience (A), operations sensitivity (B), and failure preoccupation (C) are less relevant. NAHQ highlights expertise deference in HROs.
NAHQ CPHQ Study Guide, Patient Safety Section, "High-Reliability Organization Principles"; NAHQ CPHQ Practice Exam, Safety Culture and Expertise.
NEW QUESTION # 19
Which of the following would best facilitate the development of priorities?
Answer: B
Explanation:
The development of priorities in any organization, including healthcare, is best facilitated by comparing target versus actual performance12. This approach allows organizations to identify areas where performance is not meeting expectations and prioritize efforts to address these gaps12. This process involves setting clear goals, establishing benchmarks for performance, and regularly reviewing progress3. When actual performance falls short of the target, this indicates a priority area for improvement12.
The other options, while important in the overall management and improvement of performance, do not directly facilitate the development of priorities12. Creating a plan to evaluate performance (Option B) is a part of the performance management process, but it does not in itself help to establish priorities12.
Surveying staff for potential priorities (Option C) can provide valuable insights, but it is the comparison of actual performance against targets that will objectively identify priority areas12. Selecting valid and reliable metrics for the balanced scorecard (Option D) is crucial for measuring performance, but again, it is the comparison of these metrics against targets that will highlight the areas that need to be prioritized12.
NEW QUESTION # 20
Based on the data below, which unit should the quality Improvement coordinator focus on?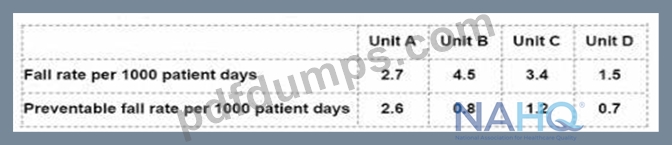
Answer: B
Explanation:
* Based on the data below, which shows the percentage of patients who acquired a hospital-associated infection (HAI) in each unit, the quality improvement coordinator should focus on Unit C, which has the highest rate of HAI among the four units.
* A hospital-associated infection (HAI) is an infection that patients get during or after receiving health care in a hospital or other health care facility. HAIs can cause serious complications, increase morbidity and mortality, prolong hospital stays, and increase health care costs. Therefore, preventing and reducing HAIs is a key quality and safety goal for health care organizations.
* A quality improvement coordinator is a professional who develops and implements quality improvement initiatives, monitors and evaluates quality performance, and provides education and support to staff and leaders on quality methods and tools. One of their responsibilities is to identify and prioritize areas for improvement based on data analysis and evidence-based practices.
* To determine which unit should be the focus of quality improvement efforts, the quality improvement coordinator can use a data analysis tool such as a Pareto chart, which shows the frequency or impact of different factors or causes in descending order, along with a cumulative line that indicates the percentage of the total. A Pareto chart can help identify the most significant issues or opportunities for improvement, based on the 80/20 rule, which states that 80% of the effects come from 20% of the causes.
* Using the data below, a Pareto chart can be created as follows:
Table
Unit
HAI Rate (%)
A
5
B
7
C
12
D
4
* The Pareto chart shows that Unit C has the highest HAI rate (12%), followed by Unit B (7%), Unit A (5%), and Unit D (4%). The cumulative line shows that Unit C alone accounts for 40% of the total HAI rate, and Units C and B together account for 63.3% of the total HAI rate. Therefore, according to the Pareto principle, the quality improvement coordinator should focus on Unit C, as it represents the most significant problem area and the greatest opportunity for improvement.
* The quality improvement coordinator can then conduct a root cause analysis to identify the possible factors or causes that contribute to the high HAI rate in Unit C, such as staff compliance, infection control practices, patient characteristics, environmental factors, etc. A root cause analysis can be facilitated by using a visual tool such as a fishbone diagram, which organizes possible factors into categories, such as people, process, equipment, environment, etc. The quality improvement coordinator can also collect and compare data from other units or sources to identify gaps and best practices.
* Based on the root cause analysis, the quality improvement coordinator can then develop and implement an action plan to address the identified causes and improve the HAI rate in Unit C. The action plan should include specific, measurable, achievable, relevant, and time-bound (SMART) goals, interventions, and indicators. The quality improvement coordinator can also involve the staff and leaders of Unit C in the planning and implementation process, to ensure their engagement and ownership of the improvement efforts.
* The quality improvement coordinator should also monitor and evaluate the progress and outcomes of the action plan, using data collection and analysis tools such as run charts, control charts, or statistical process control (SPC), which can show the variation and trends in the HAI rate over time. The quality improvement coordinator should also provide feedback and recognition to the staff and leaders of Unit C, and make adjustments to the action plan as needed, based on the data and evidence.
References:
* NAHQ HQ Principles, Module 2: Data Management, Lesson 2.3: Data Analysis Tools, Topic 2.3.1:
Pareto Chart, Topic 2.3.2: Fishbone Diagram
* NAHQ Learning Lab: The Role of the Healthcare Quality Professional in Population Health Management, Module 3: Data Collection and Analysis, Slide 16: Pareto Chart, Slide 18: Fishbone Diagram
* NAHQ Journal for Healthcare Quality, Volume 42, Issue 5, September/October 2020, Article:
Utilization of Improvement Methodologies by Healthcare Quality Professionals During the COVID-19 Pandemic, Page 283: Figure 1. Pareto Chart of COVID-19 Cases by State as of June 30, 2020
* NAHQ News and Media, News: Shaping the Future of the Healthcare Quality Profession, Paragraph 5:
The Role of the Quality Improvement Coordinator
* NAHQ Resources, Healthcare Quality Solutions: Ready Your Workforce for Quality, Page 5: The Role of the Quality Improvement Coordinator
NEW QUESTION # 21
......
Do you want to improve your IT skills in a shorter time as soon as possible but lacking of proper training materials? Don't worry, with PDFDumps CPHQ exam training materials, any IT certification exam can be easily coped with. Our CPHQ Exam Training materials is the achievement that PDFDumps's experienced IT experts worked out through years of constant exploration and practice. PDFDumps will be your best choice.
High CPHQ Quality: https://www.pdfdumps.com/CPHQ-valid-exam.html
2026 Latest PDFDumps CPHQ PDF Dumps and CPHQ Exam Engine Free Share: https://drive.google.com/open?id=1HsZ5dHENW9zajq65hMEfyyh3-S3_BsE2