DOWNLOAD the newest ActualPDF EFM PDF dumps from Cloud Storage for free: https://drive.google.com/open?id=1FMkrEZ-b-8Vi4-7HnQcut9hy_LegAiGJ
The customers don't need to download or install excessive plugins or software to get the full advantage from web-based Certified - Electronic Fetal Monitoring (EFM) practice tests. Additionally, all operating systems also support this format. The third format is the desktop EFM practice exam software. It is ideal for users who prefer offline Certified - Electronic Fetal Monitoring (EFM) exam practice. This format is supported by Windows computers and laptops. You can easily install this software in your system to use it anytime to prepare for the examination.
| Section | Weight | Objectives |
|---|---|---|
| Physiology | 11% | - Uteroplacental function - Factors affecting fetal oxygenation - Fetal cardiovascular physiology |
| Electronic Monitoring Equipment | 5% | - Proper application and use - Calibration and accuracy - Troubleshooting artifacts |
| Pattern Recognition and Intervention | 70% | - Clinical decision-making and interventions - Interpretation per NICHD standards - Fetal heart rate patterns classification - Tracing evaluation and management |
| Professional Issues | 5% | - Legal and ethical aspects - Safety and quality improvement - Documentation standards |
| Fetal Assessment and Methods | 9% | - Correlation with clinical status - Auxiliary assessment techniques - Indications for monitoring |
With constantly updated NCC pdf files providing the most relevant questions and correct answers, you can find a way out in your industry by getting the EFM certification. Our EFM test engine is very intelligence and can help you experienced the interactive study. In addition, you will get the scores after each EFM Practice Test, which can make you know about the weakness and strengthen about the EFM real test , then you can study purposefully.
NEW QUESTION # 123
A 20-year-old woman (G1P0) at 40-weeks gestation was admitted for cervical ripening with dinoprostone (Cervidil) four hours ago. She developed the pattern shown one hour ago. She has been changed to a lateral position and given a fluid bolus, and the pattern continues. An appropriate intervention would be to: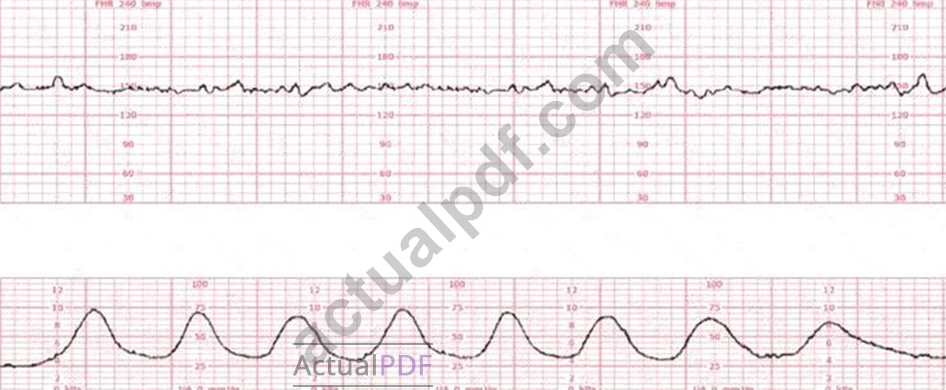
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The tracing shows tachysystole (more than 5 contractions in 10 minutes) with minimal variability and recurrent decelerations consistent with uteroplacental insufficiency caused by excessive uterine activity.
Dinoprostone (Cervidil) is a uterotonic prostaglandin, and one of its known complications is uterine tachysystole with Category II or III fetal heart rate patterns.
NCC/AWHONN guidance for tachysystole caused by prostaglandins:
* FIRST intervention: Remove the dinoprostone insert.
* Reposition the patient (already done).
* IV fluid bolus (already done).
* Consider terbutaline only if tachysystole persists after removal of the agent.
Since maternal repositioning and IV fluids have already failed, the next step is to remove the cervical ripening agent.
Why other answers are incorrect:
* A. Continue to observe - Never acceptable with tachysystole + fetal intolerance.
* B. Terbutaline - May be used after prostaglandin removal, not before.
Thus, the correct answer is C. Remove the dinoprostone insert.
References:NCC C-EFM Candidate Guide; AWHONN Fetal Heart Monitoring Principles & Practices; Menihan; Miller's Pocket Guide; NICHD Definitions; Creasy & Resnik.
NEW QUESTION # 124
A fetal heart rate deceleration that is episodic is a/an:
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
NCC and NICHD differentiate:
* Periodic decelerations - those occurring with contractions
* Episodic decelerations - those occurring independent of contractions
Deceleration types:
* Early - periodic (mirror contractions)
* Late - periodic (after peak of contraction)
* Variable - may be periodic or episodic, and are the only type strongly associated with episodic patterns** Therefore, the only deceleration type that is characteristically episodic is a variable deceleration.
Correct answer: C. Variable deceleration
References:NICHD FHR Definitions; NCC C-EFM Guide; AWHONN; Menihan; Simpson & Creehan.
NEW QUESTION # 125
A woman (G1, P0) at 41-weeks gestation presents to OB triage to rule out labor. Her cervical exam is 1 cm/50%/-2. Membranes are intact. She would like to go home if not in labor. Based on this tracing, which represents the last two hours, the best approach is: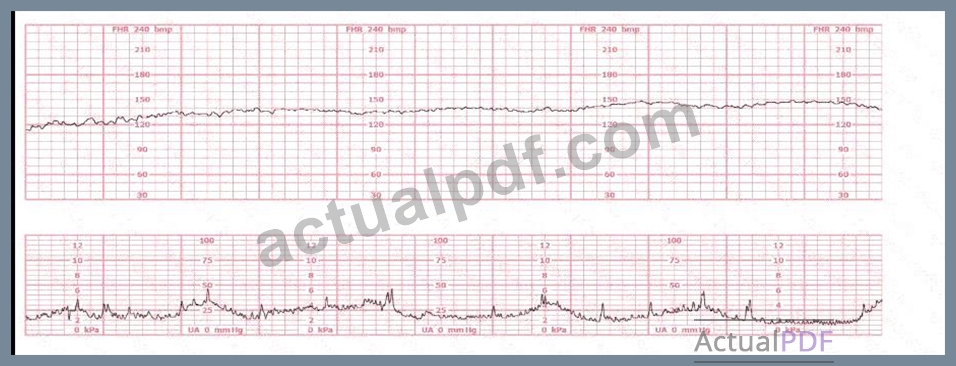
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources The fetal heart rate tracing shows a normal baseline (120-150 bpm), moderate variability, and no decelerations, consistent with a Category I pattern. According to AWHONN's Fetal Heart Monitoring Principles & Practices and NCC Perinatal Safety recommendations, a Category I tracing reliably indicates normal fetal acid-base status at the time of assessment and is considered reassuring.
Simpson & Creehan emphasize that in triage, management decisions depend on cervical status, contraction pattern, membrane status, and fetal well-being. With a cervix at 1 cm/50%/-2, intact membranes, and no regular labor pattern, she is not in active or latent labor requiring admission, provided fetal status is reassuring.
Menihan states that a normal tracing lasting two hours with moderate variability supports safe discharge when maternal and fetal assessments are normal. Creasy & Resnik confirm that reassuring fetal testing plus absence of labor is appropriate for outpatient management.
References:
AWHONN - Fetal Heart Monitoring Principles & PracticesSimpson & Creehan - Perinatal NursingMenihan
- Electronic Fetal MonitoringCreasy & Resnik - Maternal-Fetal MedicineMiller's Pocket Guide
NEW QUESTION # 126
A fetus displays a baseline heart rate of 125 beats per minute with moderate variability. During a contraction, the baseline rate drops abruptly to 80 beats per minute with gradual return to baseline over 90 seconds. This is classified as:
Answer: A
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
NICHD definitions:
A variable deceleration is identified by:
* Abrupt onset(drop from baseline to nadir in <30 seconds)
* Depth #15 bpm
* Duration #15 seconds and <2 minutes
* Variable timing relative to contractions
* Variable shape (sharp drop, jagged descents, rapid recovery)
The scenario describes:
* Abrupt drop from 125 # 80 bpm (rapid onset)
* Lasting 90 seconds (still <2 minutes)
* Gradual return but still within variable range
* Occurring during a contraction
* Depth >15 bpm
This meets ALL criteria for a variable deceleration.
Why the other options are wrong:
* A. Early deceleration
* Requires gradual onset (>30 seconds).
* Mirrors contraction shape.
* Caused by head compression.
* This decel is abrupt, so NOT early.
* B. Prolonged deceleration
* Requires #2 minutes and <10 minutes.
* This decel lasts 90 seconds, which is below the threshold.
Correct classification: Variable deceleration.
References:NICHD FHR Definitions; NCC Pattern Recognition Domain; AWHONN FHMPP; Menihan; Simpson & Creehan.
NEW QUESTION # 127
This fetal heart rate pattern is classified as Category III based on: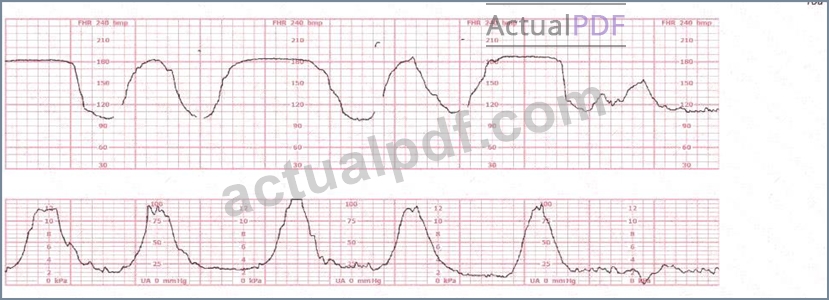
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
This tracing shows recurrent late decelerations accompanied by absent variability.
Per NICHD/NCC, a tracing is Category III if ANY of the following are present:
* Absent variability AND recurrent late decelerations
* Absent variability AND recurrent variable decelerations
* Absent variability AND bradycardia
* Sinusoidal pattern
In this strip:
* Variability is absent
* Decelerations are recurrent and late
The determining feature for the classification is absent variability, which indicates significant risk for fetal acidemia.
The contraction pattern (option B) does not determine category.
The deceleration type alone (option C) does not determine Category III without absent variability.
Thus, the classification is Category III because of absent variability.
References:NCC C-EFM Candidate Guide; NICHD Three-Tier System; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring.
NEW QUESTION # 128
......
You still can pass the exam with our help. The key point is that you are serious on our NCC EFM exam questions and not just kidding. Our EFM practice engine can offer you the most professional guidance, which is helpful for your gaining the certificate. And our Certified - Electronic Fetal Monitoring EFM learning guide contains the most useful content and keypoints which will come up in the real exam.
Reliable Test EFM Test: https://www.actualpdf.com/EFM_exam-dumps.html
P.S. Free & New EFM dumps are available on Google Drive shared by ActualPDF: https://drive.google.com/open?id=1FMkrEZ-b-8Vi4-7HnQcut9hy_LegAiGJ