BTW, DOWNLOAD part of PassTestking EFM dumps from Cloud Storage: https://drive.google.com/open?id=1VjFnx-WvKlRGKUO6YUzzT7UDfUNcS9xV
If you choose the help of PassTestking, we will spare no effort to help you pass the exam. Moreover, we also provide you with a year of free after-sales service to update the exam practice questions and answers. Do not hesitate! Please select PassTestking, it will be the best guarantee for you to pass EFM Certification Exam. Now please add PassTestking to your shopping cart.
| Section | Weight | Objectives |
|---|---|---|
| Topic 1: Pattern Recognition and Intervention | 70% | - Maternal and Fetal Complications
|
| Topic 2: Fetal Assessment Methods | 9% | - Assessment Techniques
|
| Topic 3: Professional Issues | 5% | - Clinical Practice and Safety
|
| Topic 4: Electronic Monitoring Equipment | 5% | - Monitoring Systems
|
| Topic 5: Physiology | 11% | - Maternal-Fetal Physiology
|
Victory won't come to me unless I go to it. It is time to start to clear exam and obtain an IT certification to improve your competitor from our NCC EFM training PDF if you don't want to be discarded by epoch. Many IT workers have a nice improve after they get a useful certification. If you are willing, our EFM Training Pdf can give you a good beginning. No need to doubt and worry, thousands of candidates choose our exam training materials, you shouldn't miss this high pass-rate EFM training PDF materials.
NEW QUESTION # 60
A 30-minute tracing with moderate variability, accelerations, and one variable deceleration would be classified as:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
NICHD/NCC criteria:
Category I must have ALL of the following:
* Baseline 110-160 bpm
* Moderate variability
* No late or variable decelerations
* Early decelerations may be present or absent
* Accelerations may be present or absent
Because this tracing has one variable deceleration, it fails Category I criterion ("no late or variable decelerations").
Category III requires:
* Absent variability with recurrent late decels, recurrent variables, or bradycardia, or
* Sinusoidal pattern
Those findings are not present.
Therefore, any tracing that:
* Has moderate variability and accelerations,
* But includes a variable deceleration, and
* Does not meet Category III criteria
...falls into the Category II (indeterminate) group.
Correct classification: B. Category II.
References:NCC C-EFM Candidate Guide; NICHD Three-Tier FHR Interpretation System; AWHONN FHMPP; Menihan; Simpson & Creehan.
NEW QUESTION # 61
A fetal heart rate tracing is abnormal. A change in maternal position and oxygen administration do not correct the pattern. Following birth, a fetal cord blood sample is taken:
pH = 7.25
PaCO# = 46 mm Hg
PaO# = 20 mm Hg
HCO# = 22 mEq/L
Base deficit = -4 mEq/L
These results are best interpreted as:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
Normal umbilical arterial values per NCC/AWHONN/Menihan:
* pH: 7.20-7.30
* PaCO#: 45-55 mmHg
* HCO#: 20-24 mEq/L
* Base deficit: 0 to -5 (normal to mild respiratory changes)
This sample shows:
* pH 7.25 # normal
* Base deficit -4 # no metabolic acidosis
* HCO# normal
* Slightly elevated PaCO#, consistent with mild respiratory influence but still normal
* PaO# 20 mmHg is normal for cord arterial blood
This profile is not acidotic (acidosis requires pH <7.10 and base deficit #12).
It also does not indicate hypoxia, which would present with metabolic acidosis.
Therefore: Normal.
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; Menihan; Simpson & Creehan; Creasy & Resnik.
NEW QUESTION # 62
Based on the fetal heart rate tracing shown, the expected fetal pH would be: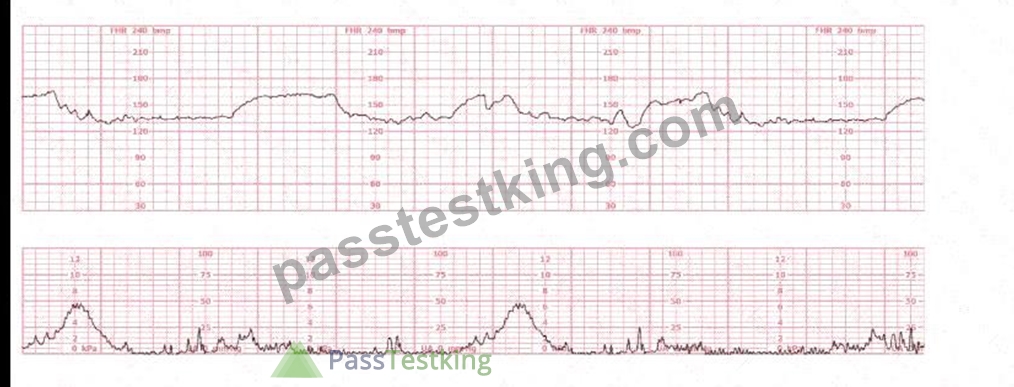
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
Assessment of likely fetal acid-base status is grounded in NCC-aligned principles that correlate fetal pH with fetal heart rate patterns, especially variability, presence/absence of accelerations, and type and depth of decelerations.
This tracing shows the following features:
Baseline:
The fetal heart rate baseline is approximately 140-150 bpm, within the normal 110-160 bpm range.
Variability:
Moderate variability is present-approximately 6-25 bpm amplitude.
Per NCC and NICHD definitions, moderate variability is strongly associated with normal fetal oxygenation and normal fetal pH > 7.20-7.25.
Accelerations:
There are occasional small accelerations, another strong indicator of normal fetal acid-base status.
Decelerations:
The tracing shows occasional variable decelerations, shallow and brief, recovering rapidly, typical of intermittent cord compression.
NCC references emphasize that intermittent, non-recurrent variables with moderate variability do not correlate with acidemia.
Uterine activity:
Contractions are present but not excessive, and fetal response remains reassuring.
Correlating tracing features with fetal pH (per NCC, AWHONN, Simpson, Menihan):
Moderate variability is the strongest intrapartum indicator of normal fetal pH.
The NICHD/NCC consensus repeatedly states that:
"The presence of moderate variability reliably predicts adequate fetal oxygenation and a fetal pH above the threshold associated with metabolic acidemia." Fetal pH below 7.15 is associated with:
Absent variability
Recurrent late decelerations
Recurrent deep variable decelerations
Prolonged bradycardia
None are present in this tracing.
Because the tracing demonstrates moderate variability, intermittent uncomplicated variables, and no recurrent late decelerations, the physiologic expectation is that the fetal pH remains normal, significantly above 7.15.
Therefore, the correct answer is: A (above 7.15).
References:
NCC C-EFM Candidate Guide (2025); NCC Content Outline; NICHD Interpretation System; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 63
A pattern of recurrent variable decelerations would move from Category II to Category III if what fetal heart rate change occurs?
Answer: B
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
Category III criteria include:
* Absent variability with recurrent variable decelerations
* Absent variability with recurrent lates
* Absent variability with bradycardia
* Sinusoidal pattern
Thus, recurrent variables become Category III when accompanied by absent variability, indicating fetal decompensation.
Why the other answers are wrong:
* B. Late decelerations # Category III only if combined with absent variability.
* C. Tachysystole # Contraction pattern, not a FHR characteristic.
Correct answer: Absent variability.
References:NCC C-EFM Candidate Guide; NICHD Definitions; AWHONN FHMPP.
NEW QUESTION # 64
A woman is being induced with oxytocin. The tracing shown is representative of 20 minutes. Based on this tracing, the next step would be to: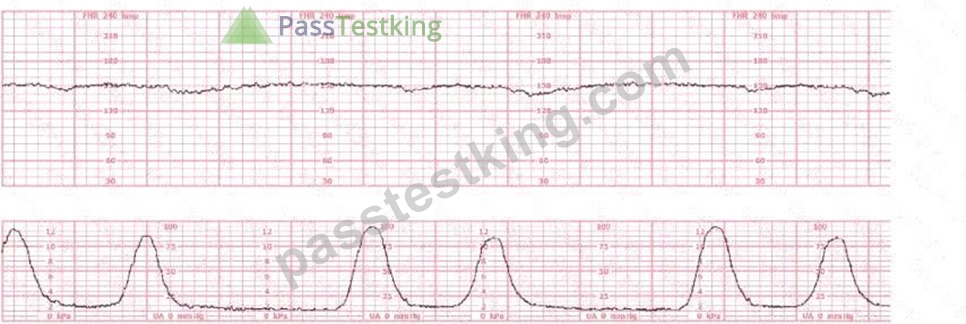
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
Evaluation of a tracing during oxytocin induction requires analysis of fetal status (baseline, variability, accelerations, decelerations) and uterine activity, with attention to tachysystole and fetal intolerance. NCC, AWHONN, Miller, Menihan, Simpson, and the NICHD guidelines all emphasize that oxytocin must be adjusted based on fetal response and contraction frequency.
Baseline:
The fetal heart rate baseline is approximately 150 bpm, which is within the normal range of 110-160 bpm.
Variability:
The tracing shows minimal variability (approximately 1-4 bpm amplitude). Minimal variability for a sustained period is categorized as a Category II pattern under NCC/NICHD classification.
Accelerations:
No accelerations are present during the 20-minute representative segment.
Decelerations:
There are no recurrent variable, no recurrent late, and no prolonged decelerations.
Uterine Activity:
The tracing shows very frequent contractions-approximately every 1½ to 2 minutes, which meets the NCC definition of tachysystole when averaged over 10 minutes (more than 5 contractions in 10 minutes).
According to NCC and AWHONN standards, when tachysystole is present with minimal variability, oxytocin must be reduced or discontinued even in the absence of late decelerations.
Clinical decision-making (per NCC principles):
NCC emphasizes that management of Category II patterns during induction starts with intrauterine resuscitative measures, including decreasing or stopping oxytocin when uterine activity is excessive or fetal response is suboptimal. Minimal variability with tachysystole requires correction of uterine stimulation before escalating to invasive monitoring or considering operative birth.
Option B (place a spiral electrode) is not indicated because the pattern is clearly visible and the priority is correcting uterine overstimulation, not refining the tracing.
Option C (operative birth) is not indicated; there is no Category III pattern or recurrent decelerations.
Option A (discontinue oxytocin) is the correct first-line action according to NCC-aligned guidelines when tachysystole and minimal variability occur.
References:
NCC C-EFM Candidate Guide (2025); NCC Content Outline; NICHD Three-Tier FHR Interpretation System; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 65
......
PassTestking wants to win the trust of NCC EFM exam candidates at any cost. To achieve this objective PassTestking is offering some top features with EFM exam practice questions. These prominent features hold high demand and are specifically designed for quick and complete Certified - Electronic Fetal Monitoring (EFM) exam questions preparation.
Valid EFM Exam Objectives: https://www.passtestking.com/NCC/EFM-practice-exam-dumps.html
What's more, part of that PassTestking EFM dumps now are free: https://drive.google.com/open?id=1VjFnx-WvKlRGKUO6YUzzT7UDfUNcS9xV