BTW, DOWNLOAD part of ActualVCE EFM dumps from Cloud Storage: https://drive.google.com/open?id=1wNqa781N6Jf9afwoL3m3GMnI1SK8zfeA
To get better condition of life, we all need impeccable credentials of different exams to prove individual’s capacity. However, weak EFM practice materials may descend and impair your ability and flunk you in the real exam unfortunately. And the worst condition is all that work you have paid may go down the drain for those EFM question torrent lack commitments and resolves to help custEFMomers. Moreover, only need toEFM spend 20-30 is it enough for you to grasp whole content of EFM practice materials that you can pass the exam easily, this is simply unimaginable.
| Section | Weight | Objectives |
|---|---|---|
| Pattern Recognition and Intervention | 70% | - Fetal Heart Rate Patterns
|
| Electronic Monitoring Equipment | 5% | - Monitoring Systems
|
| Fetal Assessment Methods | 9% | - Assessment Techniques
|
| Professional Issues | 5% | - Clinical Practice and Safety
|
| Physiology | 11% | - Maternal-Fetal Physiology
|
Frankly speaking, it is difficult to get the EFM certificate without help. Usually, the time you invest to prepare the exam is long. Now, all of your worries can be wiped out because of our EFM exam questions. Some people worry about that some difficult knowledge is hard to understand or the EFM test guide is not suitable for them. Actually, the difficult parts of the exam have been simplified, which will be easy for you to understand. Also, there will be examples, simulations and charts to make explanations vivid. In order to aid you to memorize the Certified - Electronic Fetal Monitoring exam cram better, we have integrated knowledge structure. You will clearly know what you are learning and which part you need to learn carefully. You will regret if you give up challenging yourself.
NEW QUESTION # 42
Interventions undertaken to address fetal tachycardia are targeted at maximizing
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources Fetal tachycardia is typically caused by maternal fever, dehydration, hypoxia, medications, infection, or fetal stress. AWHONN and Simpson & Creehan emphasize that management focuses on improving oxygen delivery across the placenta, which is governed by uteroplacental perfusion.
Menihan's EFM text states that "interventions for fetal tachycardia must address oxygen transfer by optimizing uteroplacental blood flow," including hydration, reducing uterine activity, maternal repositioning, and treating maternal fever.
Increasing maternal circulation alone is insufficient unless it improves placental blood flow. Enhancing fetal sympathetic tone is not a clinical goal and would worsen tachycardia.
Creasy & Resnik highlight that fetal heart rate abnormalities resolve when uteroplacental perfusion is restored, confirming this as the primary target of intervention.
References:
AWHONN - Fetal Heart Monitoring Principles & PracticesSimpson & Creehan - Perinatal NursingMenihan
- Electronic Fetal MonitoringCreasy & Resnik - Maternal-Fetal MedicineMiller's Pocket Guide
NEW QUESTION # 43
This tracing reflects: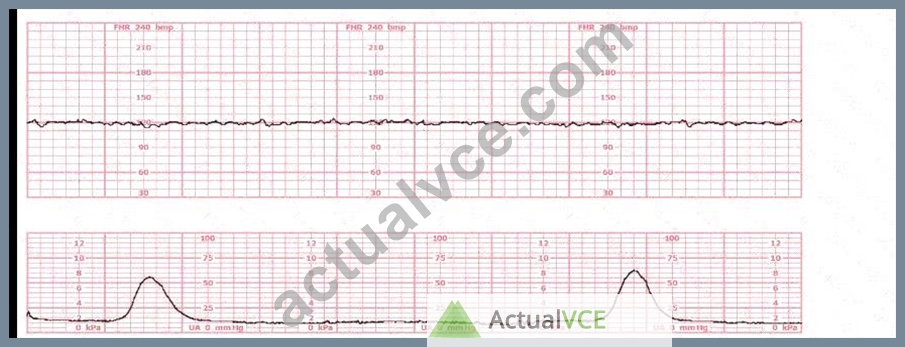
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
In NCC C-EFM interpretation, classification of a fetal heart tracing is based on NICHD's three-tier system:
Category I, II, and III. Category III represents an abnormal tracing requiring immediate evaluation and prompt intervention.
Key findings in this tracing:
* Baseline:Baseline is approximately 140 bpm, within the normal range (110-160 bpm).Baseline alone does not determine category.
* Variability:The tracing shows absent variability:
* No beat-to-beat oscillations
* Flat, minimal fluctuationNICHD and NCC define absent variability as amplitude range undetectable.
* Accelerations:No accelerations are present.
* Decelerations:The strip does not show decelerations or bradycardia.However, absent variability alone with no accelerations for 20 minutes is highly concerning.
Category Classification per NICHD/NCC:
Category III criteria include ANY of the following:
* Absent variability with recurrent late decelerations
* Absent variability with recurrent variable decelerations
* Absent variability with bradycardia
* Sinusoidal pattern
Also recognized as Category III:
* Persistent absent variability lasting #20 minutes with no accelerations, which is strongly suggestive of fetal acidemia when sustained.
This tracing shows:
* Absent variability (flat line)
* No accelerations
* Persisting over an extended period
Under NCC and AWHONN guidance:
A persistently flat tracing must be classified as Category III unless proven otherwise (e.g., fetal sleep, maternal medications), and it requires immediate intrauterine resuscitation and evaluation for potential expedited delivery.
Why Category I is NOT correct:
Category I requires:
* Moderate variability
* No late or variable decelerationsThis tracing does not have moderate variability.
Why Category II is NOT correct:
Category II includes minimal variability, marked variability, intermittent variables/lates, absence of accelerations after stimulation.
This tracing is worse than Category II because variability is absent, not minimal.
Thus, the tracing fits Category III.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline; NICHD Three-Tier FHR Interpretation System; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 44
This tracing has lasted for 20 minutes in a woman who is 6 cm dilated. The most appropriate intervention is: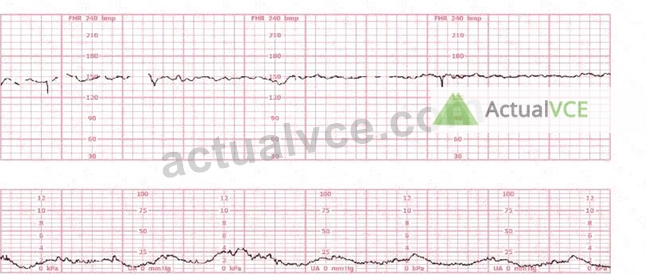
Answer: C
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
This tracing shows:
* Baseline approximately 135-140 bpm
* Minimal variability
* No accelerations
* No recurrent decelerations
* Category II for 20 minutes
According to NCC, AWHONN, and NICHD, minimal variability persisting # 20 minutes without accelerations requires assessment of fetal acid-base status, and fetal scalp stimulation is an accepted method to evaluate fetal well-being when a Category II tracing persists.
Fetal scalp stimulation:
* Should produce an acceleration # 15 bpm lasting # 15 seconds
* A positive response indicates intact fetal nervous system and normal pH
* If no acceleration occurs # further intrauterine resuscitation or expedited delivery may be required Why other options are incorrect:
* A. Delivery - Not indicated; this is Category II, not Category III.
* C. IV bolus - IV hydration may improve variability, but assessment of fetal status comes first after
20 minutes of minimal variability.
Thus, the correct answer is B. Fetal scalp stimulation.
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; NICHD Three-Tier System; Menihan; Miller's Pocket Guide; Simpson & Creehan.
NEW QUESTION # 45
A pattern of recurrent variable decelerations would move from Category II to Category III if what fetal heart rate change occurs?
Answer: A
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
Category III criteria include:
* Absent variability with recurrent variable decelerations
* Absent variability with recurrent lates
* Absent variability with bradycardia
* Sinusoidal pattern
Thus, recurrent variables become Category III when accompanied by absent variability, indicating fetal decompensation.
Why the other answers are wrong:
* B. Late decelerations # Category III only if combined with absent variability.
* C. Tachysystole # Contraction pattern, not a FHR characteristic.
Correct answer: Absent variability.
References:NCC C-EFM Candidate Guide; NICHD Definitions; AWHONN FHMPP.
NEW QUESTION # 46
(Full question statement)
This tracing is consistent with: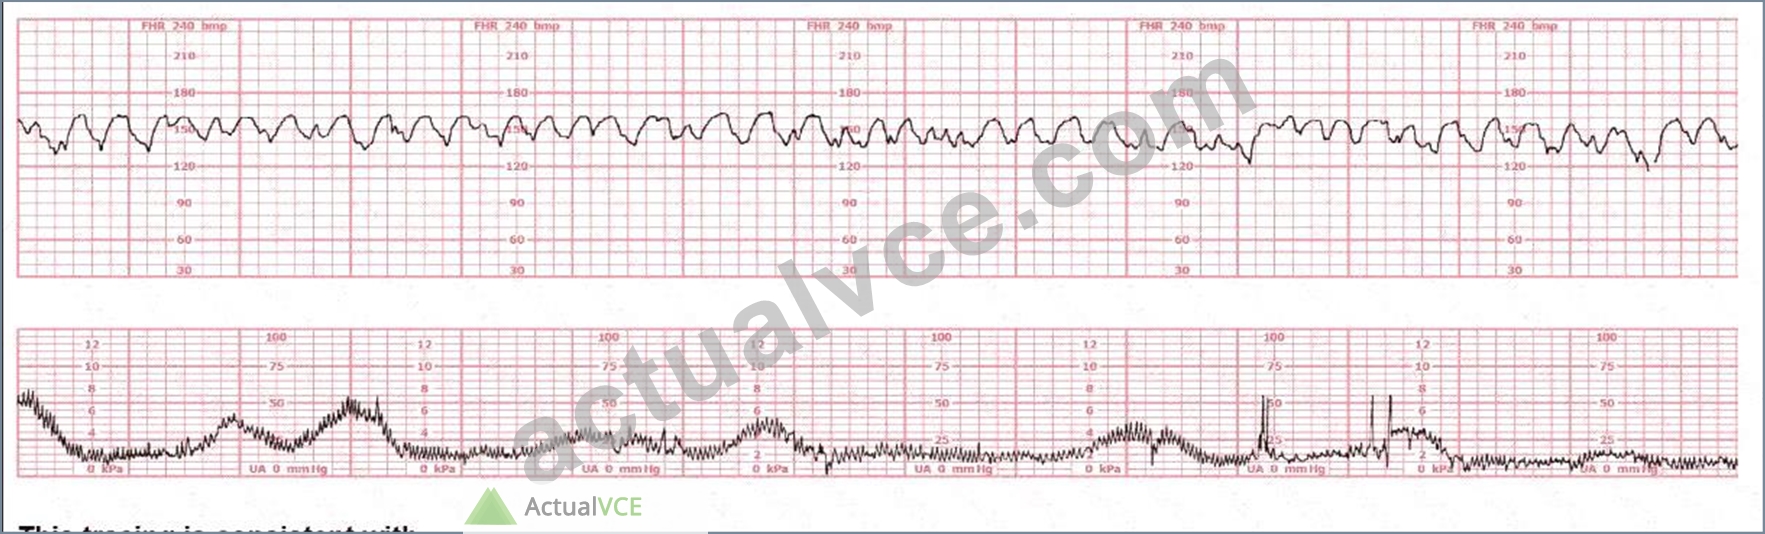
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract Without Links:
NCC and AWHONN teaching materials describe that butorphanol, an opioid analgesic, characteristically produces a transient sinusoidal-like pattern or pseudo-sinusoidal pattern with moderate variability preserved.
This drug-related pattern has:
* smooth, regular oscillations
* maintained variability
* absence of true periodic decelerations
* resolution within 20-60 minutes
Simpson & Menihan describe butorphanol as producing a "saw-tooth, wavering pattern" often mistaken for dysrhythmia but actually benign.
True sinusoidal patterns (e.g., fetal-maternal hemorrhage) are fixed, smooth, non-variable patterns with absent variability, not matching the scenario.
Atrial flutter produces very rapid atrial contractions, which manifest as irregular baseline spikes-also not consistent.
Therefore, the described tracing aligns most closely with butorphanol effects.
NEW QUESTION # 47
......
In addition to the free download of sample questions, we are also confident that candidates who use EFM study materials will pass the exam at one go. EFM study materials are revised and updated according to the latest changes in the syllabus and the latest developments in theory and practice. Regardless of your weak foundation or rich experience, EFM study materials can bring you unexpected results. In the past, our passing rate has remained at 99%-100%. This is the most important reason why most candidates choose EFM Study Materials. Failure to pass the exam will result in a full refund. But as long as you want to continue to take the EFM exam, we will not stop helping you until you win and pass the certification.
EFM Valid Study Materials: https://www.actualvce.com/NCC/EFM-valid-vce-dumps.html
DOWNLOAD the newest ActualVCE EFM PDF dumps from Cloud Storage for free: https://drive.google.com/open?id=1wNqa781N6Jf9afwoL3m3GMnI1SK8zfeA