Testpdf始終致力于為客戶提供高品質的學習資料,來提高考生一次性通過ACDIS CCDS考試的概率,這是考生獲取認證最佳捷徑。我們的CCDS認證PDF和軟件版本具有最新更新的問題解答,涵蓋了所有考試題目和課題大綱,在線測試引擎測試可以幫助您準備并熟悉實際考試情況。在您決定購買我們產品之前,您可以先免費嘗試ACDIS CCDS PDF版本的DEMO,此外,我們還提供全天24/7的在線支持,以便為客戶提供最好的便利服務。
| Section | Weight | Objectives |
|---|---|---|
| Topic 1: Medical record documentation | 19.17% | - Physician query formats - Addressing diagnoses without clinical support - Documentation requiring clarification - Provider role and diagnosis code assignment - Translating clinical indicators into compliant queries - Types of physician queries - Clinical indicators - ACDIS/AHIMA Guidelines for Achieving a Compliant Query Practice - Situations in which queries are not appropriate - When a physician query is warranted - Compliant and noncompliant queries - Health record elements used for diagnosis and procedure code assignment |
| Topic 2: Anatomy and physiology, pathophysiology, pharmacology, and medical terminology | 19.17% | - Diseases and disorders of the kidney and urinary tract - Diagnostic tests as clinical indicators - Medications as clinical indicators - Diseases and disorders of the musculoskeletal system - Diseases and disorders of the circulatory system - Diseases and disorders of the skin, subcutaneous tissue, and breast - HIV infections - Pharmaceuticals and disease processes - Diseases and disorders of the respiratory system - Clinical indicators and query opportunities by Major Diagnostic Category - Standard medical abbreviations - Diseases and disorders of the hepatobiliary system - Diseases and disorders of the digestive system - Diseases and disorders of the nervous system - Diseases and disorders of the blood and blood-forming organs and immunological disorders - Injuries, poisonings, and toxic effects of drugs - Alcohol/drug use and alcohol/drug-induced organic brain disorders - Endocrine, nutritional, and metabolic diseases and disorders - Infectious and parasitic diseases - Myeloproliferative diseases and disorders and poorly differentiated neoplasms - Mental diseases and disorders |
| Topic 3: Official Guidelines for Coding and Reporting | 14.17% | - Present on admission indicators - Hospital-acquired conditions - AHA Coding Clinic - Principal diagnosis assignment - Working DRG assignment for multiple diagnoses - Official Guidelines for Coding and Reporting updates - Secondary diagnosis assignment - Discharge dispositions and transfers - Coding guidelines for principal diagnosis selection |
| Topic 4: Impact of reportable diagnoses on quality of care | 8.33% | - Mortality reviews and observed/expected ratios - 30-day mortality measures - CDI impact on Hospital Value-Based Purchasing - Hospital Readmissions Reduction Program - Patient Safety Indicators - Coded data elements affecting Patient Safety Indicators - Hospital Value-Based Purchasing - Quality data from record abstraction and claims data - Documentation and code assignment impact on mortality index - Hospital-Acquired Condition Reduction Program - Hospital Inpatient Quality Reporting Program - Healthcare-associated infections and complication codes |
| Topic 5: Healthcare regulations, reimbursement, and documentation requirements related to the IPPS | 12.5% | - IPPS and its updates and revisions - Medicare contractors and their impact on CDI - Coding and billing practices vulnerable to denial - Major complication/comorbidity (MCC) - Case mix index (CMI) - Documentation impact on IPPS reimbursement - Medicare Severity Diagnosis Related Groups (MS-DRGs) - Principal diagnosis and medical necessity - Medical staff and clinical staff documentation responsibilities - Inpatient admission criteria and CMS Two-Midnight Rule - Complication/comorbidity (CC) - Documentation and medical necessity of setting |
| Topic 6: Healthcare facility CDI program analysis | 8.33% | - High-frequency DRGs - CDI program forecasting - Severity of illness and risk of mortality - Hospital Value-Based Purchasing measures - Publicly reported data - PEPPER data - Provider response rates - Tracking and trending physician, department, and hospital performance - Case mix index (CMI) - CC/MCC capture - Basic computer and software application skills - Patient Safety Indicators - CDI specialist productivity metrics - Physician performance measurement - Hospital-specific financial data |
| Topic 7: Professionalism, ethics, and compliance | 9.17% | - Compliance risks indicated by PEPPER - Potential DRG creep - Leading queries - CDI department goals beyond reimbursement - Medical record confidentiality - DRG compliance initiatives |
| Topic 8: Communication skills | 9.17% | - Reconciling CDI working DRGs with final coded DRGs - Physician education forms and tools - Roles and responsibilities of coders working with CDI departments - Verbal versus written physician communication - Effective and non-confrontational physician communication - Educational presentations for healthcare departments and administration - Roles and responsibilities of CDI specialists |
選擇最適合的ACDIS CCDS題庫學習資料,并來獲得認證,它能加速您在信息技術行業里快速成長,也是加薪升遷的成功選擇。在取得您第一個CCDS認證后,您還可以參加其它的IT認證考試,Testpdf的考古題能幫助獲得更多的成功。我們擁有超多十年的IT認證經驗,在我們的支援下,您可以順利的ACDIS CCDS考試。我們還承諾,對于使用我們CCDS考古題失敗的考生,將提供100%無條件退款。
問題 #50
A patient with colon cancer is admitted solely for transfusion and management of anemia caused directly by the malignancy. No chemotherapy-related adverse effect is involved. Which condition is sequenced first?
答案:A
解題說明:
When the admission is for management of anemia associated directly with the malignancy, and treatment is directed only at the anemia, the malignancy is sequenced as principal diagnosis, followed by the appropriate anemia code.
The FY 2026 Official Guidelines specifically distinguish malignancy-associated anemia from anemia caused by chemotherapy. For anemia associated with the malignancy, the neoplasm is sequenced first. For anemia resulting from an adverse effect of chemotherapy or immunotherapy, the anemia code is sequenced first.
This distinction makes documentation of anemia etiology essential. Phrases such as "anemia in cancer patient" may not clearly establish whether anemia is attributable to malignancy, chemotherapy, bleeding, nutritional deficiency, chronic kidney disease, or another process.
An encounter code for transfusion does not replace the principal-diagnosis rules for an inpatient hospitalization when the underlying reason for treatment is established.
Likewise, weakness is a symptom and would not supersede the definitive documented cancer-related anemia.
CDI professionals should therefore look beyond the fact that transfusion occurred and identify whether the medical record clearly establishes the cause of the anemia.
CCDS Reference Topics: Neoplasm-related anemia; principal diagnosis; sequencing; chemotherapy versus malignancy; medical record specificity.
=========
問題 #51
A hospital reports 80 observed deaths when its risk-adjustment methodology predicted 100 expected deaths.
What is the observed-to-expected mortality ratio, and what does it indicate?
答案:C
解題說明:
The observed-to-expected mortality ratio is calculated as:
80 observed deaths ÷ 100 expected deaths = 0.80.
A ratio below 1.0 means observed mortality is lower than predicted. In this case, the number of observed deaths is 20% below the expected number.
Accurate interpretation of mortality data is important for CDI because documentation contributes to the clinical information used by many risk-adjustment methodologies. If significant comorbidities or acute conditions are inadequately documented, the coded record may not fully represent the patient's severity or mortality risk.
However, CDI professionals must avoid treating risk-adjustment improvement as justification for unsupported diagnoses. Documentation should accurately represent conditions that were clinically present, evaluated, treated, monitored, or otherwise reportable according to applicable rules.
The official CCDS content outline specifically includes severity of illness/risk of mortality, physician documentation effects on public reporting, and analysis of hospital performance among its expected competencies.
Mortality ratios should also be interpreted in context; they are influenced by patient population, model methodology, documentation, coding accuracy, and actual clinical outcomes.
CCDS Reference Topics: O/E mortality; ROM; risk adjustment; quality outcomes; CDI program analysis.
=========
問題 #52
A 34-year-old female was admitted from a group home with uncontrolled diabetes. A CDI specialist must query to specify the patient's mental incapacity since it makes management of the diabetes more difficult.
Which of the following terminology recognized by ICD-10-CM could result in the assignment of a comorbid condition?
答案:B
解題說明:
Severe intellectual disability is recognized ICD-10-CM terminology and maps to F72, Severe intellectual disabilities. The other phrases are not equivalent standardized ICD-10-CM diagnostic terminology.
This distinction is highly relevant to CDI. Terms used conversationally in the clinical record do not necessarily provide sufficient specificity or map cleanly to reportable ICD-10-CM diagnoses. When a patient's cognitive or developmental condition affects treatment, monitoring, self-management, nursing requirements, or the complexity of care, the CDI specialist should seek clinically appropriate provider documentation using recognized diagnostic terminology.
For FY 2026 MS-DRG logic, CMS identifies F72 as a CC, meaning it can qualify as a complication
/comorbidity when it meets secondary-diagnosis reporting requirements. That does not mean the CDI specialist should query merely for reimbursement impact. The query must be clinically justified by the record and should allow the provider to determine the correct diagnosis.
"Severe mental challenge," "acute mental incapacity," and "acute intellectual disability" do not represent the same codable disease classification.
CCDS Reference Topics: Medical terminology; mental/behavioral and neurodevelopmental disorders; CC recognition; clinically supported query opportunities.
=========
問題 #53
The table below shows physician performance: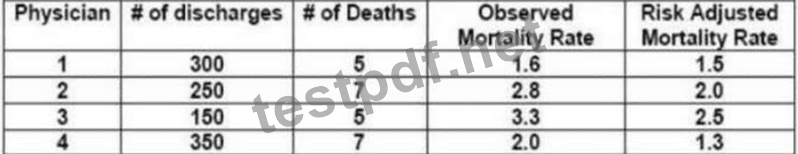
Which of the following physicians will have the most favorable mortality rate on a public website, such as Healthgrades.com?
答案:B
解題說明:
Physician 4 has the most favorable risk-adjusted mortality rate, at 1.3, compared with Physician 1 at 1.5, Physician 2 at 2.0, and Physician 3 at 2.5. Although Physician 1 has fewer observed deaths and an observed mortality rate of 1.6%, public outcome comparisons commonly incorporate risk adjustment rather than relying solely on raw mortality. Risk adjustment attempts to account for differences in patient complexity, comorbid disease burden, demographic factors, and other characteristics that influence expected outcomes.
This is directly relevant to CDI because incomplete documentation of clinically significant comorbidities can understate patient severity and therefore adversely affect the expected mortality component of risk-adjusted performance calculations. Conversely, accurate documentation allows coded data to represent the actual severity and risk of the population being treated. Healthgrades specifically states that its mortality methodology adjusts for patient risk factors to permit more meaningful comparisons of clinical outcomes.
The CCDS content outline specifically requires knowledge of mortality indices, severity of illness/risk of mortality, physician performance, and the effect of documentation on publicly reported data.
CCDS Reference Topics: Impact of reportable diagnoses on quality of care; Healthcare facility CDI program analysis; mortality index and risk adjustment.
=========
問題 #54
A CDI specialist has been asked to present a report to hospital administration that will demonstrate the CDI program's impact over time. Which of the following reports will BEST accomplish this?
答案:A
解題說明:
A line graph showing Risk of Mortality (ROM) and Severity of Illness (SOI) by month provides the strongest evidence of program impact over time because it displays longitudinal trends. Hospital leadership can readily determine whether documented patient complexity and risk profiles are increasing, decreasing, or remaining stable and can correlate those trends with CDI interventions.
The CCDS content outline specifically requires CDI specialists to analyze program trends, use SOI/ROM and other program-performance methodologies, create forecasting data, evaluate hospital performance, and track metrics over time. A line graph is particularly appropriate because time is the independent variable and changes from month to month are immediately visible.
An individual specialist's query rate primarily measures productivity or workflow rather than overall organizational impact. A pie graph of unanswered queries provides a snapshot of one process metric, not longitudinal program effectiveness. A presentation of program goals and objectives communicates strategy but does not demonstrate measurable results.
ROM and SOI also connect CDI work to quality and risk-adjustment outcomes, making them particularly meaningful to senior hospital administration.
CCDS Reference Topics: Healthcare facility CDI program analysis; trend analysis; SOI/ROM; physician and hospital performance.
=========
問題 #55
......
我相信不論在哪個行業工作的人都希望自己有很好的職業前景。當然在競爭激烈的IT行業裏面也不例外。在IT行業中工作的專業人士也希望自己有個很好的提升機會和很大的提升空間。很多專業的IT人士都知道ACDIS CCDS 認證考試可以幫你滿足這些願望的。而Testpdf是一個能幫助你成功通過ACDIS CCDS 的網站。
CCDS熱門證照: https://www.testpdf.net/CCDS.html