P.S. Free 2026 NCC EFM dumps are available on Google Drive shared by DumpsTorrent: https://drive.google.com/open?id=1VbI3zbqHCe9CsScoc0oVZ1wi9yu7fe2v
The best strategy to enhance your knowledge and become accustomed to the EFM Exam Questions format is to test yourself. DumpsTorrent NCC EFM practice tests (desktop and web-based) assist you in evaluating and enhancing your knowledge, helping you avoid viewing the NCC test as a potentially daunting experience. If the reports of your NCC practice exams (desktop and online) aren't perfect, it's preferable to practice more. EFM self-assessment tests from DumpsTorrent works as a wake-up call, helping you to strengthen your EFM preparation ahead of the NCC actual exam.
| Section | Weight | Objectives |
|---|---|---|
| Topic 1: Electronic Monitoring Equipment | 5% | - Monitoring Systems
|
| Topic 2: Fetal Assessment Methods | 9% | - Assessment Techniques
|
| Topic 3: Pattern Recognition and Intervention | 70% | - Fetal Heart Rate Patterns
|
| Topic 4: Physiology | 11% | - Maternal-Fetal Physiology
|
| Topic 5: Professional Issues | 5% | - Clinical Practice and Safety
|
Test your knowledge of the EFM exam dumps with NCC EFM practice questions. The software is designed to help with Certified - Electronic Fetal Monitoring (EFM) exam dumps preparation. NCC EFM Practice Test software can be used on devices that range from mobile devices to desktop computers.
NEW QUESTION # 69
In documenting auscultation of the fetal heart rate, it is important to record findings in relationship to:
Answer: C
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
NCC and AWHONN auscultation standards emphasize the need to document FHR findings relative to uterine contractions, including:
* The FHR between contractions (baseline)
* FHR during contractions
* Presence/absence of decelerations
* Recovery after a contraction
Uterine activity determines whether findings are:
* Baseline
* Accelerations
* Early/late/variable decelerations
Why the other options are incorrect:
* A. Fetal position - relevant for Doppler placement, not auscultation documentation.
* B. Stage of labor - affects monitoring frequency but does not change how findings are documented.
Correct answer: C. Uterine activity.
References:NCC C-EFM Candidate Guide; AWHONN Standards for FHR Auscultation; Simpson & Creehan.
NEW QUESTION # 70
This fetal heart rate tracing is obtained upon the woman's admission to labor and delivery. This tracing is most reflective of: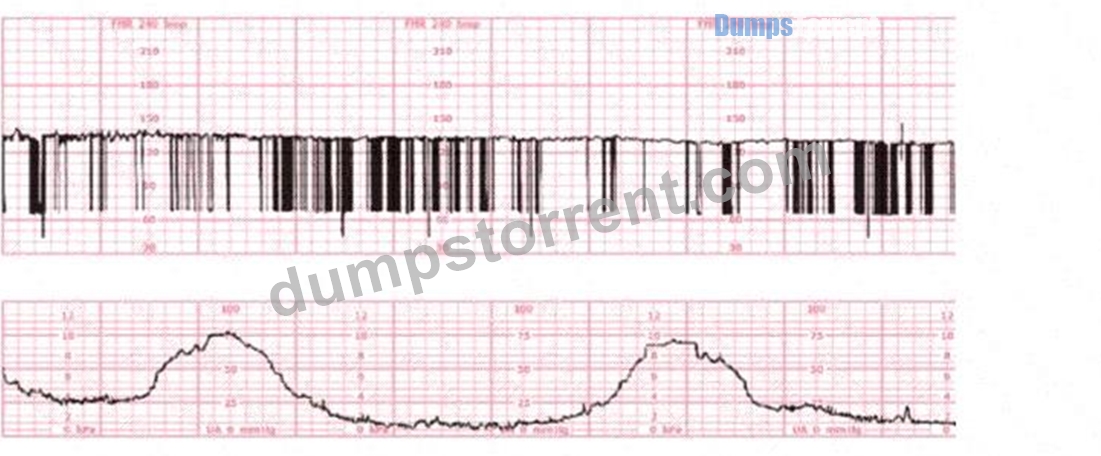
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
When evaluating an admission tracing, NCC emphasizes determining whether the pattern represents baseline variability abnormalities, signal artifact, or an underlying fetal cardiac rhythm disturbance. The strip shown contains clear features of a fetal dysrhythmia, which NCC and AWHONN describe as an irregular rhythm characterized by inconsistent R-R intervals or intermittent missed beats.
Key features in this tracing:
* Extremely irregular FHR signalThe pattern shows abrupt vertical spikes, inconsistent spacing, and intermittent loss of coherent waveform. NCC teaches that this appearance is typical of irregular ventricular conduction or premature atrial/ventricular contractions.
* Wide variability in beat spacingBeat intervals vary significantly, suggesting ectopic beats or conduction abnormalities rather than a stable rhythm such as heart block or atrial flutter.
* Sensor not malfunctioningThe lower uterine activity channel is smooth and consistent, meaning the upper channel's abrupt changes represent true FHR signal irregularity, not artifact.
Why the incorrect answers are ruled out:
A). Atrial flutter - NOT supported
* Atrial flutter produces a very fast, regular atrial rate (typically 300 bpm) with a repetitive saw-tooth pattern.
* It does not produce the highly irregular beat-to-beat pattern seen here.
* FHR in atrial flutter appears more organized, not chaotic.
B). Complete heart block - NOT supported
* Complete heart block (third-degree AV block) produces a very slow, regular ventricular rate, commonly 50-70 bpm, with a dissociation between atrial and ventricular rhythms.
* The tracing here does not show a slow, steady baseline.
* Instead, the rhythm is highly irregular with spikes and losses-not characteristic of AV block.
C). Fetal dysrhythmia - CORRECT
* NCC, AWHONN, Miller, and Menihan describe fetal dysrhythmias as:"Irregular, inconsistent FHR patterns due to premature atrial contractions (PACs), premature ventricular contractions (PVCs), or intermittent conduction disturbances."
* The hallmark is an irregular rhythm, often appearing as abrupt spikes or missing beats on the monitor.
* The tracing shown matches these characteristics precisely.
Therefore, the tracing is most consistent with fetal dysrhythmia, typically benign PACs/PVCs, and is the correct answer.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 71
Intermittent fetal heart rate auscultation for a low-risk, spontaneous laboring patient who is 4-5 centimeters dilated should be assessed at intervals every
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract (No URLs or Links) NCC aligns with AWHONN's "Practice Guidelines for Fetal Heart Monitoring", which specify the appropriate frequency of intermittent auscultation (IA) based on labor phase and risk level. For low- risk patients in active labor, IA must occur:
* Every 15-30 minutes during active labor
* Every 5 minutes during second stage with pushing
AWHONN and Menihan emphasize that intermittent auscultation must follow standardized time intervals to ensure adequate fetal surveillance. These intervals reflect the physiologic understanding that fetal compromise may evolve over relatively short time periods, and active labor (4-7 cm dilation) represents a time of increasing stress on fetal oxygenation.
Simpson & Creehan explain that IA frequency should increase as labor intensifies, and that the 15-30- minute interval is the nationally recognized standard for low-risk active labor. NCC's exam content domain "Fetal Assessment Methods" reinforces knowing these surveillance intervals for safe low- intervention care.
Thus, for a 4-5 cm dilated, low-risk, spontaneous labor, the correct IA interval is every 15-30 minutes.
References (No URLs)
* NCC C-EFM Candidate Guide 2025 - Fetal Assessment Methods
* AWHONN Practice Guidelines for Fetal Heart Monitoring, 2022-2024
* Menihan: Electronic Fetal Monitoring
* Simpson & Creehan: Perinatal Nursing
* Miller: Fetal Monitoring Pocket Guide
NEW QUESTION # 72
The main reason intrauterine pressure catheters are placed is to:
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
Intrauterine pressure catheters (IUPCs) are an internal uterine activity monitoring device used when external tocodynamometry does not provide adequate assessment of contraction strength or frequency.
According to NCC, AWHONN, Miller, and Menihan, the primary indication for placing an IUPC is to obtain accurate, quantitative measurement of uterine activity.
Purpose of IUPC (per NCC and AWHONN):
* Measures exact intrauterine pressure in mmHg
* Calculates Montevideo units (MVUs) to evaluate adequacy of labor
* Clearly differentiates:
* Frequency
* Duration
* Strength (intensity)
* Resting tone
NCC explicitly lists the primary purpose as:
"Accurate assessment of uterine contraction pattern and intensity."
Why the other options are incorrect:
A). Define the quality of the fetal baseline - Incorrect
* Fetal heart rate (FHR) baseline quality is determined by fetal ECG or FSE, not IUPC.
* IUPCs monitor the uterus, not the fetal cardiac signal.
C). Rule out artifact - Incorrect
* While an IUPC can reduce artifact from the toco, this is not its primary purpose.
* Artifact is more commonly an issue with external FHR monitoring, corrected by repositioning or placing a fetal scalp electrode-not by using an IUPC.
B). Determine the contraction pattern
This aligns directly with NCC's Electronic Monitoring Equipment domain: IUPCs provide the most accurate and reliable measurement of uterine activity when external monitoring is inadequate.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 73
The tracing shown is a: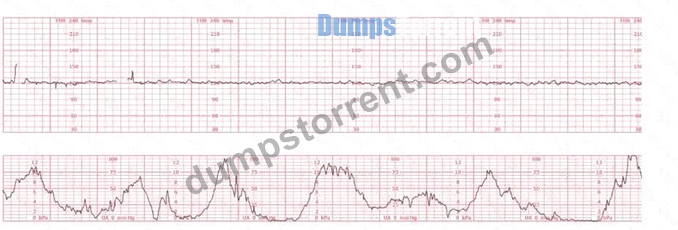
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References (No URLs):
Interpretation of fetal heart rate (FHR) tracings in the NCC C-EFM exam follows the standardized NICHD three-tier classification, which is fully adopted in NCC's content outline and recommended references such as AWHONN Fetal Heart Monitoring Principles & Practices, Miller's EFM Pocket Guide, Menihan, Simpson' s Perinatal Nursing, and Creasy & Resnik.
Baseline:
The tracing demonstrates an FHR baseline around 145-150 bpm, which falls within the normal range of 110-
160 bpm. NCC references define baseline as the mean FHR rounded to increments of 5 bpm over a 10-minute window.
Variability:
The strip shows minimal variability, with amplitude fluctuations approximately 0-2 bpm.
According to NCC-aligned definitions:
* Moderate variability: 6-25 bpm
* Minimal variability: 1-5 bpm
* Absent variability: undetectable amplitude
This tracing shows minimal variability, not moderate, so it cannot be Category I.
Accelerations:
No accelerations are present. Lack of accelerations alone does not classify the tracing as Category III.
Decelerations:
There are no recurrent late decelerations, no recurrent variable decelerations, and no prolonged decelerations. Without these, and with minimal variability, the tracing does not meet Category III criteria.
Category III criteria (per NICHD/NCC):
Must include at least one of the following:
* Absent variability with recurrent late decelerations
* Absent variability with recurrent variable decelerations
* Absent variability with bradycardia
* Sinusoidal pattern
None of these are present.
Category II criteria (per NICHD/NCC):
Category II includes tracings that are not Category I or III.
Examples specifically listed include:
* Minimal variability
* Absent accelerations after fetal stimulation
* Tachycardia
* Bradycardia without absent variability
* Variable or late decelerations occurring intermittently
Because this tracing shows minimal variability, a normal baseline, no accelerations, and no recurrent decelerations, it fits squarely into Category II.
Therefore, the correct classification is Category II.
References:NCC C-EFM Candidate Guide and Content Outline (2025); AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine; NICHD Three-Tier FHR Interpretation System.
NEW QUESTION # 74
......
Our website of the EFM study guide only supports credit card payment, but do not support card debit card, etc. Pay attention here that if the money amount of buying our EFM study materials is not consistent with what you saw before, you need to see whether you purchased extra copies of the product or were taxed. As our EFM Guide materials are sold all around the world, you can find that the content and language is easy to understand.
Download EFM Fee: https://www.dumpstorrent.com/EFM-exam-dumps-torrent.html
P.S. Free & New EFM dumps are available on Google Drive shared by DumpsTorrent: https://drive.google.com/open?id=1VbI3zbqHCe9CsScoc0oVZ1wi9yu7fe2v