BONUS!!! Download part of Dumpcollection EFM dumps for free: https://drive.google.com/open?id=165HfsgvwISGaoanTL-dmrCvYkpBV1UoR
You only need 20-30 hours to learn EFM exam torrent and prepare the EFM exam. Many people, especially the in-service staff, are busy in their jobs, learning, family lives and other important things and have little time and energy to learn and prepare the EFM exam. But if you buy our EFM Test Torrent, you can invest your main energy on your most important thing and spare 1-2 hours each day to learn and prepare the exam. Our EFM exam questions and answers are based on the real exam and conform to the popular trend in the candidates.
| Section | Objectives |
|---|---|
| Topic 1: Fetal Physiology and Oxygenation | - Fetal cardiovascular physiology - Oxygen transport and acid-base balance |
| Topic 2: Maternal and Fetal Complications | - High-risk obstetric conditions affecting fetal monitoring - Hypoxia and uteroplacental insufficiency |
| Topic 3: Fetal Heart Rate Interpretation | - Category I, II, and III tracing interpretation - Accelerations and decelerations - Baseline rate and variability |
| Topic 4: Uterine Activity | - Normal uterine contraction patterns - Tachysystole and abnormal contraction patterns |
| Topic 5: Intrauterine Resuscitation and Interventions | - Fluid management and medication adjustments - Maternal position changes and oxygen administration |
| Topic 6: Intrapartum Assessment and Monitoring | - Risk assessment during labor - External and internal monitoring techniques |
In order to meet the different demands of the different customers, these experts from our company have designed three different versions of the EFM study materials. All customers have the right to choose the most suitable version according to their need after buying our study materials. The PDF version of the EFM Study Materials has many special functions, including download the demo for free, support the printable format and so on.
NEW QUESTION # 92
This tracing reflects: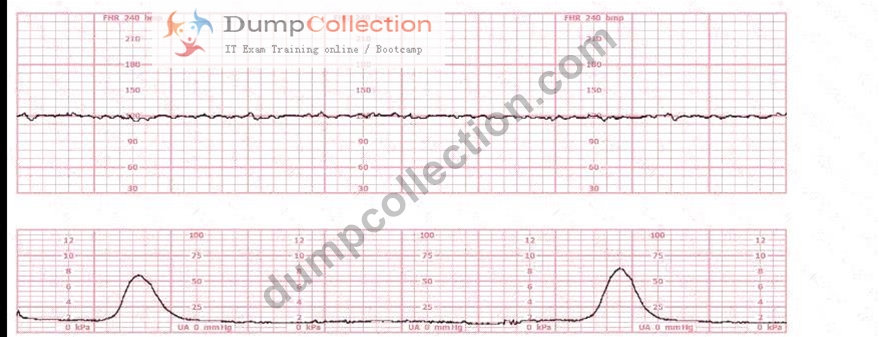
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
In NCC C-EFM interpretation, classification of a fetal heart tracing is based on NICHD's three-tier system:
Category I, II, and III. Category III represents an abnormal tracing requiring immediate evaluation and prompt intervention.
Key findings in this tracing:
* Baseline:Baseline is approximately 140 bpm, within the normal range (110-160 bpm).Baseline alone does not determine category.
* Variability:The tracing shows absent variability:
* No beat-to-beat oscillations
* Flat, minimal fluctuationNICHD and NCC define absent variability as amplitude range undetectable.
* Accelerations:No accelerations are present.
* Decelerations:The strip does not show decelerations or bradycardia.However, absent variability alone with no accelerations for 20 minutes is highly concerning.
Category Classification per NICHD/NCC:
Category III criteria include ANY of the following:
* Absent variability with recurrent late decelerations
* Absent variability with recurrent variable decelerations
* Absent variability with bradycardia
* Sinusoidal pattern
Also recognized as Category III:
* Persistent absent variability lasting #20 minutes with no accelerations, which is strongly suggestive of fetal acidemia when sustained.
This tracing shows:
* Absent variability (flat line)
* No accelerations
* Persisting over an extended period
Under NCC and AWHONN guidance:
A persistently flat tracing must be classified as Category III unless proven otherwise (e.g., fetal sleep, maternal medications), and it requires immediate intrauterine resuscitation and evaluation for potential expedited delivery.
Why Category I is NOT correct:
Category I requires:
* Moderate variability
* No late or variable decelerationsThis tracing does not have moderate variability.
Why Category II is NOT correct:
Category II includes minimal variability, marked variability, intermittent variables/lates, absence of accelerations after stimulation.
This tracing is worse than Category II because variability is absent, not minimal.
Thus, the tracing fits Category III.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline; NICHD Three-Tier FHR Interpretation System; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 93
Tachysystole can have a negative effect on fetal oxygenation during labor by
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources NCC-recommended physiology references (AWHONN, Simpson & Creehan, Menihan, Creasy & Resnik) consistently state that the primary mechanism by which tachysystole affects fetal oxygenation is reduced uteroplacental perfusion, specifically through impaired intervillous space reperfusion.
During a normal contraction cycle, the fetus receives oxygen between contractions, when the uterus relaxes and maternal blood re-enters the intervillous space. AWHONN's Fetal Heart Monitoring Principles & Practices explains that tachysystole-defined as more than five contractions in 10 minutes averaged over 30 minutes-shortens or eliminates the relaxation phase, preventing adequate placental reoxygenation.
Simpson & Creehan highlight that "tachysystole decreases uteroplacental blood flow and interferes with replenishment of oxygenated maternal blood in the intervillous space." Menihan emphasizes that fetal hypoxemia in tachysystole results from interrupted perfusion, not from altered oxygen transport or maternal hemodynamic changes. Creasy & Resnik confirm that uterine overactivity reduces intervillous perfusion during contractions and impairs fetal oxygen exchange.
Thus, the physiologic problem is failure of the intervillous space to reperfuse, which compromises fetal oxygenation.
References:
AWHONN - Fetal Heart Monitoring Principles & PracticesSimpson & Creehan - Perinatal NursingMenihan
- Electronic Fetal MonitoringCreasy & Resnik - Maternal-Fetal MedicineMiller's Pocket Guide
NEW QUESTION # 94
During the second stage of labor, a period of bradycardia develops. The fetal heart rate baseline variability is moderate. The most likely cause of this bradycardia is:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
Second-stage bradycardia with moderate variability most commonly occurs from:
* Vagal stimulation caused by head compression, particularly during descent and pushing.
Moderate variability indicates:
* Neurologically intact fetus
* Sufficient oxygen reserve
* Temporary nature of bradycardia
This aligns with physiologic vagal slowing rather than hypoxic mechanisms.
Why the incorrect answers are wrong:
* A. Cord compression # typically produces variable decelerations, not sustained bradycardia with preserved variability.
* C. Vasospasm # associated with late decelerations and decreased variability (uteroplacental insufficiency).
Correct answer: B. Vagal stimulation
References:NCC Physiology Domain; AWHONN FHMPP; Menihan; Simpson & Creehan.
NEW QUESTION # 95
A patient at 41 weeks gestation is being induced. She has progressed slowly and is now at 6 cm, 90% effaced,
-1 station. She has the fetal heart tracing shown despite repositioning. The next step in the management of this patient should be to: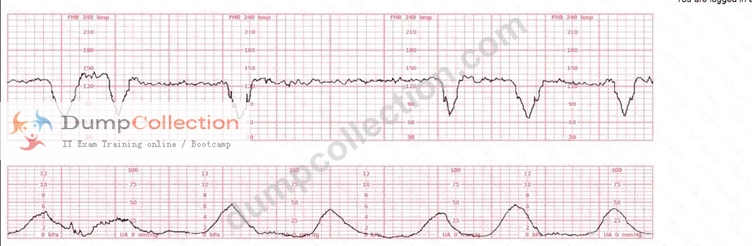
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The tracing clearly shows recurrent deep variable decelerations, characterized by:
* Abrupt onset (<30 sec)
* Sharp V-shape
* Rapid descent and ascent
* Depth exceeding 60-70 bpm drops
* Occurring with most contractions
This pattern is highly consistent with cord compression, which is the physiologic basis of variable decelerations. According to NCC, NICHD, AWHONN, Miller, and Menihan, recurrent (#50% of contractions) deep variables with slow return to baseline indicate fetal compromise and require targeted intervention.
The patient has already been repositioned, so first-line management has failed. NCC emphasizes that the next recommended intervention for recurrent variable decelerations, particularly when maternal repositioning is ineffective, is amnioinfusion. This intervention relieves cord compression by restoring fluid around the umbilical cord.
Why the other choices are incorrect:
A). Apply a spiral electrode - NOT appropriate
* Spiral electrodes improve signal quality but do not treat cord compression.
* The tracing is already clearly interpretable, and the issue is physiologic, not technical.
B). Decrease the oxytocin - Not the best next step
* Decreasing oxytocin is appropriate when tachysystole is contributing to fetal intolerance.
* This strip shows normal contraction frequency (about every 2-3 minutes) and no tachysystole.
* Thus, reducing oxytocin alone will not relieve cord compression.
C). Perform an amnioinfusion - CORRECT
NCC-approved references repeatedly state:
* For recurrent variable decelerations that persist after maternal repositioning, amnioinfusion is recommended to reduce the frequency and depth of decelerations.
* It can improve fetal oxygenation, decrease cord compression, and reduce the need for operative delivery.
* It is the intervention most directly targeted to the pathophysiology of this pattern.
Therefore, C. Perform an amnioinfusion is the correct next management step.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline; NICHD FHR Interpretation System; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal- Fetal Medicine.
NEW QUESTION # 96
In the event of recurrent variable decelerations with thick meconium, amnioinfusion is recommended to:
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
Amnioinfusion is considered an intrauterine resuscitative intervention used specifically for recurrent variable decelerations caused by cord compression. NCC, AWHONN, Miller, and Menihan consistently teach that variables occur when the umbilical cord becomes compressed, reducing fetal oxygenation. When oligohydramnios or decreased amniotic fluid volume is present, the cord is more vulnerable to compression.
Why amnioinfusion is used:
Amnioinfusion works by:
Increasing intraamniotic fluid volume
Reducing umbilical cord compression
Decreasing the frequency and severity of variable decelerations
This directly targets the pathophysiology behind recurrent variables.
Why the other options are incorrect:
A). Dilute thick meconium - NOT supported by NCC
Historically, amnioinfusion was studied for meconium dilution, but major organizations-including NCC- aligned sources-state that amnioinfusion is NOT recommended for the sole purpose of diluting meconium. It does not reduce meconium aspiration syndrome and is no longer indicated for that purpose.
B). Restore uterine blood flow - NOT accurate
Uterine blood flow is addressed through maternal positioning, fluid bolus, reducing uterine tachysystole, and minimizing vasoconstriction-not via amnioinfusion. Amnioinfusion does not physiologically affect uterine perfusion.
C). Treat oligohydramnios - CORRECT
Recurrent variables with thick meconium often occur in the setting of low fluid, which worsens cord compression.
NCC-recommended indications include:
Recurrent variable decelerations unresponsive to repositioning
Suspected or confirmed oligohydramnios
Thick meconium may be associated with low fluid, but the purpose of amnioinfusion is to alleviate cord compression by restoring fluid volume, not to dilute the meconium.
Thus, the correct answer is C. Treat oligohydramnios.
References:
NCC C-EFM Candidate Guide (2025); NCC Content Outline; AWHONN Fetal Heart Monitoring Principles
& Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 97
......
Today is the right time to advance your career. Yes, you can do this easily. Just need to pass the EFM certification exam. Are you ready for this? If yes then get registered in NCC EFM certification exam and start preparation with top-notch Dumpcollection EFM Exam Practice questions today. These NCC EFM questions are available at Dumpcollection with up to 1 year of free updates.
Top EFM Dumps: https://www.dumpcollection.com/EFM_braindumps.html
BONUS!!! Download part of Dumpcollection EFM dumps for free: https://drive.google.com/open?id=165HfsgvwISGaoanTL-dmrCvYkpBV1UoR