試験の知識が豊富な専門家によってコンパイルされたEFM試験トレントをすべての受験者に提供し、EFM学習教材のコンパイルの経験が豊富です。最新バージョンを入手したら、できるだけ早くメールボックスに送信します。 EFM試験問題では、学生が練習に20〜30時間を費やすだけでEFM試験に合格する自信が持てるので、一部の労働者にとっては非常に便利です。 EFM試験に合格して目標を達成するための最良のツールでなければなりません。
| Section | Weight | Objectives |
|---|---|---|
| Topic 1: Pattern Recognition and Intervention | 70% | - Fetal Heart Rate Patterns
|
| Topic 2: Electronic Monitoring Equipment | 5% | - Monitoring Systems
|
| Topic 3: Professional Issues | 5% | - Clinical Practice and Safety
|
| Topic 4: Fetal Assessment Methods | 9% | - Assessment Techniques
|
| Topic 5: Physiology | 11% | - Maternal-Fetal Physiology
|
EFM学習教材を世界中に確実に紹介し、幸運とより良い機会を求めるすべての人々が自分の人生の価値を実現できるようにするという大胆な考えを持っています。したがって、EFM練習問題は、EFM試験に合格し、より良い未来を勝ち取るのに役立ちます。また、常に先駆的な精神を持ち続け、あなたの道を歩むプロジェクトに積極的に取り組みます。 EFMトレーニング資料は、その素晴らしい品質のためにあなたを決して失望させません。
質問 # 60
After spontaneous rupture of membranes, this fetal heart rate pattern is observed. The initial intervention should be to: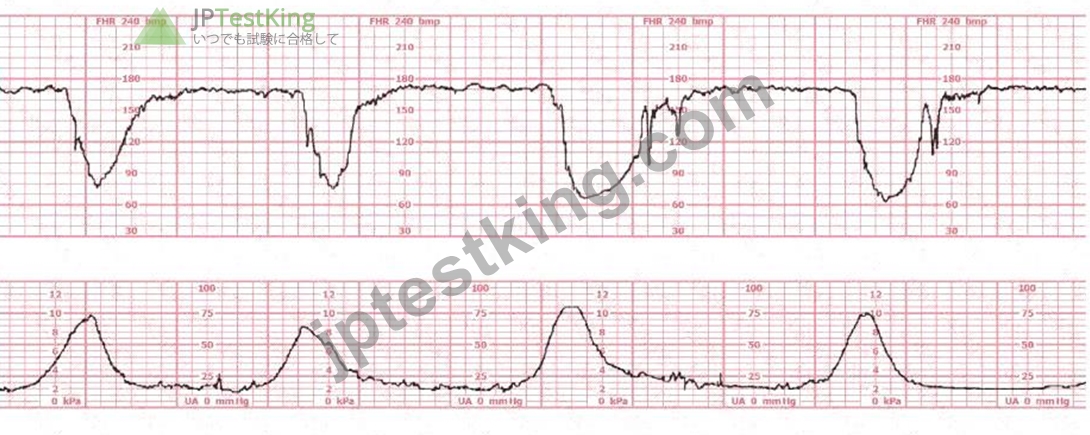
正解:A
解説:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
The strip shows abrupt, deep variable decelerations, which are highly suspicious for cord compression.
Following rupture of membranes, the FIRST step recommended by NCC/AWHONN is:
* Immediate vaginal examination to rule out cord prolapse.
Cord prolapse requires emergent action, and examination must occur before repositioning or fluids.
Why the other answers are incorrect:
* C. Left lateral positioning is appropriate after ruling out cord prolapse.
* A. IV fluids do not address the potentially life-threatening cause.
Correct first action is: vaginal examination.
References:NCC Pattern Recognition & Intervention; AWHONN FHMPP; Menihan; Simpson & Creehan.
質問 # 61
The tracing shown is from a woman at 28-weeks gestation in the post-anesthesia care unit (PACU) after an appendectomy. She is alert and awake. Based on this fetal heart rate pattern, the most appropriate intervention is: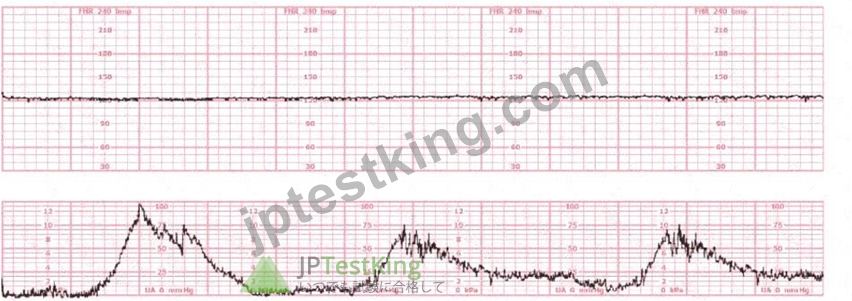
正解:A
解説:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The fetal heart rate tracing shows:
* Baseline around 140 bpm
* Minimal variability
* No accelerations
* No decelerations
* Regular uterine activity but not tachysystole
This pattern is Category II, but in the context of:
* 28-week gestation
* Immediate postoperative status after anesthesia
* Maternal alertness and stability
NCC and AWHONN emphasize that maternal sedation, post-anesthesia effects, medications, and physiologic stress commonly cause temporary minimal variability without acidemia, especially at preterm gestations where baseline variability is normally lower.
Key NCC principle:
Minimal variability in a stable mother without decelerations does NOT require emergent delivery.
Instead, the fetus should be observed as anesthesia effects wear off.
Why other answers are incorrect:
* A. Terbutaline - No tachysystole and no recurrent decels are present.
* C. Cesarean birth - No bradycardia, no late decels, no absent variability, and no Category III criteria.
Thus, appropriate management is B. Continued monitoring.
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; Menihan EFM; Miller's Pocket Guide; NICHD Definitions; Creasy & Resnik.
質問 # 62
This is a fetal heart rate tracing of a multiparous woman whose cervix is 7 cm dilated on admission. The most likely cause for this pattern is: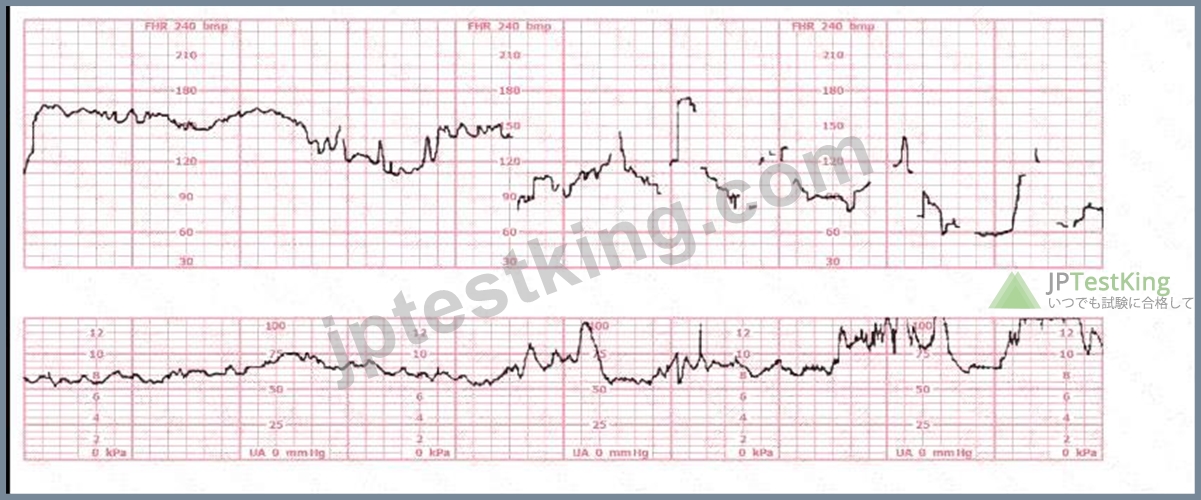
正解:C
解説:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The tracing shows a clear relationship between uterine activity and fetal heart rate changes:
* The uterine activity strip demonstrates very frequent contractions with little resting time between them, exceeding five contractions in 10 minutes, averaged over a 30-minute window.
* NCC and NICHD define tachysystole as "more than 5 contractions in 10 minutes, averaged over 30 minutes, regardless of whether the labor is spontaneous or stimulated." As uterine activity intensifies and becomes excessively frequent, the fetal heart rate strip begins to show:
* Progressive decrease in baseline
* Recurrent decelerations with gradual onset and recovery
* Reduced variability in the latter portion of the strip
This pattern is consistent with uteroplacental insufficiency caused by excessive uterine activity (tachysystole). NCC and AWHONN emphasize that tachysystole can result in decreased uterine blood flow and fetal oxygenation, leading to late or prolonged decelerations and eventual bradycardia if not corrected.
Why the other options are less likely:
* A. Placental abruptionTypically associated with maternal symptoms (pain, vaginal bleeding, firm
/boardlike uterus) and often a sustained increase in resting tone or a hypertonic contraction, not simply very frequent contractions. These maternal findings are not described in the vignette.
* B. Rapid fetal descentUsually causes variable or early decelerations related to head compression, but the tocodynamometer would not necessarily show this degree of contraction frequency. The lower strip here clearly highlights excessive contractions as the primary problem.
Thus, the tracing's FHR abnormalities are best explained by tachysystole, making C. Tachysystole the most appropriate answer.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline - Pattern Recognition and Intervention; NICHD Three-Tier FHR Interpretation System; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
質問 # 63
When R-R intervals are short, the fetal heart rate is
正解:C
解説:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources The fetal heart rate is calculated from the interval between consecutive R waves in the fetal ECG. Shorter R- R intervals indicate more beats per unit of time, therefore resulting in a higher heart rate. AWHONN and Menihan both note that fetal ECG monitoring measures instantaneous rate based on R-R spacing, and "shorter intervals correspond to fetal tachycardia." Simpson & Creehan reinforce that fetal heart rate variability and baseline are derived from these R-R intervals, with shorter intervals consistently producing faster rates. Miller's Pocket Guide describes the relationship simply: "Short R-R = faster rate; long R-R = slower rate." References:
AWHONN - Fetal Heart MonitoringMenihan - Electronic Fetal MonitoringSimpson & Creehan - Perinatal NursingMiller's Pocket GuideCreasy & Resnik - Maternal-Fetal Medicine
質問 # 64
A woman (G1, P0) at 41-weeks gestation presents to OB triage to rule out labor. Her cervical exam is 1 cm/50%/-2. Membranes are intact. She would like to go home if not in labor. Based on this tracing, which represents the last two hours, the best approach is: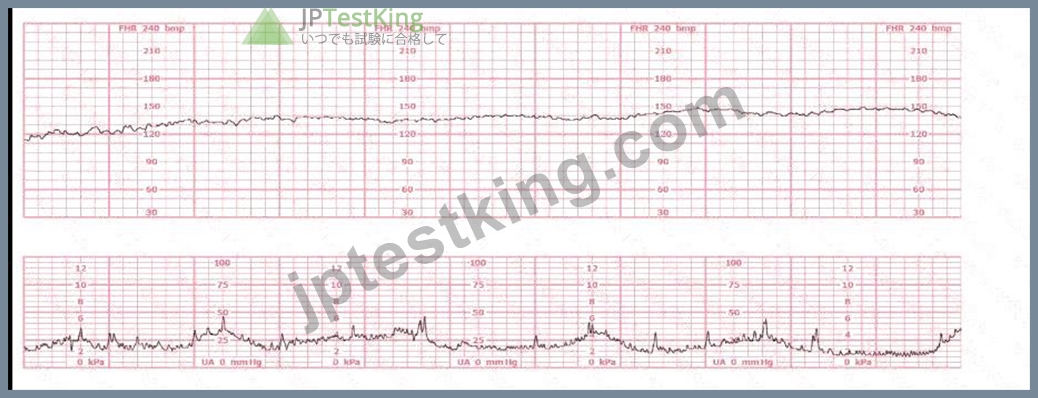
正解:A
解説:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources The fetal heart rate tracing shows a normal baseline (120-150 bpm), moderate variability, and no decelerations, consistent with a Category I pattern. According to AWHONN's Fetal Heart Monitoring Principles & Practices and NCC Perinatal Safety recommendations, a Category I tracing reliably indicates normal fetal acid-base status at the time of assessment and is considered reassuring.
Simpson & Creehan emphasize that in triage, management decisions depend on cervical status, contraction pattern, membrane status, and fetal well-being. With a cervix at 1 cm/50%/-2, intact membranes, and no regular labor pattern, she is not in active or latent labor requiring admission, provided fetal status is reassuring.
Menihan states that a normal tracing lasting two hours with moderate variability supports safe discharge when maternal and fetal assessments are normal. Creasy & Resnik confirm that reassuring fetal testing plus absence of labor is appropriate for outpatient management.
References:
AWHONN - Fetal Heart Monitoring Principles & PracticesSimpson & Creehan - Perinatal NursingMenihan
- Electronic Fetal MonitoringCreasy & Resnik - Maternal-Fetal MedicineMiller's Pocket Guide
質問 # 65
......
弊社のEFM練習資料は、さまざまな学位の受験者に適しています。これらの受験者は、この分野の知識のレベルに関係ありません。これらのEFMトレーニング資料は当社にとって名誉あるものであり、お客様の目標達成を支援するための最大限の特権として扱っています。私たちの知る限り、EFM試験準備は何百万人もの受験者に夢を追いかけ、より効率的に学習するように動機付けました。 EFMの練習資料は、あなたを失望させません。
EFMテスト難易度: https://www.jptestking.com/EFM-exam.html