BONUS!!! Download part of RealExamFree CIC dumps for free: https://drive.google.com/open?id=1Vyg--mLIO-y9bxptiRCKFWwJYD4jxjhi
It is our aspiration to help candidates get certification in their first try with our latest CIC exam prep and valid pass guide. We know the difficulty of CIC real exam so our IT experts written the best quality exam answers for our customers who didn't get good result. By using our CIC pass review, you will grasp the overall key points of the test content and solve the difficult questions easier.
| Section | Weight | Objectives |
|---|---|---|
| Topic 1: Environment of Care | 10-13% | |
| Topic 2: Identification of Infectious Disease Processes | 17-19% | |
| Topic 3: Cleaning, Sterilization, Disinfection, Asepsis | 10-13% | |
| Topic 4: Management and Communication | 10-13% | |
| Topic 5: Surveillance and Epidemiologic Investigation | 22-26% | |
| Topic 6: Preventing/Controlling the Transmission of Infectious Agents | 17-19% | |
| Topic 7: Employee/Occupational Health | 10-13% | |
| Topic 8: Education and Research | 6-9% |
>> CBIC CIC Exam Dumps Provider <<
The CIC exam questions by experts based on the calendar year of all kinds of exam after analysis, it is concluded that conforms to the exam thesis focus in the development trend, and summarize all kind of difficulties you will face, highlight the user review must master the knowledge content. And unlike other teaching platform, the CBIC Certified Infection Control Exam study question is outlined the main content of the calendar year examination questions didn't show in front of the user in the form of a long time, but as far as possible with extremely concise prominent text of CIC Test Guide is accurate incisive expression of the proposition of this year's forecast trend, and through the simulation of topic design meticulously.
NEW QUESTION # 51
The rate of catheter-associated urinary tract infections (CAUTIs) has decreased following recent practice changes. To present these results to the Quality Committee, the infection preventionist should use:
Answer: B
Explanation:
To communicate that CAUTI rates decreased after practice changes, the best tool is a run chart, which displays a measure over time and helps determine whether observed changes represent real improvement rather than random variation. The Institute for Healthcare Improvement (IHI) describes run charts as graphs of data over time and emphasizes that improvement and sustainability are demonstrated by observing patterns and shifts over time.
Run charts are especially appropriate for infection prevention metrics because they allow a Quality Committee to see: (1) the baseline period before interventions, (2) the timing of practice changes, and (3) whether there is a sustained downward trend or "shift" in CAUTI rates. Patient safety measurement guidance likewise notes that run charts are a standard quality tool to display trends in patient-safety measures over time and evaluate whether process changes are leading to improvement.
By contrast, an affinity diagram organizes ideas/themes, and fishbone diagrams and root cause analyses are primarily for analyzing causes of a problem-not for clearly presenting a time-based improvement result to leadership. A run chart is therefore the most appropriate communication method.
NEW QUESTION # 52
What question would be appropriate for an infection preventionist to ask when reviewing the discussion section of an original article?
Answer: C
Explanation:
When reviewing the discussion section of an original article, an infection preventionist must focus on critically evaluating the interpretation of the study findings, their relevance to infection control, and their implications for practice. The discussion section typically addresses the meaning of the results, compares them to existing literature, and considers limitations or alternative interpretations. The appropriate question should align with the purpose of this section and reflect the infection preventionist's need to assess the validity and applicability of the research. Let's analyze each option:
* A. Was the correct sample size and analysis method chosen?: This question pertains to the methodology section of a research article, where the study design, sample size, and statistical methods are detailed.
While these elements are critical for assessing the study's rigor, they are not the primary focus of the discussion section, which interprets results rather than re-evaluating the study design. An infection preventionist might ask this during a review of the methods section, but it is less relevant here.
* B. Could alternative explanations account for the observed results?: The discussion section often explores whether the findings can be explained by factors other than the hypothesized cause, such as confounding variables, bias, or chance. This question is highly appropriate for an infection preventionist, as it encourages a critical assessment of whether the results truly support infection control interventions or if other factors (e.g., environmental conditions, patient factors) might be responsible.
This aligns with CBIC's emphasis on evidence-based practice, where understanding the robustness of conclusions is key to applying research to infection prevention strategies.
* C. Is the study question important, appropriate, and stated clearly?: This question relates to the introduction or background section of an article, where the research question and its significance are established. While important for overall study evaluation, it is not specific to the discussion section, which focuses on interpreting results rather than revisiting the initial question. An infection preventionist might consider this earlier in the review process, but it does not fit the context of the discussion section.
* D. Are criteria used to measure the exposure and the outcome explicit?: This question is relevant to the methods section, where the definitions and measurement tools for exposures (e.g., a specific intervention) and outcomes (e.g., infection rates) are described. The discussion section may reference these criteria but focuses more on their implications rather than their clarity. This makes it less appropriate for the discussion section specifically.
The discussion section is where authors synthesize their findings, address limitations, and consider alternative explanations, making option B the most fitting. For an infection preventionist, evaluating alternative explanations is crucial to ensure that recommended practices (e.g., hand hygiene protocols or sterilization techniques) are based on solid evidence and not confounded by unaddressed variables. This critical thinking is consistent with CBIC's focus on applying research to improve infection control outcomes.
CBIC Infection Prevention and Control (IPC) Core Competency Model (updated 2023), Domain I:
Identification of Infectious Disease Processes, which emphasizes critical evaluation of research evidence.
CBIC Examination Content Outline, Domain V: Management and Communication, which includes assessing the validity of research findings for infection control decision-making.
NEW QUESTION # 53
An infection preventionist is providing education to a group of medical device reprocessing staff on critical steps in cleaning instruments. Which of the following actions is recommended while using washer-disinfector?
Answer: C
Explanation:
Best practices for using a washer-disinfector include disassembling instruments and opening hinged instruments to ensure proper cleaning and decontamination.
The APIC Text explains:
"Open hinged instruments and disassemble all instruments... Confirm that spray will be able to reach all loaded items without impedance." This ensures water and detergents reach all surfaces. Avoid stacking instruments and ensure proper placement to allow full cleaning.
References:
APIC Text, 4th Edition, Chapter 108 - Sterile Processing
NEW QUESTION # 54
What rate is expressed by the number of patients who acquire infections over a specified time period divided by the population at risk of acquiring an infection during that time period?
Answer: D
Explanation:
Theincidence ratemeasuresnew cases of infection in a population over a defined time periodusing the formula: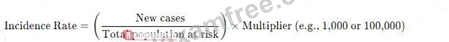
Why the Other Options Are Incorrect?
* B. Disease specific- Refers to infectionscaused by a particular pathogen, not the general rate of new infections.
* C. Point prevalence- Measuresexisting cases at a specific point in time, not new cases.
* D. Period prevalence- Includesboth old and new cases over a set period, unlike incidence, which only considers new cases.
CBIC Infection Control Reference
APIC definesincidence rate as the number of new infections in a population over a given period.
NEW QUESTION # 55
An 84-year-old male with a gangrenous foot is admitted to the hospital from an extended-care facility (ECF).
The ECF is notified that the wound grew Enterococcus faecium with the following antibiotic sensitivity results:
ampicillin - R
vancomycin - R
penicillin - R
linezolid - S
This is the fourth Enterococcus species cultured from residents within the same ECF wing in the past month.
The other cultures were from two urine specimens and a draining wound. The Infection Preventionist (IP) should immediately:
Answer: C
Explanation:
The scenario describes a potential outbreak of multidrug-resistant Enterococcus faecium in an extended-care facility (ECF) wing, indicated by four positive cultures (including the current case and three prior cases from urine and a draining wound) within a month. The organism exhibits resistance to ampicillin, vancomycin, and penicillin, but sensitivity to linezolid, suggesting a possible vancomycin-resistant Enterococcus (VRE) strain, which is a significant concern in healthcare settings. The Certification Board of Infection Control and Epidemiology (CBIC) emphasizes the importance of rapid outbreak detection and response in the
"Surveillance and Epidemiologic Investigation" domain, aligning with Centers for Disease Control and Prevention (CDC) guidelines for managing multidrug-resistant organisms (MDROs).
Option A, "Notify the medical director of the outbreak," is the most immediate and critical action. Identifying an outbreak-defined by the CDC as two or more cases of a similar illness linked by time and place-requires prompt notification to the facility's leadership (e.g., medical director) to initiate a coordinated response. The presence of four Enterococcus cases, including a multidrug-resistant strain, within a single ECF wing over a month suggests a potential cluster, necessitating urgent action to assess the scope, implement control measures, and allocate resources. The CDC's "Management of Multidrug-Resistant Organisms in Healthcare Settings" (2006) recommends immediate reporting to facility leadership as the first step to activate an outbreak investigation team, making this the priority.
Option B, "Compare the four culture reports and sensitivity patterns," is an important subsequent step in outbreak investigation. Analyzing the antibiotic susceptibility profiles and culture sources can confirm whether the cases are epidemiologically linked (e.g., clonal spread of VRE) and guide treatment and control strategies. However, this is a detailed analysis that follows initial notification and should not delay alerting the medical director. Option C, "Conduct surveillance cultures for this organism in all residents," is a proactive measure to determine the prevalence of Enterococcus faecium, especially VRE, within the wing. The CDC recommends targeted surveillance during outbreaks, but this requires prior authorization and planning by the outbreak team, making it a secondary action after notification. Option D, "Notify the nursing administrator to close the wing to new admissions," may be a control measure to prevent further spread, as suggested by the CDC for MDRO outbreaks. However, closing a unit is a significant decision that should be guided by the medical director and infection control team after assessing the situation, not an immediate independent action by the IP.
The CBIC Practice Analysis (2022) and CDC guidelines prioritize rapid communication with leadership to initiate a structured outbreak response, including resource allocation and policy adjustments. Given the multidrug-resistant nature and cluster pattern, notifying the medical director (Option A) is the most immediate and appropriate action to ensure a comprehensive response.
References:
* CBIC Practice Analysis, 2022.
* CDC Management of Multidrug-Resistant Organisms in Healthcare Settings, 2006.
NEW QUESTION # 56
......
Just download CBIC CIC Exam Questions and start CIC exam preparation right now. The CBIC CIC PDF Dumps exam syllabus is updated from time to time. If you want to pass the CBIC Certified Infection Control Exam exam then you have to understand these changes.
CIC Braindumps Torrent: https://www.realexamfree.com/CIC-real-exam-dumps.html
2026 Latest RealExamFree CIC PDF Dumps and CIC Exam Engine Free Share: https://drive.google.com/open?id=1Vyg--mLIO-y9bxptiRCKFWwJYD4jxjhi