P.S. Free 2026 NCC EFM dumps are available on Google Drive shared by Pass4SureQuiz: https://drive.google.com/open?id=1IAYvpFIdfITcbIRTb3G3wrvqfJou-PdQ
NCC EFM learning materials are new but increasingly popular choices these days which incorporate the newest information and the most professional knowledge of the practice exam. All points of questions required are compiled into our Certified - Electronic Fetal Monitoring EFM Preparation quiz by experts. By the way, the EFMcertificate is of great importance for your future and education.
| Section | Objectives |
|---|---|
| Fetal Physiology and Oxygenation | - Fetal cardiovascular physiology - Oxygen transport and acid-base balance |
| Intrapartum Assessment and Monitoring | - External and internal monitoring techniques - Risk assessment during labor |
| Uterine Activity | - Tachysystole and abnormal contraction patterns - Normal uterine contraction patterns |
| Maternal and Fetal Complications | - High-risk obstetric conditions affecting fetal monitoring - Hypoxia and uteroplacental insufficiency |
| Fetal Heart Rate Interpretation | - Category I, II, and III tracing interpretation - Accelerations and decelerations - Baseline rate and variability |
| Intrauterine Resuscitation and Interventions | - Maternal position changes and oxygen administration - Fluid management and medication adjustments |
There is a succession of anecdotes, and there are specialized courses. Experts call them experts, and they must have their advantages. They are professionals in every particular field. The EFM test material, in order to enhance the scientific nature of the learning platform, specifically hired a large number of qualification exam experts, composed of product high IQ team, these experts by combining his many years teaching experience of EFM Quiz guide and research achievements in the field of the test, to exam the popularization was very complicated content of Certified - Electronic Fetal Monitoring exam dumps, better meet the needs of users of various kinds of cultural level.
NEW QUESTION # 92
A 45-year-old woman at 36-weeks gestation presents for a nonstress test. Vital signs are: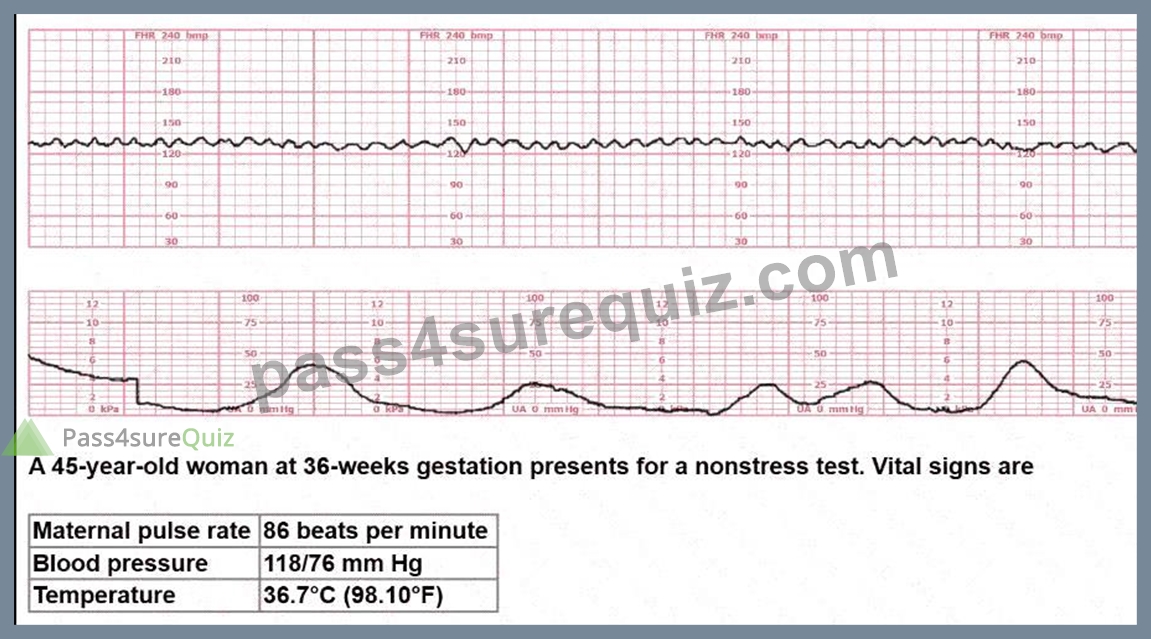
* Maternal pulse rate: 86 beats per minute
* Blood pressure: 118/76 mm Hg
* Temperature: 36.7°C (98.1°F)
The next course of action would include:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
The NST strip shows:
* Baseline FHR about 140 bpm
* Moderate variability
* Two or more accelerations meeting 15×15 criteria
* No decelerations
* Normal, infrequent contractions
Per NCC and AWHONN, a reactive NST is defined as:
* #2 accelerations of 15 bpm × 15 seconds in a 20-minute period
* With baseline 110-160 and moderate variability
* No recurrent decelerations
A reactive NST at 36 weeks in a hemodynamically stable mother with normal vitals is reassuring, and the appropriate disposition is routine follow-up and discharge.
Why the other options are incorrect:
* B. Induce labor - Not indicated solely on maternal age or a reactive NST.
* C. Kleihauer-Betke test - Used to quantify fetomaternal hemorrhage after trauma or sensitization risk; there is no such history here.
Therefore, the correct action is A. Discharge home.
References:NCC C-EFM Candidate Guide; AWHONN Fetal Heart Monitoring Principles & Practices; Simpson & Creehan; Creasy & Resnik.
NEW QUESTION # 93
A nonstress test is nonreactive in a 36-week gestational age fetus. Vibroacoustic stimulation (VAS) is applied with no fetal response. The next step is to proceed to:
Answer: A
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
A nonreactive NST with no response to vibroacoustic stimulation indicates:
* Possible fetal sleep cycle
* Possible CNS depression
* Possible hypoxemia
NCC, AWHONN, and MFM guidelines state the next step is a biophysical profile because:
* It evaluates fetal tone, movement, breathing, amniotic fluid, and NST
* Provides a complete assessment of fetal well-being
* Is less invasive and more informative than immediate delivery decisions Why the wrong answers are incorrect:
* B. Cesarean birth - not indicated without confirming fetal compromise.
* C. Induction of labor - not indicated until BPP clarifies fetal status.
Correct answer: A. Biophysical profile.
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; Creasy & Resnik; Simpson & Creehan.
NEW QUESTION # 94
During the second stage of labor, a period of bradycardia develops. The fetal heart rate baseline variability is moderate. The most likely cause of this bradycardia is:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
Second-stage bradycardia with moderate variability most commonly occurs from:
* Vagal stimulation caused by head compression, particularly during descent and pushing.
Moderate variability indicates:
* Neurologically intact fetus
* Sufficient oxygen reserve
* Temporary nature of bradycardia
This aligns with physiologic vagal slowing rather than hypoxic mechanisms.
Why the incorrect answers are wrong:
* A. Cord compression # typically produces variable decelerations, not sustained bradycardia with preserved variability.
* C. Vasospasm # associated with late decelerations and decreased variability (uteroplacental insufficiency).
Correct answer: B. Vagal stimulation
References:NCC Physiology Domain; AWHONN FHMPP; Menihan; Simpson & Creehan.
NEW QUESTION # 95
The tracing shown is a: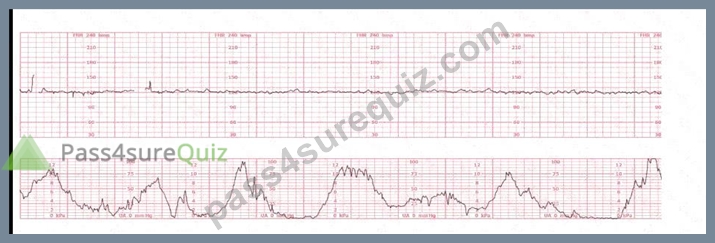
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References (No URLs):
Interpretation of fetal heart rate (FHR) tracings in the NCC C-EFM exam follows the standardized NICHD three-tier classification, which is fully adopted in NCC's content outline and recommended references such as AWHONN Fetal Heart Monitoring Principles & Practices, Miller's EFM Pocket Guide, Menihan, Simpson' s Perinatal Nursing, and Creasy & Resnik.
Baseline:
The tracing demonstrates an FHR baseline around 145-150 bpm, which falls within the normal range of 110-
160 bpm. NCC references define baseline as the mean FHR rounded to increments of 5 bpm over a 10-minute window.
Variability:
The strip shows minimal variability, with amplitude fluctuations approximately 0-2 bpm.
According to NCC-aligned definitions:
* Moderate variability: 6-25 bpm
* Minimal variability: 1-5 bpm
* Absent variability: undetectable amplitude
This tracing shows minimal variability, not moderate, so it cannot be Category I.
Accelerations:
No accelerations are present. Lack of accelerations alone does not classify the tracing as Category III.
Decelerations:
There are no recurrent late decelerations, no recurrent variable decelerations, and no prolonged decelerations. Without these, and with minimal variability, the tracing does not meet Category III criteria.
Category III criteria (per NICHD/NCC):
Must include at least one of the following:
* Absent variability with recurrent late decelerations
* Absent variability with recurrent variable decelerations
* Absent variability with bradycardia
* Sinusoidal pattern
None of these are present.
Category II criteria (per NICHD/NCC):
Category II includes tracings that are not Category I or III.
Examples specifically listed include:
* Minimal variability
* Absent accelerations after fetal stimulation
* Tachycardia
* Bradycardia without absent variability
* Variable or late decelerations occurring intermittently
Because this tracing shows minimal variability, a normal baseline, no accelerations, and no recurrent decelerations, it fits squarely into Category II.
Therefore, the correct classification is Category II.
References:NCC C-EFM Candidate Guide and Content Outline (2025); AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine; NICHD Three-Tier FHR Interpretation System.
NEW QUESTION # 96
A woman at 39-weeks gestation is in early labor, 2-3 cm dilated, 85% effaced, and -2 station. Based on the fetal heart rate tracing shown, what is the most appropriate first intervention?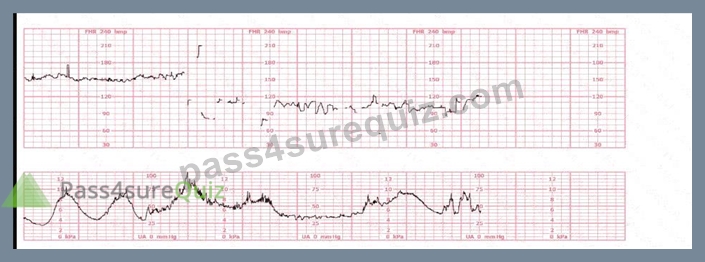
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The tracing shows significant artifact, periods of signal loss, and abrupt changes inconsistent with physiologic fetal patterns. This is typical of poor signal quality, not actual fetal decelerations. In early labor at -2 station, external FHR monitoring often loses contact due to fetal position and maternal movement.
NCC and AWHONN emphasize the following when artifact is present:
* Correct signal quality before interpreting the tracing.
* Troubleshooting steps include:- Adjusting transducer location- Ensuring adequate ultrasound gel- Repositioning the mother- Checking for maternal heart rate contamination Why the other options are incorrect:
* B. IV fluid bolus - Indicated for hypotension or late decelerations, not for artifact.
* C. Terbutaline - Used for tachysystole with fetal intolerance; there is no tachysystole shown.
Thus, the correct first step is A. Adjust the fetal monitor.
References:NCC C-EFM Candidate Guide; AWHONN Fetal Heart Monitoring Principles & Practices; Miller' s Pocket Guide; Menihan; Simpson & Creehan.
NEW QUESTION # 97
......
Are you planning to pass the EFM exam and don’t know where to start preparation? Many candidates don’t find a credible and lose money and time. If you want to save your resources, you are at right place because NCC EFM offers real exam questions for the students so that they can prepare and pass NCC EFM.
Exam EFM Reference: https://www.pass4surequiz.com/EFM-exam-quiz.html
2026 Latest Pass4SureQuiz EFM PDF Dumps and EFM Exam Engine Free Share: https://drive.google.com/open?id=1IAYvpFIdfITcbIRTb3G3wrvqfJou-PdQ