BTW, DOWNLOAD part of Exam4Tests EFM dumps from Cloud Storage: https://drive.google.com/open?id=12rVMGRQVZzrlflgHlFxQ3gHN0NgxeSG5
According to the survey from our company, the experts and professors from our company have designed and compiled the best EFM cram guide in the global market. We can assure to all people that our EFM study materials will have a higher quality and it can help all people to remain an optimistic mind when they are preparing for the EFM Exam. On the contrary, people who want to pass the exam will persist in studying all the time. We deeply believe that the latest EFM study questions from our company will is most suitable and helpful for all people.
| Section | Objectives |
|---|---|
| Uterine Activity | - Normal uterine contraction patterns - Tachysystole and abnormal contraction patterns |
| Fetal Physiology and Oxygenation | - Oxygen transport and acid-base balance - Fetal cardiovascular physiology |
| Intrapartum Assessment and Monitoring | - External and internal monitoring techniques - Risk assessment during labor |
| Fetal Heart Rate Interpretation | - Baseline rate and variability - Accelerations and decelerations - Category I, II, and III tracing interpretation |
| Intrauterine Resuscitation and Interventions | - Fluid management and medication adjustments - Maternal position changes and oxygen administration |
| Maternal and Fetal Complications | - High-risk obstetric conditions affecting fetal monitoring - Hypoxia and uteroplacental insufficiency |
>> Intereactive EFM Testing Engine <<
Our company is a professional certificate exam materials provider, and we have occupied in this field for years. EFM exam dumps are high-quality, and we have received many good feedbacks from our customers. In addition, we offer you free demo for you to have a try before buying EFM Exam Braindumps, and you will have a better understanding of what you are going to buy. We have online and offline chat service stuffs, who are quite familiar with the EFM exam dumps, if you have any questions, just contact us.
NEW QUESTION # 49
The tracing shown is a: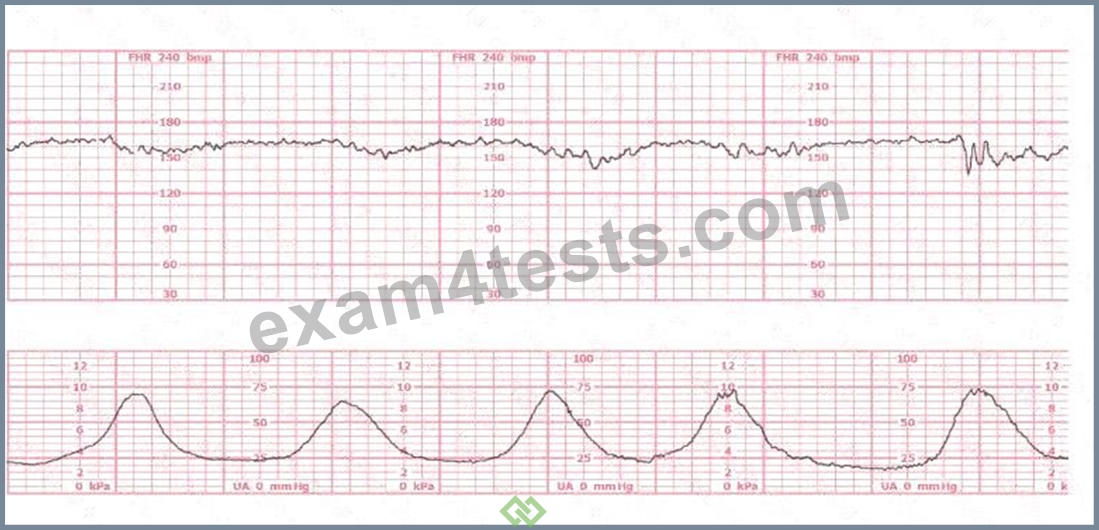
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The tracing demonstrates:
* Baseline: approx. 140 bpm
* Variability: minimal-to-moderate (fluctuating but not consistently moderate)
* Decelerations: shallow variable decelerations
* Accelerations: not consistently present
According to NICHD/NCC definitions:
Category I requires ALL of the following:
* Baseline 110-160
* Moderate variability
* No late or variable decelerations
* Early decels and accelerations may be present
This tracing does not have consistently moderate variability and does have variable decelerations, so it is not Category I.
Category III requires ANY of the following:
* Absent variability with recurrent late decels
* Absent variability with recurrent variable decels
* Absent variability with bradycardia
* Sinusoidal pattern
This tracing does not show absent variability, bradycardia, or recurrent significant lates.
Category II includes:
* Minimal variability
* Absence of accelerations
* Variable decelerations
* Tracings not clearly Category I or III
This strip fits Category II exactly due to minimal variability + intermittent variable decelerations.
Thus, the correct classification is Category II.
References:NCC C-EFM Candidate Guide; NICHD Three-Tier Interpretation System; AWHONN Fetal Heart Monitoring Principles & Practices; Menihan; Miller; Simpson & Creehan.
NEW QUESTION # 50
A patient presents at 38-weeks gestation with complaints of decreased fetal movement and ruptured membranes. The fetal heart rate is not able to be determined with an external ultrasound monitor. A spiral electrode is placed, and the tracing shows a rate of 90 bpm. What is the next most appropriate action?
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
Whenever a fetal heart rate is unexpectedly low (such as 90 bpm), the FIRST step per NCC and AWHONN is to confirm that the signal is fetal, not maternal.
Even internal spiral electrodes can capture maternal heart rate, especially after:
* Rupture of membranes
* Maternal hypotension
* Maternal dehydration
* Maternal tachycardia or bradycardia
Thus, the first, most immediate action is:
# Palpate the maternal radial pulse to determine whether the tracing is maternal or fetal.
If rates match # the monitor is falsely detecting the maternal pulse.
If rates differ # confirm true fetal bradycardia and begin intrauterine resuscitation.
Why the other options are incorrect:
* A. Intrauterine resuscitation - should NOT begin before confirming the tracing is fetal.
* C. Bedside ultrasound - appropriate after confirming that the tracing is not maternal, not before.
Correct answer: B. Palpation of the maternal radial pulse.
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; Menihan; Miller's Pocket Guide; Simpson
& Creehan.
NEW QUESTION # 51
When a difference in interpretation occurs over a non-emergent electronic fetal heart rate tracing, the first step toward resolution is to:
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
NCC's Professional Issues domain emphasizes communication, collaboration, and team-based interpretation of electronic fetal monitoring tracings.
For non-emergent differences in interpretation, the first step is:
* Discussion and joint review of the tracing by the involved clinicians.
Only if disagreement persists should the chain of command be used. Documentation occurs after consensus or escalation-not as the first step.
Thus, the appropriate first step is C. Have the involved clinicians review the tracing together.
References:NCC C-EFM Candidate Guide; AWHONN Standards for Professional Fetal Monitoring Practice; TeamSTEPPS principles.
NEW QUESTION # 52
Nonstress testing is used more frequently for antepartum testing than contraction stress testing because contraction stress testing has a:
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
NCC and AWHONN explain that Contraction Stress Testing (CST):
* Has a higher rate of equivocal ("equivocal-suspicious" or "equivocal-hyperstimulation") results
* Frequently must be repeated or replaced with other tests
* Requires inducing contractions, which carries risk (hyperstimulation, preterm labor, uterine rupture in scarred uterus) NST is used more commonly because it is:
* Noninvasive
* Easier to perform
* Has fewer contraindications
* Has a lower rate of equivocal results
Why the others are incorrect:
* B - CST does detect fetal compromise reliably and is NOT limited in its reporting structure.
* C - A negative CST actually has very high negative predictive value for 7 days, making this answer incorrect.
Thus the correct choice is A. Higher frequency of equivocal results.
References:NCC C-EFM Candidate Guide; AWHONN; Menihan; Simpson & Creehan; Creasy & Resnik.
NEW QUESTION # 53
A woman at 39-weeks gestation is in early labor, 2-3 cm dilated, 85% effaced, and -2 station. Based on the fetal heart rate tracing shown, what is the most appropriate first intervention?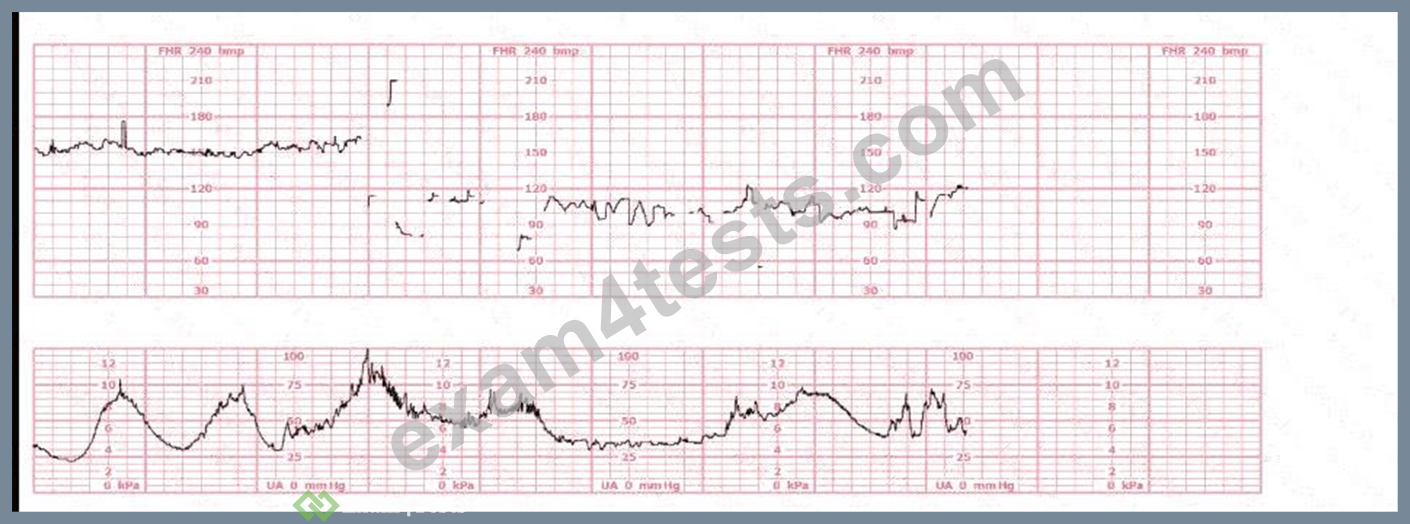
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The tracing shows significant artifact, periods of signal loss, and abrupt changes inconsistent with physiologic fetal patterns. This is typical of poor signal quality, not actual fetal decelerations. In early labor at -2 station, external FHR monitoring often loses contact due to fetal position and maternal movement.
NCC and AWHONN emphasize the following when artifact is present:
* Correct signal quality before interpreting the tracing.
* Troubleshooting steps include:- Adjusting transducer location- Ensuring adequate ultrasound gel- Repositioning the mother- Checking for maternal heart rate contamination Why the other options are incorrect:
* B. IV fluid bolus - Indicated for hypotension or late decelerations, not for artifact.
* C. Terbutaline - Used for tachysystole with fetal intolerance; there is no tachysystole shown.
Thus, the correct first step is A. Adjust the fetal monitor.
References:NCC C-EFM Candidate Guide; AWHONN Fetal Heart Monitoring Principles & Practices; Miller' s Pocket Guide; Menihan; Simpson & Creehan.
NEW QUESTION # 54
......
Some people worry that our aim is not to Certified - Electronic Fetal Monitoring guide torrent but to sell their privacy information to the third part to cause serious consequences. But we promise to you our privacy protection is very strict and we won’t sell the client’s privacy to others for our own benefits. Our aim to sell the EFM test torrent to the client is to help them pass the exam and not to seek illegal benefits. For that time is extremely important for the learners, everybody hope that they can get the efficient learning. So clients can use our EFM Test Torrent immediately is the great merit of our product. When you begin to use, you can enjoy the various functions and benefits of our product such as it can simulate the exam and boosts the timing function.
Exam EFM Forum: https://www.exam4tests.com/EFM-valid-braindumps.html
DOWNLOAD the newest Exam4Tests EFM PDF dumps from Cloud Storage for free: https://drive.google.com/open?id=12rVMGRQVZzrlflgHlFxQ3gHN0NgxeSG5