BTW, DOWNLOAD part of Itcertmaster EFM dumps from Cloud Storage: https://drive.google.com/open?id=1oS1lIFxDYGOxNMZi56859aWGwddSb-t1
The APP version of our EFM study guide provides you with mock exams, time-limited exams, and online error correction and let you can review on any electronic device. So that you can practice our EFM exam questions on Phone or IPAD, computer as so on. At the same time, for any version, we do not limit the number of downloads and the number of concurrent users, you can even buy EFM Learning Materials together with your friends, which undoubtedly saves you a lot of overhead.
| Section | Objectives |
|---|---|
| Topic 1: Fetal Heart Rate Interpretation | - Baseline rate and variability - Accelerations and decelerations - Category I, II, and III tracing interpretation |
| Topic 2: Uterine Activity | - Normal uterine contraction patterns - Tachysystole and abnormal contraction patterns |
| Topic 3: Fetal Physiology and Oxygenation | - Oxygen transport and acid-base balance - Fetal cardiovascular physiology |
| Topic 4: Intrapartum Assessment and Monitoring | - External and internal monitoring techniques - Risk assessment during labor |
| Topic 5: Intrauterine Resuscitation and Interventions | - Maternal position changes and oxygen administration - Fluid management and medication adjustments |
| Topic 6: Maternal and Fetal Complications | - Hypoxia and uteroplacental insufficiency - High-risk obstetric conditions affecting fetal monitoring |
Similarly, the Itcertmaster NCC EFM practice test creates an actual exam scenario on each and every step so that you may be well prepared before your actual Certified - Electronic Fetal Monitoring examination time. Hence, it saves you time and money. Itcertmaster provides three months of free updates if you purchase the NCC EFM Questions and the content of the examination changes after that.
NEW QUESTION # 12
The tracing shown is from a woman at 28-weeks gestation in the post-anesthesia care unit (PACU) after an appendectomy. She is alert and awake. Based on this fetal heart rate pattern, the most appropriate intervention is:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The fetal heart rate tracing shows:
* Baseline around 140 bpm
* Minimal variability
* No accelerations
* No decelerations
* Regular uterine activity but not tachysystole
This pattern is Category II, but in the context of:
* 28-week gestation
* Immediate postoperative status after anesthesia
* Maternal alertness and stability
NCC and AWHONN emphasize that maternal sedation, post-anesthesia effects, medications, and physiologic stress commonly cause temporary minimal variability without acidemia, especially at preterm gestations where baseline variability is normally lower.
Key NCC principle:
Minimal variability in a stable mother without decelerations does NOT require emergent delivery.
Instead, the fetus should be observed as anesthesia effects wear off.
Why other answers are incorrect:
* A. Terbutaline - No tachysystole and no recurrent decels are present.
* C. Cesarean birth - No bradycardia, no late decels, no absent variability, and no Category III criteria.
Thus, appropriate management is B. Continued monitoring.
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; Menihan EFM; Miller's Pocket Guide; NICHD Definitions; Creasy & Resnik.
NEW QUESTION # 13
(Full question statement)
A woman at 39-weeks gestation is in labor, progressing normally. The baseline fetal heart rate has increased from 125 to 150 beats per minute over the last hour with moderate variability. What is the next step?
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract Without Links:
NCC-recommended references (Simpson, AWHONN FHM, Creasy & Resnik) note that baseline increases within the normal range (110-160 bpm) accompanied by moderate variability are typically benign. Mild physiologic causes-maternal activity, fetal stimulation, or normal sympathetic activation-may transiently raise baseline FHR.
AWHONN stresses that intervention is required only when tachycardia exceeds 160 bpm or when variability is minimal/absent or accompanied by recurrent decelerations.
Here, the baseline increase to 150 bpm remains within normal limits and is paired with moderate variability, which the NCC recognizes as the strongest indicator of adequate fetal oxygenation.
Therefore, evaluation is complete, and continued observation is the appropriate course.
NEW QUESTION # 14
The main reason intrauterine pressure catheters are placed is to:
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
Intrauterine pressure catheters (IUPCs) are an internal uterine activity monitoring device used when external tocodynamometry does not provide adequate assessment of contraction strength or frequency.
According to NCC, AWHONN, Miller, and Menihan, the primary indication for placing an IUPC is to obtain accurate, quantitative measurement of uterine activity.
Purpose of IUPC (per NCC and AWHONN):
* Measures exact intrauterine pressure in mmHg
* Calculates Montevideo units (MVUs) to evaluate adequacy of labor
* Clearly differentiates:
* Frequency
* Duration
* Strength (intensity)
* Resting tone
NCC explicitly lists the primary purpose as:
"Accurate assessment of uterine contraction pattern and intensity."
Why the other options are incorrect:
A). Define the quality of the fetal baseline - Incorrect
* Fetal heart rate (FHR) baseline quality is determined by fetal ECG or FSE, not IUPC.
* IUPCs monitor the uterus, not the fetal cardiac signal.
C). Rule out artifact - Incorrect
* While an IUPC can reduce artifact from the toco, this is not its primary purpose.
* Artifact is more commonly an issue with external FHR monitoring, corrected by repositioning or placing a fetal scalp electrode-not by using an IUPC.
B). Determine the contraction pattern
This aligns directly with NCC's Electronic Monitoring Equipment domain: IUPCs provide the most accurate and reliable measurement of uterine activity when external monitoring is inadequate.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 15
Sustained fetal supraventricular tachycardia that goes untreated is most likely to result in:
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
Sustained fetal supraventricular tachycardia (SVT) often produces heart rates > 200-240 bpm, causing:
* Poor ventricular filling
* Decreased stroke volume
* Reduced cardiac output
* Congestive heart failure
* Progressive fluid accumulation
NCC and AWHONN emphasize that untreated SVT leads to hydrops fetalis, characterized by:
* Ascites
* Pleural effusion
* Pericardial effusion
* Skin edema
Why the other answers are incorrect:
* A. Fetal anemia - Causes tachycardia but is not caused by SVT.
* C. Neonatal pacemaker - Pacemakers treat heart block, not SVT.
Correct answer: B. Hydrops fetalis
References:NCC C-EFM Candidate Guide; AWHONN Principles & Practices; Simpson & Creehan; Creasy
& Resnik Maternal-Fetal Medicine.
NEW QUESTION # 16
A woman at 38-weeks gestation is admitted to labor and delivery following a fall down the stairs three hours ago. She started feeling contractions in the ambulance. The fetal heart rate tracing shown is on initial evaluation and represents 25 minutes. This tracing is most consistent with a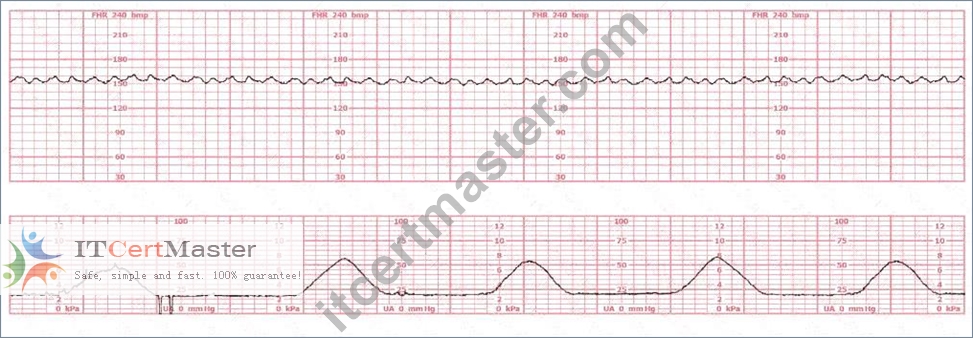
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract without any URL or Links According to the NCC C-EFM 2025 Candidate Guide, Pattern Recognition and Intervention requires the candidate to classify fetal heart rate (FHR) patterns using the NICHD 2008 three-tier system, which NCC endorses across all recommended resources (AWHONN Fetal Heart Monitoring Principles and Practices, Menihan Electronic Fetal Monitoring, Simpson & Creasy, Miller's Pocket Guide).
A Category II tracing is defined as "indeterminate" and includes any FHR pattern that is not Category I and not Category III. NCC references indicate that Category II may include:
* Minimal or marked variability
* Absence of accelerations after fetal stimulation
* Recurrent variable decelerations with moderate variability
* Prolonged decelerations lasting 2-10 minutes
* Baseline tachycardia or bradycardia without absent variability
In the tracing provided:
* The baseline FHR is approximately 135-145 bpm, within normal limits.
* Moderate variability is not consistently present; variability is borderline minimal-moderate at times.
* No significant accelerations are seen over the 25-minute evaluation period.
* No recurrent late or prolonged decelerations are present.
* There are occasional subtle variable-type dips, but not enough to meet criteria for Category III.
NCC-endorsed texts (such as AWHONN and Menihan) state that a tracing with minimal variability for less than 40 minutes and without recurrent decelerations is Category II, as it fails to meet the requirements for Category I (must have moderate variability and accelerations absent decelerations) and lacks the criteria for Category III (must have absent variability with recurrent late decels, recurrent variable decels, bradycardia, or sinusoidal pattern).
Therefore, this pattern is indeterminate, consistent with Category II, and requires continued surveillance and evaluation, which aligns with NCC-recommended clinical decision-making competencies.
NEW QUESTION # 17
......
Are you worried about insufficient time to prepare the exam? Do you have a scientific learning plan? Maybe you have set a series of to-do list, but it’s hard to put into practice for there are always unexpected changes during the EFM exam. Here we recommend our EFM test prep to you. With innovative science and technology, our study materials have grown into a powerful and favorable product that brings great benefits to all customers. Under the support of our EFM Study Materials, passing the EFM exam won’t be an unreachable mission.
EFM Exam Question: https://www.itcertmaster.com/EFM.html
What's more, part of that Itcertmaster EFM dumps now are free: https://drive.google.com/open?id=1oS1lIFxDYGOxNMZi56859aWGwddSb-t1