What's more, part of that 2Pass4sure EFM dumps now are free: https://drive.google.com/open?id=1rLrWf-psdPRU9pSl1Ho_P084SgUNw68Y
2Pass4sure enjoys the reputation of a reliable study material provider to those professionals who are keen to meet the challenges of industry and work hard to secure their positions in it. If you are preparing for a EFM Certification test, the EFM exam dumps from 2Pass4sure can prove immensely helpful for you in passing your desired EFM exam.
| Section | Objectives |
|---|---|
| Topic 1: Intrauterine Resuscitation and Interventions | - Maternal position changes and oxygen administration - Fluid management and medication adjustments |
| Topic 2: Uterine Activity | - Tachysystole and abnormal contraction patterns - Normal uterine contraction patterns |
| Topic 3: Fetal Physiology and Oxygenation | - Fetal cardiovascular physiology - Oxygen transport and acid-base balance |
| Topic 4: Maternal and Fetal Complications | - Hypoxia and uteroplacental insufficiency - High-risk obstetric conditions affecting fetal monitoring |
| Topic 5: Fetal Heart Rate Interpretation | - Accelerations and decelerations - Baseline rate and variability - Category I, II, and III tracing interpretation |
| Topic 6: Intrapartum Assessment and Monitoring | - Risk assessment during labor - External and internal monitoring techniques |
Life is beset with all different obstacles that are not easily overcome. For instance, EFM exams may be insurmountable barriers for the majority of population. However, with the help of our EFMexam questions, exams are no longer problems for you. The reason why our EFM Training Materials outweigh other EFM study prep can be attributed to three aspects, namely free renewal in one year, immediate download after payment and simulation for the software version.
NEW QUESTION # 72
The tracing shown is a: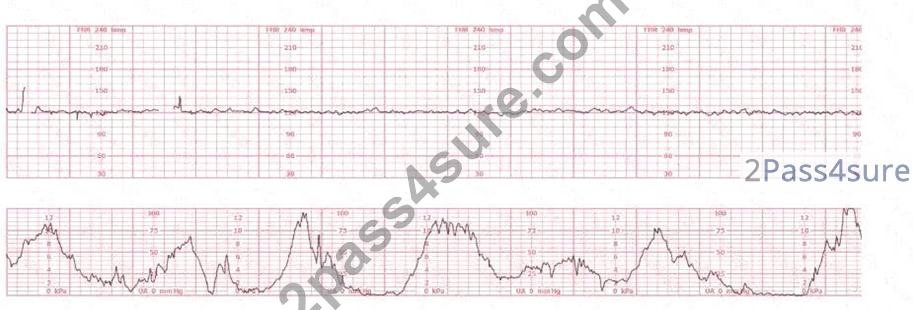
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References (No URLs):
Interpretation of fetal heart rate (FHR) tracings in the NCC C-EFM exam follows the standardized NICHD three-tier classification, which is fully adopted in NCC's content outline and recommended references such as AWHONN Fetal Heart Monitoring Principles & Practices, Miller's EFM Pocket Guide, Menihan, Simpson' s Perinatal Nursing, and Creasy & Resnik.
Baseline:
The tracing demonstrates an FHR baseline around 145-150 bpm, which falls within the normal range of 110-
160 bpm. NCC references define baseline as the mean FHR rounded to increments of 5 bpm over a 10-minute window.
Variability:
The strip shows minimal variability, with amplitude fluctuations approximately 0-2 bpm.
According to NCC-aligned definitions:
* Moderate variability: 6-25 bpm
* Minimal variability: 1-5 bpm
* Absent variability: undetectable amplitude
This tracing shows minimal variability, not moderate, so it cannot be Category I.
Accelerations:
No accelerations are present. Lack of accelerations alone does not classify the tracing as Category III.
Decelerations:
There are no recurrent late decelerations, no recurrent variable decelerations, and no prolonged decelerations. Without these, and with minimal variability, the tracing does not meet Category III criteria.
Category III criteria (per NICHD/NCC):
Must include at least one of the following:
* Absent variability with recurrent late decelerations
* Absent variability with recurrent variable decelerations
* Absent variability with bradycardia
* Sinusoidal pattern
None of these are present.
Category II criteria (per NICHD/NCC):
Category II includes tracings that are not Category I or III.
Examples specifically listed include:
* Minimal variability
* Absent accelerations after fetal stimulation
* Tachycardia
* Bradycardia without absent variability
* Variable or late decelerations occurring intermittently
Because this tracing shows minimal variability, a normal baseline, no accelerations, and no recurrent decelerations, it fits squarely into Category II.
Therefore, the correct classification is Category II.
References:NCC C-EFM Candidate Guide and Content Outline (2025); AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine; NICHD Three-Tier FHR Interpretation System.
NEW QUESTION # 73
Fetal cardiac output is essentially dependent on the fetal:
Answer: A
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
Because the fetal myocardium is immature, it has:
* Limited ability to increase stroke volume
* Limited ability to increase contractility
Therefore, fetal cardiac output (CO) is almost entirely dependent on heart rate.
NCC and AWHONN physiology describe:
* CO = stroke volume × heart rate
* In the fetus, stroke volume is relatively fixed
* Therefore, changes in HR directly affect cardiac output
* Tachycardia # increases CO
* Bradycardia # decreases CO # decreased perfusion and oxygen delivery
Why the other options are incorrect:
* A. Activity does not fundamentally determine CO.
* B. Baroreceptors regulate HR reflexively but are not the primary determinant of cardiac output.
Correct answer: C. Heart rate
References:NCC Physiology Domain; AWHONN FHMPP; Menihan; Simpson & Creehan; Creasy & Resnik.
NEW QUESTION # 74
(Full question statement)
The American College of Obstetricians and Gynecologists (ACOG) recommends continuous electronic fetal monitoring in pregnancies when there is:
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract Without Links:
NCC relies heavily on ACOG Practice Bulletins for risk-based monitoring decisions. ACOG identifies maternal diabetes (pregestational or poorly controlled gestational diabetes) as a key high-risk obstetric condition warranting continuous electronic fetal monitoring due to risks such as fetal hypoxia, macrosomia, and metabolic complications.
In contrast, a history of preterm birth does not necessarily require continuous monitoring unless current pregnancy complications are present.
Macrosomia alone does not automatically justify continuous EFM unless accompanied by other risk factors.
Therefore, according to NCC-aligned ACOG clinical criteria, maternal diabetes is the correct indication.
NEW QUESTION # 75
The pattern on the fetal heart rate tracing shown is likely due to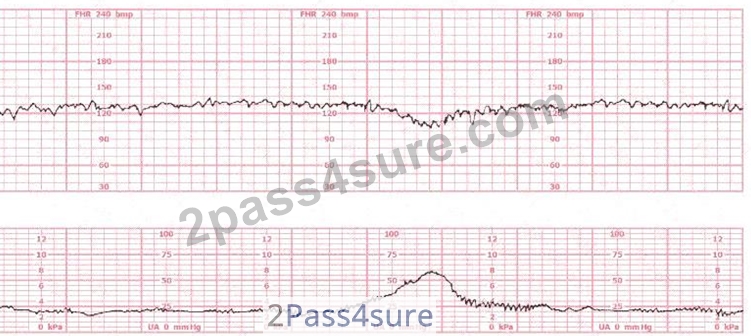
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract Sources:
The tracing demonstrates an abrupt-onset, sharp, V-shaped deceleration, occurring simultaneously with or slightly after a contraction-classic for variable decelerations, which are caused by umbilical cord compression.
According to AWHONN Fetal Heart Monitoring Principles & Practices, variable decelerations are defined by:
* "Abrupt decreases in FHR below baseline of at least 15 bpm, lasting at least 15 seconds and less than 2 minutes."
* "Most commonly associated with umbilical cord compression, whether transient or recurrent." Physiology reference (Simpson & Miller, Pocket Guide):
* Compression of the umbilical vein causes a brief acceleration.
* Compression of the umbilical arteries triggers a vagal response, producing a rapid deceleration.
* This creates the characteristic sharp 'V', 'U', or 'W' shape on the monitor.
Placental insufficiency (Choice B) produces late decelerations, which are gradual, not abrupt.
Fetal head compression (Choice A) produces early decelerations, which mirror contractions and have a gradual pattern.
Thus, the tracing is most consistent with variable decelerations caused by umbilical cord compression.
References:AWHONN Fetal Heart Monitoring Principles & Practices;Simpson - Fetal Monitoring;Menihan
- Electronic Fetal Monitoring;Miller's EFM Pocket Guide;NCC C-EFM Content Outline - Pattern Recognition Domain.
NEW QUESTION # 76
(Full question statement)
This tracing is consistent with: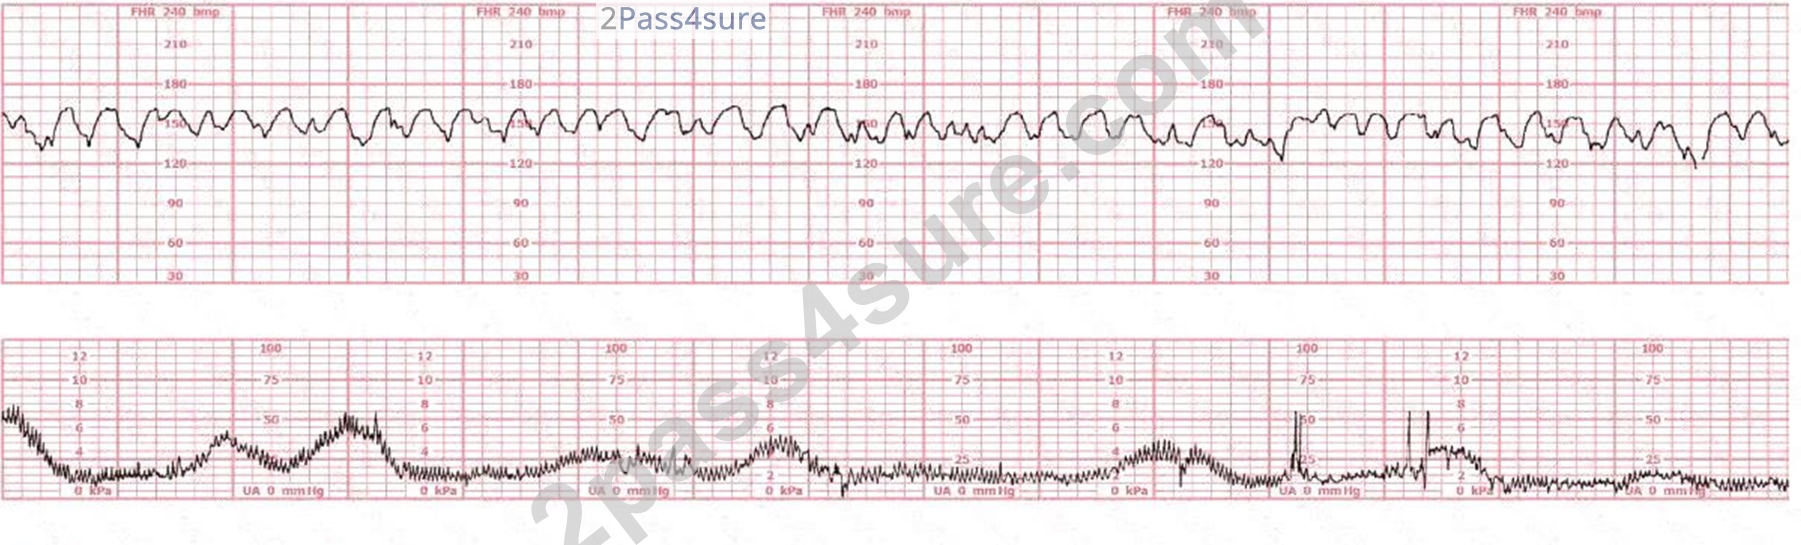
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract Without Links:
NCC and AWHONN teaching materials describe that butorphanol, an opioid analgesic, characteristically produces a transient sinusoidal-like pattern or pseudo-sinusoidal pattern with moderate variability preserved.
This drug-related pattern has:
* smooth, regular oscillations
* maintained variability
* absence of true periodic decelerations
* resolution within 20-60 minutes
Simpson & Menihan describe butorphanol as producing a "saw-tooth, wavering pattern" often mistaken for dysrhythmia but actually benign.
True sinusoidal patterns (e.g., fetal-maternal hemorrhage) are fixed, smooth, non-variable patterns with absent variability, not matching the scenario.
Atrial flutter produces very rapid atrial contractions, which manifest as irregular baseline spikes-also not consistent.
Therefore, the described tracing aligns most closely with butorphanol effects.
NEW QUESTION # 77
......
You can try the NCC EFM exam dumps demo before purchasing. If you like our Certified - Electronic Fetal Monitoring (EFM) exam questions features, you can get the full version after payment. 2Pass4sure EFM Dumps give surety to confidently pass the Certified - Electronic Fetal Monitoring (EFM) exam on the first attempt.
Latest Test EFM Experience: https://www.2pass4sure.com/NCC-C-EFM/EFM-actual-exam-braindumps.html
BTW, DOWNLOAD part of 2Pass4sure EFM dumps from Cloud Storage: https://drive.google.com/open?id=1rLrWf-psdPRU9pSl1Ho_P084SgUNw68Y