CCDSスタディガイドのサポーターは、GoShiken世界中で数万を超えており、それらの品質を直接反映しています。 試験はあなたの肩に大きな負担をかけるかもしれないので、私たちACDISの練習資料は時間の経過とともにそれらの問題をあなたを和らげることができます。 定期的にCCDS試験シミュレーションに時間を費やしただけで、それを取得できる可能性が大幅に向上します。 ご参考までに、合格率は現在までに98%を超えています。 これまでの練習教材は3つのバージョンで構成されており、これら3つの基本タイプはすべて、好みや傾向に応じてサポーターに人気があります。 成功に向かって進む途中で、CCDS準備資料:Certified Clinical Documentation Specialistは常に素晴らしいサポートを提供します。
| Section | Weight | Objectives |
|---|---|---|
| Medical record documentation | 19.17% | - Health record elements used for diagnosis and procedure code assignment - Documentation requiring clarification - Provider role and diagnosis code assignment - Situations in which queries are not appropriate - Physician query formats - Addressing diagnoses without clinical support - Clinical indicators - Compliant and noncompliant queries - ACDIS/AHIMA Guidelines for Achieving a Compliant Query Practice - Translating clinical indicators into compliant queries - When a physician query is warranted - Types of physician queries |
| Healthcare regulations, reimbursement, and documentation requirements related to the IPPS | 12.5% | - Coding and billing practices vulnerable to denial - Medicare contractors and their impact on CDI - Case mix index (CMI) - Principal diagnosis and medical necessity - Documentation and medical necessity of setting - Major complication/comorbidity (MCC) - Inpatient admission criteria and CMS Two-Midnight Rule - Complication/comorbidity (CC) - IPPS and its updates and revisions - Documentation impact on IPPS reimbursement - Medical staff and clinical staff documentation responsibilities - Medicare Severity Diagnosis Related Groups (MS-DRGs) |
| Communication skills | 9.17% | - Roles and responsibilities of coders working with CDI departments - Educational presentations for healthcare departments and administration - Verbal versus written physician communication - Reconciling CDI working DRGs with final coded DRGs - Physician education forms and tools - Roles and responsibilities of CDI specialists - Effective and non-confrontational physician communication |
| Impact of reportable diagnoses on quality of care | 8.33% | - Coded data elements affecting Patient Safety Indicators - Mortality reviews and observed/expected ratios - Patient Safety Indicators - 30-day mortality measures - Hospital-Acquired Condition Reduction Program - Quality data from record abstraction and claims data - Hospital Value-Based Purchasing - Hospital Inpatient Quality Reporting Program - Hospital Readmissions Reduction Program - CDI impact on Hospital Value-Based Purchasing - Documentation and code assignment impact on mortality index - Healthcare-associated infections and complication codes |
| Healthcare facility CDI program analysis | 8.33% | - Basic computer and software application skills - PEPPER data - Publicly reported data - Severity of illness and risk of mortality - Physician performance measurement - Case mix index (CMI) - Tracking and trending physician, department, and hospital performance - Hospital Value-Based Purchasing measures - Hospital-specific financial data - Provider response rates - Patient Safety Indicators - High-frequency DRGs - CDI program forecasting - CDI specialist productivity metrics - CC/MCC capture |
| Official Guidelines for Coding and Reporting | 14.17% | - Hospital-acquired conditions - Principal diagnosis assignment - Official Guidelines for Coding and Reporting updates - Coding guidelines for principal diagnosis selection - Present on admission indicators - Secondary diagnosis assignment - AHA Coding Clinic - Discharge dispositions and transfers - Working DRG assignment for multiple diagnoses |
| Professionalism, ethics, and compliance | 9.17% | - CDI department goals beyond reimbursement - Leading queries - Potential DRG creep - DRG compliance initiatives - Compliance risks indicated by PEPPER - Medical record confidentiality |
| Anatomy and physiology, pathophysiology, pharmacology, and medical terminology | 19.17% | - Diseases and disorders of the hepatobiliary system - Injuries, poisonings, and toxic effects of drugs - Diseases and disorders of the skin, subcutaneous tissue, and breast - Myeloproliferative diseases and disorders and poorly differentiated neoplasms - Mental diseases and disorders - Diseases and disorders of the blood and blood-forming organs and immunological disorders - Diagnostic tests as clinical indicators - Diseases and disorders of the digestive system - Diseases and disorders of the respiratory system - Medications as clinical indicators - Diseases and disorders of the kidney and urinary tract - Alcohol/drug use and alcohol/drug-induced organic brain disorders - Diseases and disorders of the musculoskeletal system - HIV infections - Pharmaceuticals and disease processes - Infectious and parasitic diseases - Diseases and disorders of the circulatory system - Diseases and disorders of the nervous system - Clinical indicators and query opportunities by Major Diagnostic Category - Endocrine, nutritional, and metabolic diseases and disorders - Standard medical abbreviations |
CCDS認定の取得を支援するために、多くの専門家が数年間、ACDISすべての試験官向けのCCDS試験トレントを策定するために懸命に取り組んできました。GoShiken このようにして、当社のCCDS学習資料は、対象となるだけでなく、すべての知識ポイントを網羅しています。 CCDS練習教材には、CCDS練習教材の学習プロセスの欠陥を見つけるのに役立つ統計分析機能もあるため、弱いリンクのCertified Clinical Documentation Specialistトレーニングを強化できます。 このようにして、能力が向上したため、成功に自信を持つことができます。
質問 # 81
A physician documents acute kidney injury. The patient's creatinine is 0.8 mg/dL on admission, 0.9 mg/dL the following day, and 0.8 mg/dL at discharge. Urine output remains normal and no renal treatment is provided.
What is the BEST CDI action?
正解:C
解説:
A clinical validation query is appropriate because the documented diagnosis appears inconsistent with the available clinical evidence. The creatinine values remain essentially unchanged, urine output is normal, and there is no apparent treatment or monitoring consistent with acute renal dysfunction.
The CDI specialist cannot simply delete the diagnosis because providers are responsible for establishing diagnoses. Conversely, a diagnosis should not automatically be accepted when substantial clinical evidence raises a legitimate question about its validity.
A compliant query would present the documented AKI together with the pertinent renal findings and request clarification. The provider could confirm AKI and provide supporting clinical reasoning, revise the diagnosis, state that it was ruled out, or document another condition.
Assigning chronic kidney disease would be equally inappropriate because CKD requires evidence of chronic kidney abnormality and cannot be inferred from these laboratory values.
The August 2026 ACDIS/AHIMA query guidance supersedes prior versions and remains the foundational standard for clinical validation and documentation clarification.
Clinical validation protects data integrity because diagnoses influence reimbursement, quality reporting, severity measurement, utilization analysis, and downstream patient information.
CCDS Reference Topics: Clinical validation; AKI; unsupported diagnoses; provider clarification; compliance.
=========
質問 # 82
The table below shows physician performance: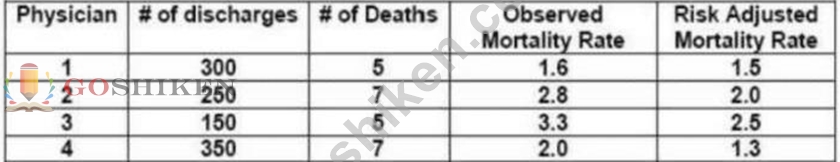
Which of the following physicians will have the most favorable mortality rate on a public website, such as Healthgrades.com?
正解:C
解説:
Physician 4 has the most favorable risk-adjusted mortality rate, at 1.3, compared with Physician 1 at 1.5, Physician 2 at 2.0, and Physician 3 at 2.5. Although Physician 1 has fewer observed deaths and an observed mortality rate of 1.6%, public outcome comparisons commonly incorporate risk adjustment rather than relying solely on raw mortality. Risk adjustment attempts to account for differences in patient complexity, comorbid disease burden, demographic factors, and other characteristics that influence expected outcomes.
This is directly relevant to CDI because incomplete documentation of clinically significant comorbidities can understate patient severity and therefore adversely affect the expected mortality component of risk-adjusted performance calculations. Conversely, accurate documentation allows coded data to represent the actual severity and risk of the population being treated. Healthgrades specifically states that its mortality methodology adjusts for patient risk factors to permit more meaningful comparisons of clinical outcomes.
The CCDS content outline specifically requires knowledge of mortality indices, severity of illness/risk of mortality, physician performance, and the effect of documentation on publicly reported data.
CCDS Reference Topics: Impact of reportable diagnoses on quality of care; Healthcare facility CDI program analysis; mortality index and risk adjustment.
=========
質問 # 83
Respiratory failure is documented in a patient's initial progress notes. There are no clinical indicators in the record to support this diagnosis. According to the AHIMA/ACDIS Practice Brief Guidelines for Achieving a Compliant Query Practice, the MOST appropriate action by the CDI specialist is which of the following?
正解:C
解説:
This scenario requires a clinical validation query. The diagnosis of respiratory failure is documented, but the remainder of the record lacks clinical evidence supporting it. CDI should not automatically accept the diagnosis solely because it appears in a progress note, nor should the specialist unilaterally remove or invalidate the provider's diagnosis.
The appropriate process is to present relevant patient-specific clinical information objectively and ask the responsible provider to clarify whether respiratory failure remains clinically appropriate. A compliant validation query should permit the provider to confirm the diagnosis, document another condition, indicate that it was ruled out, or provide another clinically appropriate response.
Looking only for CPAP documentation is inadequate because CPAP can be used for multiple conditions and its presence or absence does not independently determine whether respiratory failure exists. Similarly, simply refusing to code the diagnosis without seeking clarification bypasses the provider's clinical judgment and the organization's validation process.
The 2026 ACDIS/AHIMA query guidance is now the current foundational standard and supersedes earlier versions of the practice brief.
CCDS Reference Topics: Clinical validation; compliant querying; unsupported diagnoses; documentation integrity.
=========
質問 # 84
At discharge, the physician documents, "Possible gram-negative pneumonia." No later documentation rules out the condition. How should the diagnosis generally be handled for an inpatient admission?
正解:B
解説:
In the inpatient hospital setting, an uncertain diagnosis documented at discharge using terminology such as possible, probable, suspected, likely, questionable, compatible with, or consistent with may generally be coded as though the condition existed or was established.
Therefore, "possible gram-negative pneumonia" may be coded in accordance with the inpatient uncertain- diagnosis guideline when it remains the final diagnostic conclusion.
The rationale is that inpatient diagnostic evaluation and treatment frequently occur before absolute confirmation is available, and the patient may have been managed as though the suspected disease were present.
This rule is materially different from outpatient coding, where uncertain diagnoses are generally not coded as established and the documented signs, symptoms, or confirmed conditions are reported instead.
The presence of the uncertain terminology alone does not mandate a query. A query would be appropriate if documentation is contradictory, if the diagnosis is clinically unsupported, or if another documentation issue prevents correct code assignment.
CDI specialists need to recognize this inpatient-specific rule because unnecessary queries for "possible" or
"probable" diagnoses can create physician burden without improving coding accuracy.
CCDS Reference Topics: Uncertain inpatient diagnoses; discharge documentation; pneumonia; inpatient versus outpatient coding.
=========
質問 # 85
The PRIMARY goal of a CDI specialist's work is to support complete and specific documentation that results in:
正解:D
解説:
The fundamental objective of clinical documentation integrity is to ensure that the health record accurately represents the patient's clinical condition, including severity of illness, complexity, acuity, diagnoses, treatments, and outcomes. Reimbursement is an important downstream consequence of documentation and coding, but maximizing reimbursement is not the primary professional objective of CDI.
The ACDIS CCDS framework describes the CDI specialist as applying clinical knowledge to determine how documentation translates into coded data and educating providers so the record appropriately reflects severity, complexity, and acuity. This distinction is critical from an ethics and compliance perspective. A CDI program must pursue documentation accuracy whether clarification raises, lowers, or leaves reimbursement unchanged.
Reducing HACs is principally a clinical-quality and patient-safety function. CDI can improve the accuracy with which HACs are identified and reported, but it does not directly prevent those conditions. Similarly, improved provider communication is an important mechanism used by CDI professionals, but it is a means toward accurate documentation rather than the primary endpoint.
Therefore, A most accurately captures the broad clinical, coding, quality, and compliance purpose of CDI.
CCDS Reference Topics: Professionalism, ethics, and compliance; Medical record documentation; goals of CDI beyond reimbursement.
=========
質問 # 86
......
我々GoShikenのCCDS問題集はあなたの発展に大助けを提供することができます。CCDS試験に合格したら、あなたがより良く就職し輝かしい未来を持っています。この試験が非常に困難ですが、実は試験を準備するとき、もっと楽になることができます。我々のACDISのCCDS問題集を利用してから、あなたは短い時間でリラクスで試験に合格することができます。
CCDS模擬対策問題: https://www.goshiken.com/ACDIS/CCDS-mondaishu.html