2026 Latest ActualtestPDF EFM PDF Dumps and EFM Exam Engine Free Share: https://drive.google.com/open?id=1f-NoWUA_dB0ol6x1mBxNlJ5z5OkQ4YPy
The advent of our EFM exam questions with three versions has helped more than 98 percent of exam candidates get the certificate successfully. They are the PDF version, Software version and the APP online version which are co-related with the customers' requirements. All content of our EFM Exam Materials are written based on the real exam specially. And EFM simulating questions are carefully arranged with high efficiency and high quality. Besides, EFM guide preparations are afforded by our considerate after-sales services.
| Section | Weight | Objectives |
|---|---|---|
| Topic 1: Pattern Recognition and Intervention | 70% | - Fetal heart rate patterns classification - Clinical decision-making and interventions - Tracing evaluation and management - Interpretation per NICHD standards |
| Topic 2: Electronic Monitoring Equipment | 5% | - Calibration and accuracy - Proper application and use - Troubleshooting artifacts |
| Topic 3: Professional Issues | 5% | - Legal and ethical aspects - Safety and quality improvement - Documentation standards |
| Topic 4: Fetal Assessment and Methods | 9% | - Auxiliary assessment techniques - Correlation with clinical status - Indications for monitoring |
| Topic 5: Physiology | 11% | - Uteroplacental function - Factors affecting fetal oxygenation - Fetal cardiovascular physiology |
Our EFM test braindumps are in the leading position in the editorial market, and our advanced operating system for EFM latest exam torrent has won wide recognition. As long as you choose our EFM exam questions and pay successfully, you do not have to worry about receiving our learning materials for a long time. We assure you that you only need to wait 5-10 minutes and you will receive our EFM Exam Questions which are sent by our system. When you start learning, you will find a lot of small buttons, which are designed carefully. You can choose different ways of operation according to your learning habits to help you learn effectively.
NEW QUESTION # 73
A woman in active labor at 8 cm experiences spontaneous rupture of membranes and acute bright red vaginal bleeding. The uterus is soft and nontender to palpation. The fetal monitor tracing has been normal and now shows tachycardia followed by bradycardia with minimal variability. The maternal blood pressure is 130/76 mm Hg, and the pulse is 86 beats per minute. The most likely cause of these findings is:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
When bright red vaginal bleeding occurs at the moment of membrane rupture, accompanied by an acute, severe fetal heart rate deterioration, NCC sources emphasize considering conditions causing fetal hemorrhage rather than maternal instability.
The key features in this scenario:
* Timing:Bleeding occurs immediately with spontaneous rupture of membranes-this is classic for vasa previa rupture, where fetal vessels traverse membranes and are torn when the membranes rupture.
* Bleeding characteristics:Bleeding is acute, bright red, and sudden.In vasa previa, the blood observed vaginally is fetal blood, not maternal blood.
* Uterine exam:The uterus is soft and nontender, which strongly argues against abruptio placenta, where the uterus is typically firm, rigid, or painful.
* Maternal vital signs:Maternal blood pressure and pulse are normal, indicating no maternal hypovolemia.In placental abruption or placenta previa with significant maternal bleeding, maternal vitals are often abnormal.Here, the mother is stable, meaning the blood is not maternal-supporting fetal vessel rupture.
* Fetal heart rate pattern:
* Initial tachycardia, followed by
* Bradycardia with minimal variabilitySuch a pattern is consistent with acute fetal blood loss, which rapidly leads to fetal hypovolemia and hypoxia.
* Differential based on NCC-aligned physiology:
A). Abruptio placenta - NOT supported
Typically presents with:
* Painful bleeding
* Firm, tender uterus
* Maternal tachycardia
* Uterine irritabilityNone of these are present.
B). Placenta previa - NOT supported
Classically painless bright red bleeding before or early in labor, not triggered by membrane rupture.
Fetal compromise is less sudden unless maternal shock occurs, which is not the case here.
C). Ruptured vasa previa - CORRECT
Defined by:
* Painless, sudden bright red bleeding at ROM
* Normal maternal vital signs
* Rapid fetal deterioration (tachycardia # bradycardia # minimal variability)
* Soft, nontender uterusThis fits the scenario exactly.
Therefore, the most likely cause is ruptured vasa previa, a recognized obstetric emergency described across AWHONN, NCC C-EFM references, and maternal-fetal physiology texts such as Menihan and Creasy & Resnik.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 74
The pattern on the fetal heart rate tracing shown is likely due to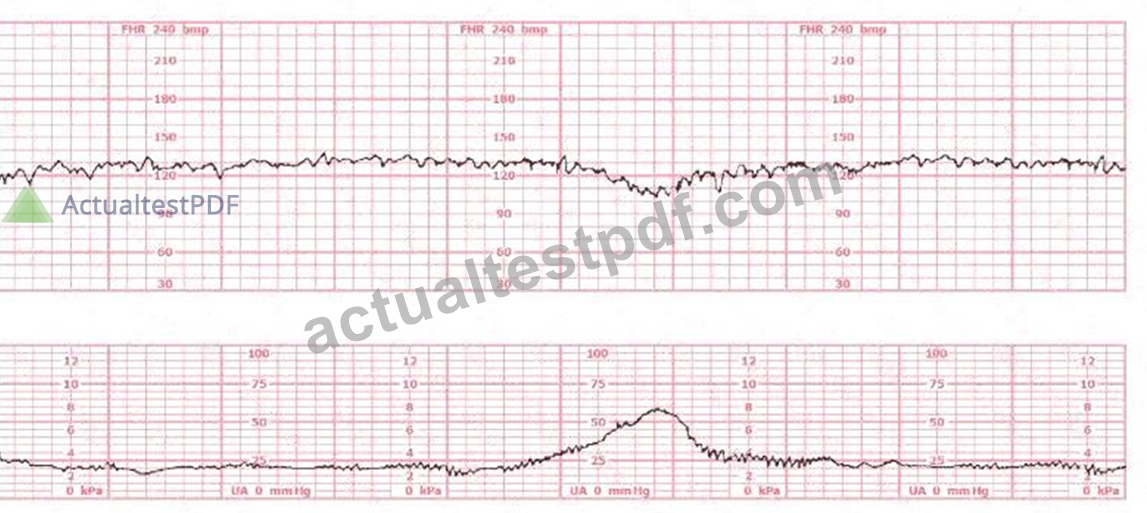
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract Sources:
The tracing demonstrates an abrupt-onset, sharp, V-shaped deceleration, occurring simultaneously with or slightly after a contraction-classic for variable decelerations, which are caused by umbilical cord compression.
According to AWHONN Fetal Heart Monitoring Principles & Practices, variable decelerations are defined by:
* "Abrupt decreases in FHR below baseline of at least 15 bpm, lasting at least 15 seconds and less than 2 minutes."
* "Most commonly associated with umbilical cord compression, whether transient or recurrent." Physiology reference (Simpson & Miller, Pocket Guide):
* Compression of the umbilical vein causes a brief acceleration.
* Compression of the umbilical arteries triggers a vagal response, producing a rapid deceleration.
* This creates the characteristic sharp 'V', 'U', or 'W' shape on the monitor.
Placental insufficiency (Choice B) produces late decelerations, which are gradual, not abrupt.
Fetal head compression (Choice A) produces early decelerations, which mirror contractions and have a gradual pattern.
Thus, the tracing is most consistent with variable decelerations caused by umbilical cord compression.
References:AWHONN Fetal Heart Monitoring Principles & Practices;Simpson - Fetal Monitoring;Menihan
- Electronic Fetal Monitoring;Miller's EFM Pocket Guide;NCC C-EFM Content Outline - Pattern Recognition Domain.
NEW QUESTION # 75
In the event of recurrent variable decelerations with thick meconium, amnioinfusion is recommended to:
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
Amnioinfusion is considered an intrauterine resuscitative intervention used specifically for recurrent variable decelerations caused by cord compression. NCC, AWHONN, Miller, and Menihan consistently teach that variables occur when the umbilical cord becomes compressed, reducing fetal oxygenation. When oligohydramnios or decreased amniotic fluid volume is present, the cord is more vulnerable to compression.
Why amnioinfusion is used:
Amnioinfusion works by:
Increasing intraamniotic fluid volume
Reducing umbilical cord compression
Decreasing the frequency and severity of variable decelerations
This directly targets the pathophysiology behind recurrent variables.
Why the other options are incorrect:
A). Dilute thick meconium - NOT supported by NCC
Historically, amnioinfusion was studied for meconium dilution, but major organizations-including NCC- aligned sources-state that amnioinfusion is NOT recommended for the sole purpose of diluting meconium. It does not reduce meconium aspiration syndrome and is no longer indicated for that purpose.
B). Restore uterine blood flow - NOT accurate
Uterine blood flow is addressed through maternal positioning, fluid bolus, reducing uterine tachysystole, and minimizing vasoconstriction-not via amnioinfusion. Amnioinfusion does not physiologically affect uterine perfusion.
C). Treat oligohydramnios - CORRECT
Recurrent variables with thick meconium often occur in the setting of low fluid, which worsens cord compression.
NCC-recommended indications include:
Recurrent variable decelerations unresponsive to repositioning
Suspected or confirmed oligohydramnios
Thick meconium may be associated with low fluid, but the purpose of amnioinfusion is to alleviate cord compression by restoring fluid volume, not to dilute the meconium.
Thus, the correct answer is C. Treat oligohydramnios.
References:
NCC C-EFM Candidate Guide (2025); NCC Content Outline; AWHONN Fetal Heart Monitoring Principles
& Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 76
(Full question)
Spontaneous fetal heart rate accelerations indicate
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract (No URLs):
NCC references (AWHONN, Menihan, Simpson, Creasy & Resnik) consistently state that fetal accelerations are a reassuring sign of intact neurologic function. Accelerations represent the interaction of both the sympathetic and parasympathetic branches moderated through the central nervous system, reflecting effective autonomic regulation.
AWHONN specifically describes fetal accelerations as:
* A maturity marker of CNS function,
* Reflecting vigorous fetal movement,
* Demonstrating adequate oxygenation,
* Indicating a well-oxygenated brainstem and cortex.
Simpson & Miller emphasize that accelerations require both systems to be functioning and respond appropriately, which confirms CNS integration, not sympathetic or parasympathetic dominance alone.
Therefore, spontaneous accelerations indicate an integrated CNS response, making Option C the correct NCC-aligned answer.
NEW QUESTION # 77
The black pattern represents the heart rate pattern for Baby A. The blue pattern represents the heart rate pattern for Baby B. A possible etiology of the baseline fetal heart rate of Baby A is: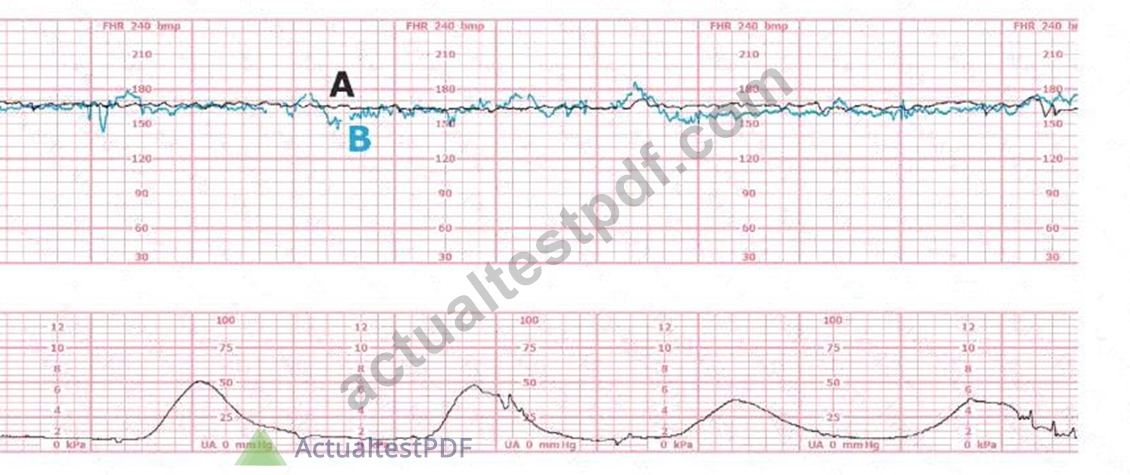
Answer: A
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
The black tracing (Baby A) demonstrates:
* Baseline ~170-175 bpm
* Moderate variability
* No recurrent decelerations
This is fetal tachycardia.
NCC physiology guidelines list common causes of fetal tachycardia:
* Maternal fever / infection (chorioamnionitis)
* Maternal dehydration
* Maternal anxiety
* Maternal hyperthyroidism
* Fetal infection
* Certain medications (terbutaline, illicit stimulants)
Why the other options are incorrect:
* A. Fetal positioning does not influence baseline heart rate.
* C. Magnesium sulfate typically lowers fetal baseline and variability-it does not cause tachycardia.
Thus, the most likely etiology is infection.
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; Menihan EFM; Simpson & Creehan; Creasy & Resnik.
NEW QUESTION # 78
......
How to find a valid exam dumps providers which can elaborate on how to prepare you properly with more appropriate questions to pass EFM exams? Yes, here is your chance to know us. Our products are just suitable for you. Our EFM exam training dumps will help you master the real test and prepare well for your exam. If you worry about your exam, our EFM Exam Training dumps will guide you and make you well preparing,you will pass exam without any doubt.
Technical EFM Training: https://www.actualtestpdf.com/NCC/EFM-practice-exam-dumps.html
P.S. Free 2026 NCC EFM dumps are available on Google Drive shared by ActualtestPDF: https://drive.google.com/open?id=1f-NoWUA_dB0ol6x1mBxNlJ5z5OkQ4YPy