What's more, part of that Itexamguide EFM dumps now are free: https://drive.google.com/open?id=1WjrVP_GZU69gklzbls6yFFiKKgK0w16L
Our EFM practice exam is specially designed for those people who have not any time to attend the class and prepare NCC exam tests with less energy. You will understand each point of questions and answers with the help of our EFM Exam Review. And our exam pass guide will cover the points and difficulties of the EFM real exam, getting certification are just a piece of cake.
| Section | Weight | Objectives |
|---|---|---|
| Physiology | 11% | - Maternal-Fetal Physiology
|
| Fetal Assessment Methods | 9% | - Assessment Techniques
|
| Pattern Recognition and Intervention | 70% | - Maternal and Fetal Complications
|
| Professional Issues | 5% | - Clinical Practice and Safety
|
| Electronic Monitoring Equipment | 5% | - Monitoring Systems
|
As you may know that we have become a famous brand for we have engaged for over ten years in this career. The system designed of EFM learning guide by our professional engineers is absolutely safe. Your personal information will never be revealed. Of course, our EFM Actual Exam will certainly not covet this small profit and sell your information. So you can just buy our EFM exam questions without any worries and trouble.
NEW QUESTION # 50
A woman at 38-weeks gestation is admitted to labor and delivery following a fall down the stairs three hours ago. She started feeling contractions in the ambulance. The fetal heart rate tracing shown is on initial evaluation and represents 25 minutes. This tracing is most consistent with a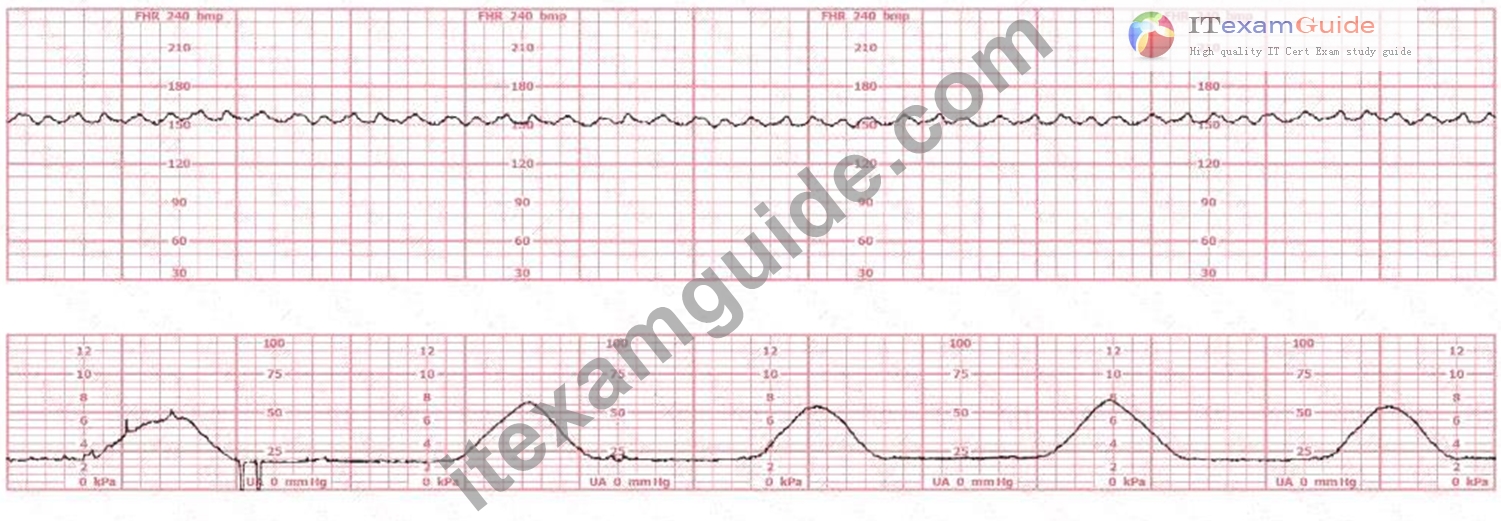
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract without any URL or Links According to the NCC C-EFM 2025 Candidate Guide, Pattern Recognition and Intervention requires the candidate to classify fetal heart rate (FHR) patterns using the NICHD 2008 three-tier system, which NCC endorses across all recommended resources (AWHONN Fetal Heart Monitoring Principles and Practices, Menihan Electronic Fetal Monitoring, Simpson & Creasy, Miller's Pocket Guide).
A Category II tracing is defined as "indeterminate" and includes any FHR pattern that is not Category I and not Category III. NCC references indicate that Category II may include:
* Minimal or marked variability
* Absence of accelerations after fetal stimulation
* Recurrent variable decelerations with moderate variability
* Prolonged decelerations lasting 2-10 minutes
* Baseline tachycardia or bradycardia without absent variability
In the tracing provided:
* The baseline FHR is approximately 135-145 bpm, within normal limits.
* Moderate variability is not consistently present; variability is borderline minimal-moderate at times.
* No significant accelerations are seen over the 25-minute evaluation period.
* No recurrent late or prolonged decelerations are present.
* There are occasional subtle variable-type dips, but not enough to meet criteria for Category III.
NCC-endorsed texts (such as AWHONN and Menihan) state that a tracing with minimal variability for less than 40 minutes and without recurrent decelerations is Category II, as it fails to meet the requirements for Category I (must have moderate variability and accelerations absent decelerations) and lacks the criteria for Category III (must have absent variability with recurrent late decels, recurrent variable decels, bradycardia, or sinusoidal pattern).
Therefore, this pattern is indeterminate, consistent with Category II, and requires continued surveillance and evaluation, which aligns with NCC-recommended clinical decision-making competencies.
NEW QUESTION # 51
An internal electronic fetal monitor tracing continues to record artifact despite equipment troubleshooting and replacement of the spiral electrode. The next action is to:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
When internal monitoring continues to record artifact despite:
* Changing the scalp electrode
* Ensuring correct attachment
* Checking cable connections
* Confirming maternal movement is not the cause
NCC requires confirmation of fetal well-being using another modality.
The correct next step is direct auscultation with Doppler or fetoscope.
Why other answers are incorrect:
* Oxygen is not indicated for equipment malfunction.
* Repositioning does not resolve internal FHR artifact.
Thus, Auscultate the fetal heart rate is the appropriate next step.
References:NCC C-EFM Candidate Guide; AWHONN; Miller's Pocket Guide; Menihan.
NEW QUESTION # 52
Tachysystole can have a negative effect on fetal oxygenation during labor by
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources NCC-recommended physiology references (AWHONN, Simpson & Creehan, Menihan, Creasy & Resnik) consistently state that the primary mechanism by which tachysystole affects fetal oxygenation is reduced uteroplacental perfusion, specifically through impaired intervillous space reperfusion.
During a normal contraction cycle, the fetus receives oxygen between contractions, when the uterus relaxes and maternal blood re-enters the intervillous space. AWHONN's Fetal Heart Monitoring Principles & Practices explains that tachysystole-defined as more than five contractions in 10 minutes averaged over 30 minutes-shortens or eliminates the relaxation phase, preventing adequate placental reoxygenation.
Simpson & Creehan highlight that "tachysystole decreases uteroplacental blood flow and interferes with replenishment of oxygenated maternal blood in the intervillous space." Menihan emphasizes that fetal hypoxemia in tachysystole results from interrupted perfusion, not from altered oxygen transport or maternal hemodynamic changes. Creasy & Resnik confirm that uterine overactivity reduces intervillous perfusion during contractions and impairs fetal oxygen exchange.
Thus, the physiologic problem is failure of the intervillous space to reperfuse, which compromises fetal oxygenation.
References:
AWHONN - Fetal Heart Monitoring Principles & PracticesSimpson & Creehan - Perinatal NursingMenihan
- Electronic Fetal MonitoringCreasy & Resnik - Maternal-Fetal MedicineMiller's Pocket Guide
NEW QUESTION # 53
A woman (G1, P0) at 41-weeks gestation presents to OB triage to rule out labor. Her cervical exam is 1 cm/50%/-2. Membranes are intact. She would like to go home if not in labor. Based on this tracing, which represents the last two hours, the best approach is: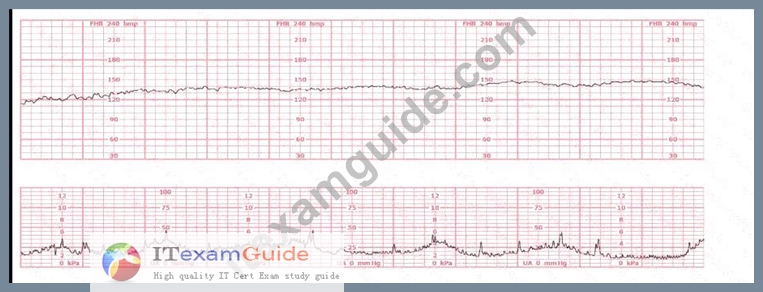
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources The fetal heart rate tracing shows a normal baseline (120-150 bpm), moderate variability, and no decelerations, consistent with a Category I pattern. According to AWHONN's Fetal Heart Monitoring Principles & Practices and NCC Perinatal Safety recommendations, a Category I tracing reliably indicates normal fetal acid-base status at the time of assessment and is considered reassuring.
Simpson & Creehan emphasize that in triage, management decisions depend on cervical status, contraction pattern, membrane status, and fetal well-being. With a cervix at 1 cm/50%/-2, intact membranes, and no regular labor pattern, she is not in active or latent labor requiring admission, provided fetal status is reassuring.
Menihan states that a normal tracing lasting two hours with moderate variability supports safe discharge when maternal and fetal assessments are normal. Creasy & Resnik confirm that reassuring fetal testing plus absence of labor is appropriate for outpatient management.
References:
AWHONN - Fetal Heart Monitoring Principles & PracticesSimpson & Creehan - Perinatal NursingMenihan
- Electronic Fetal MonitoringCreasy & Resnik - Maternal-Fetal MedicineMiller's Pocket Guide
NEW QUESTION # 54
Sustained fetal supraventricular tachycardia that goes untreated is most likely to result in:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
Sustained fetal supraventricular tachycardia (SVT) often produces heart rates > 200-240 bpm, causing:
* Poor ventricular filling
* Decreased stroke volume
* Reduced cardiac output
* Congestive heart failure
* Progressive fluid accumulation
NCC and AWHONN emphasize that untreated SVT leads to hydrops fetalis, characterized by:
* Ascites
* Pleural effusion
* Pericardial effusion
* Skin edema
Why the other answers are incorrect:
* A. Fetal anemia - Causes tachycardia but is not caused by SVT.
* C. Neonatal pacemaker - Pacemakers treat heart block, not SVT.
Correct answer: B. Hydrops fetalis
References:NCC C-EFM Candidate Guide; AWHONN Principles & Practices; Simpson & Creehan; Creasy
& Resnik Maternal-Fetal Medicine.
NEW QUESTION # 55
......
Our company has employed a lot of leading experts in the field to compile the Certified - Electronic Fetal Monitoring exam question. Our system of team-based working is designed to bring out the best in our people in whose minds and hands the next generation of the best EFM exam torrent will ultimately take shape. Our company has a proven track record in delivering outstanding after sale services and bringing innovation to the guide torrent. I believe that you already have a general idea about the advantages of our Certified - Electronic Fetal Monitoring exam question, but now I would like to show you the greatest strength of our EFM Guide Torrent --the highest pass rate. According to the statistics, the pass rate among our customers who prepared the exam under the guidance of our EFM guide torrent has reached as high as 98% to 100% with only practicing our EFM exam torrent for 20 to 30 hours.
Examcollection EFM Questions Answers: https://www.itexamguide.com/EFM_braindumps.html
DOWNLOAD the newest Itexamguide EFM PDF dumps from Cloud Storage for free: https://drive.google.com/open?id=1WjrVP_GZU69gklzbls6yFFiKKgK0w16L