BONUS!!! Download part of PracticeVCE EFM dumps for free: https://drive.google.com/open?id=1ly82VcFlaaZCb4XXKWw71ZhkXbNzft-Y
PracticeVCE EFM exam braindumps are authorized legal products which is famous for its high passing rate. Our dumps can cover nearly 95% questions of the real test, our answers and explanations are edited by many experienced experts and the correct rate is 100%. Our NCC EFM Exam Braindumps provide three versions to satisfy different kinds of customers' habits: PDF version, Soft test engine and APP test engine.
| Section | Objectives |
|---|---|
| Maternal and Fetal Complications | - Hypoxia and uteroplacental insufficiency - High-risk obstetric conditions affecting fetal monitoring |
| Uterine Activity | - Tachysystole and abnormal contraction patterns - Normal uterine contraction patterns |
| Intrauterine Resuscitation and Interventions | - Maternal position changes and oxygen administration - Fluid management and medication adjustments |
| Intrapartum Assessment and Monitoring | - External and internal monitoring techniques - Risk assessment during labor |
| Fetal Heart Rate Interpretation | - Category I, II, and III tracing interpretation - Accelerations and decelerations - Baseline rate and variability |
| Fetal Physiology and Oxygenation | - Oxygen transport and acid-base balance - Fetal cardiovascular physiology |
The 21 century is the information century. So there are many changes in the field of the EFM exam questions. They are also transforming people's lives and the mode of operation of human society in a profound way. when you are preparing for an EFM exam, our company can provide the best electronic EFM Exam Torrent for you in this website. I strongly believe that under the guidance of our EFM test torrent, you will be able to keep out of troubles way and take everything in your stride.
NEW QUESTION # 115
A woman at 39-weeks gestation is being induced. She has chronic hypertension controlled by methyldopa (Aldomet). Spontaneous rupture of membranes has occurred; she is 10 cm dilated and at +1 station. The fetal monitor tracing shown is obtained by spiral electrode and tocodynamometer. The next best appropriate action is to: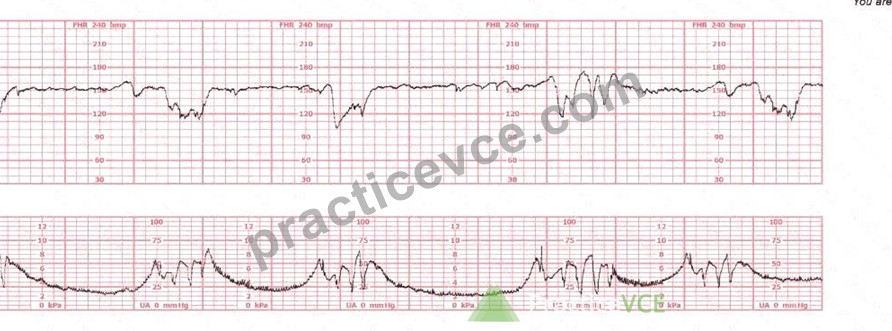
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The tracing shows recurrent variable decelerations deepening during contractions as the patient is fully dilated and at +1 station.
NCC's Pattern Recognition and Intervention framework states:
* During second stage (complete dilation), variable decelerations commonly occur from cord compression caused by head descent and maternal pushing efforts.
* The FIRST correction for pushing-associated recurrent variable decelerations is modifying the pushing technique:
* Side-lying pushing
* Pushing with every other contraction
* Open-glottis pushing
* Allowing passive descent
These measures relieve head compression and reduce the severity of variable decelerations.
Why the other answers are incorrect
A). Administer terbutaline
* Terbutaline is given for tachysystole with fetal intolerance.
* This tracing does not show tachysystole.
* The pattern is timing-related to pushing, not uterine overstimulation.
B). Consider amnioinfusion
* Amnioinfusion is used for recurrent variable decelerations before complete dilation, when membrane rupture + low fluid is suspected.
* At 10 cm and +1, the fetal head is deep in the pelvis, and the cause of variables is head compression, not cord compression due to oligohydramnios.
* Also, amnioinfusion is impractical and not beneficial at this stage.
Therefore, the correct answer is C. Modify pushing.
References:NCC C-EFM Candidate Guide; NCC Content Outline; AWHONN Principles & Practices; Miller' s Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan; Creasy & Resnik.
NEW QUESTION # 116
This tracing reflects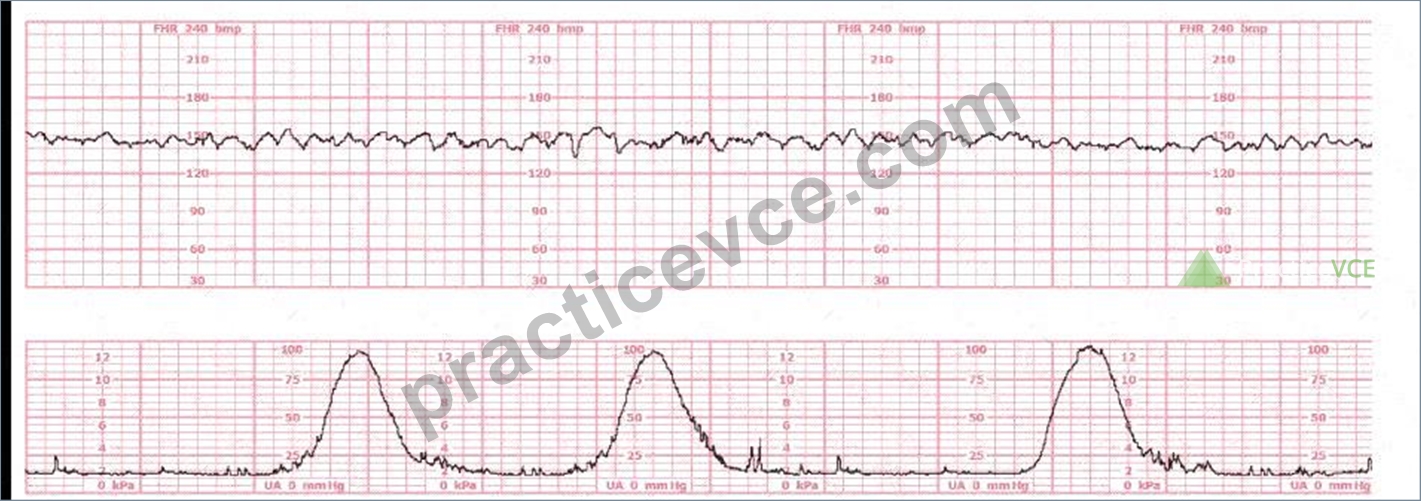
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract (NCC-Recommended Sources Only) The fetal heart rate (FHR) tracing shown demonstrates a baseline approximately 135-145 bpm with fluctuations of 6-25 bpm, a hallmark of moderate variability. Moderate variability is defined in all NCC- endorsed resources as the normal amplitude range of 6-25 bpm around the fetal baseline.
According to the AWHONN Fetal Heart Monitoring Principles & Practices (2022-2024), moderate variability is considered the single most reliable indicator of adequate fetal oxygenation and intact neurologic pathways, specifically reflecting well-functioning sympathetic and parasympathetic interplay.
The NICHD/NCC standardized definitions included in the NCC C-EFM Candidate Guide state:
* Minimal variability: amplitude range # 5 bpm
* Moderate variability: amplitude range 6-25 bpm
* Marked variability: amplitude > 25 bpm
* Sinusoidal pattern: smooth, undulating waveform, 3-5 cycles per minute, equal amplitude, absent beat-to-beat variability The tracing provided does not show the repetitive, smooth, wave-like pattern of a sinusoidal rhythm; nor does it show flattening associated with minimal variability. Instead, it includes continuous beat-to-beat fluctuation within the moderate range, without periods of absent or minimal variability.
Menihan's Electronic Fetal Monitoring (5th ed.) and Simpson & Creehan's Perinatal Nursing (5th ed.) both emphasize that moderate variability is:
* A reassuring feature
* Indicative of adequate fetal CNS oxygenation
* Expected in a reactive, well-oxygenated fetus
* A key criterion for Category I classification
Additionally, Miller's EFM Pocket Guide reiterates that variability between 6-25 bpm is considered the normal (moderate) fetal autonomic response and is not a sinusoidal pattern, which has a fixed amplitude and frequency.
Therefore, based on NCC-standard definitions and the observed amplitude, the correct interpretation is moderate variability.
References (No URLs):
AWHONN Fetal Heart Monitoring Principles & Practices; NCC C-EFM Candidate Guide 2025; Simpson & Creehan Perinatal Nursing; Menihan Electronic Fetal Monitoring; Miller's Pocket Guide to Fetal Monitoring; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 117
A patient at 41 weeks gestation is being induced. She has progressed slowly and is now at 6 cm, 90% effaced,
-1 station. She has the fetal heart tracing shown despite repositioning. The next step in the management of this patient should be to: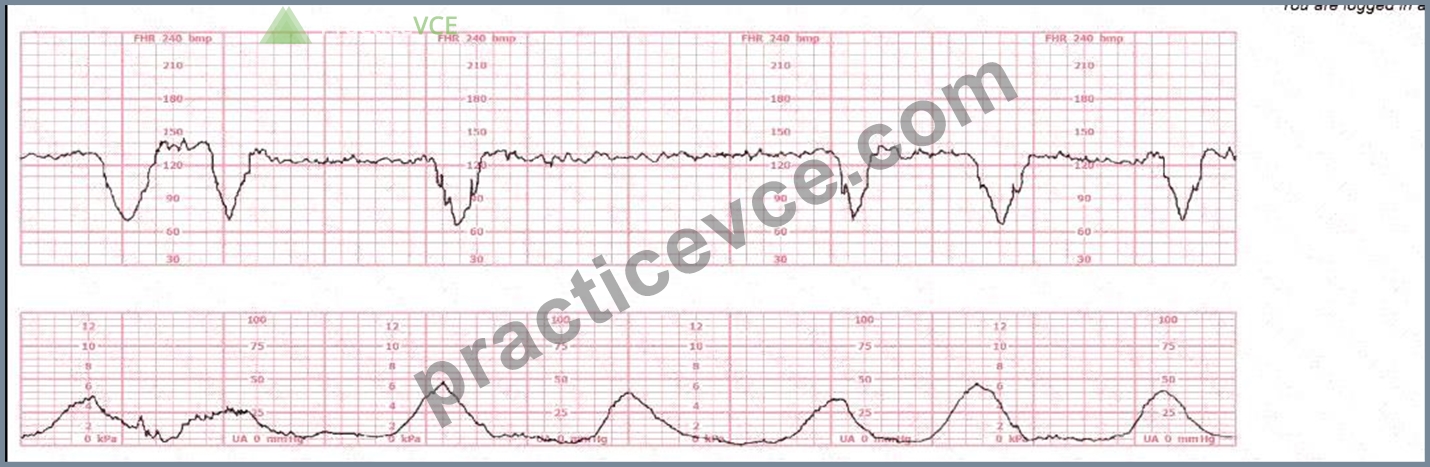
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The tracing clearly shows recurrent deep variable decelerations, characterized by:
* Abrupt onset (<30 sec)
* Sharp V-shape
* Rapid descent and ascent
* Depth exceeding 60-70 bpm drops
* Occurring with most contractions
This pattern is highly consistent with cord compression, which is the physiologic basis of variable decelerations. According to NCC, NICHD, AWHONN, Miller, and Menihan, recurrent (#50% of contractions) deep variables with slow return to baseline indicate fetal compromise and require targeted intervention.
The patient has already been repositioned, so first-line management has failed. NCC emphasizes that the next recommended intervention for recurrent variable decelerations, particularly when maternal repositioning is ineffective, is amnioinfusion. This intervention relieves cord compression by restoring fluid around the umbilical cord.
Why the other choices are incorrect:
A). Apply a spiral electrode - NOT appropriate
* Spiral electrodes improve signal quality but do not treat cord compression.
* The tracing is already clearly interpretable, and the issue is physiologic, not technical.
B). Decrease the oxytocin - Not the best next step
* Decreasing oxytocin is appropriate when tachysystole is contributing to fetal intolerance.
* This strip shows normal contraction frequency (about every 2-3 minutes) and no tachysystole.
* Thus, reducing oxytocin alone will not relieve cord compression.
C). Perform an amnioinfusion - CORRECT
NCC-approved references repeatedly state:
* For recurrent variable decelerations that persist after maternal repositioning, amnioinfusion is recommended to reduce the frequency and depth of decelerations.
* It can improve fetal oxygenation, decrease cord compression, and reduce the need for operative delivery.
* It is the intervention most directly targeted to the pathophysiology of this pattern.
Therefore, C. Perform an amnioinfusion is the correct next management step.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline; NICHD FHR Interpretation System; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal- Fetal Medicine.
NEW QUESTION # 118
A woman is admitted to labor and delivery with vaginal bleeding. This tracing is obtained. This is most consistent with: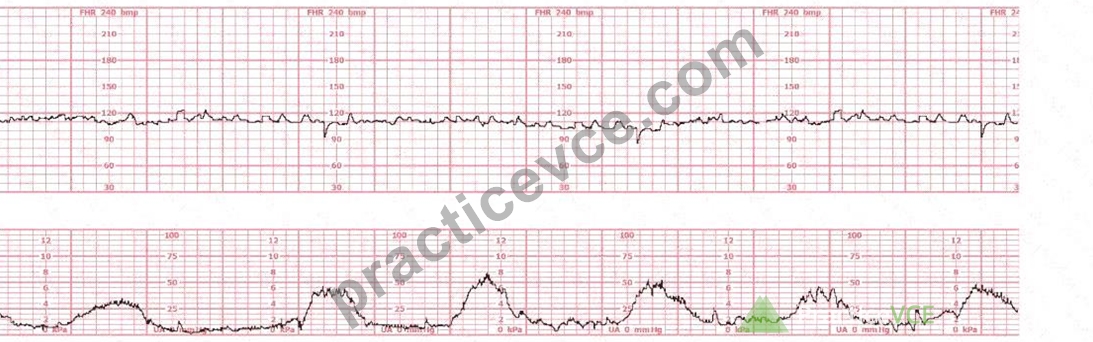
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The tracing shows:
* Baseline approx. 120 bpm
* Minimal variability (amplitude <5 bpm) across the entire strip
* No accelerations
* No decelerations
* Contractions present but not excessive
NCC defines:
* Category I requires moderate variability # not present.
* Category III requires absent variability with recurrent decels, bradycardia, or sinusoidal pattern # not present.
* Thus this falls into Category II: "indeterminate."
Minimal variability for this length of time cannot be considered a normal baseline, especially in the setting of vaginal bleeding, which raises concern for:
* Abruption
* Maternal anemia
* Hypovolemia
* Decreased uteroplacental perfusion
There is no evidence of dysrhythmia (no irregular R-R intervals, no chaotic spikes, no sawtooth pattern).
Therefore, the correct interpretation is A. An indeterminate pattern (Category II).
References:NCC C-EFM Candidate Guide; NICHD Definitions; AWHONN Principles & Practices; Menihan; Simpson & Creehan; Creasy & Resnik.
NEW QUESTION # 119
A woman experiences an eclamptic seizure during the second stage of labor. An anticipated fetal heart rate abnormality post-seizure would be:
Answer: A
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Emergency Fetal Response Principles:
Following an eclamptic seizure:
* Maternal hypoxia, apnea, and intense sympathetic discharge occur
* Uteroplacental perfusion drops
* Fetus experiences acute hypoxemia
* The expected fetal heart rate response is a prolonged bradycardia
This is well-described in NCC and AWHONN emergency physiology:
* "Post-seizure fetal bradycardia is common and often resolves within 5-10 minutes as maternal oxygenation stabilizes." Why other answers are incorrect:
* B. Sinusoidal pattern - Rare and usually indicates fetal anemia, not post-seizure status.
* C. Variable decelerations - Associated with cord compression, not seizures.
Correct answer: A. Bradycardia
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; Menihan; Simpson & Creehan.
NEW QUESTION # 120
......
Compared with those practice materials which are to no avail and full of hot air, our EFM guide tests outshine them in every aspect. If you make your decision of them, you are ready to be thrilled with the desirable results from now on. The passing rate of our EFM Exam Torrent is up to 98 to 100 percent, and this is a striking outcome staged anywhere in the world. They are appreciated with passing rate up to 98 percent among the former customers. So they are in ascendant position in the market.
EFM Practice Guide: https://www.practicevce.com/NCC/EFM-practice-exam-dumps.html
BONUS!!! Download part of PracticeVCE EFM dumps for free: https://drive.google.com/open?id=1ly82VcFlaaZCb4XXKWw71ZhkXbNzft-Y