DOWNLOAD the newest PrepAwayETE EFM PDF dumps from Cloud Storage for free: https://drive.google.com/open?id=18d6Ig6EoAd9exo8dLty5ERbxZ8HR36Oj
Passing the Certified - Electronic Fetal Monitoring certification test is an important step in professional development, and preparing with actual Certified - Electronic Fetal Monitoring exam questions can help applicants achieve this certification. The EFM Study Material promotes an organized approach to studying, aid applicants in identifying areas for development, build confidence and reduces exam anxiety. PrepAwayETE has created three formats for applicants to pass the Certified - Electronic Fetal Monitoring test on the first try.
| Section | Weight | Objectives |
|---|---|---|
| Physiology | 11% | - Factors affecting fetal oxygenation - Fetal cardiovascular physiology - Uteroplacental function |
| Pattern Recognition and Intervention | 70% | - Interpretation per NICHD standards - Tracing evaluation and management - Clinical decision-making and interventions - Fetal heart rate patterns classification |
| Fetal Assessment and Methods | 9% | - Auxiliary assessment techniques - Indications for monitoring - Correlation with clinical status |
| Professional Issues | 5% | - Legal and ethical aspects - Documentation standards - Safety and quality improvement |
| Electronic Monitoring Equipment | 5% | - Proper application and use - Calibration and accuracy - Troubleshooting artifacts |
Are you worrying about how to pass NCC EFM test? Now don't need to worry about the problem. PrepAwayETE that committed to the study of NCC EFM certification exam for years has a wealth of experience and strong exam dumps to help you effectively pass your exam. Whether to pass the exam successfully, it consists not in how many materials you have seen, but in if you find the right method. PrepAwayETE is the right method which can help you sail through NCC EFM Certification Exam.
NEW QUESTION # 74
When evaluating a baseline fetal heart rate change, the fetal heart rate is assessed for a minimum of:
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
NCC and NICHD define baseline FHR as the mean FHR rounded to increments of 5 bpm during a minimum of a 10-minute window, excluding:
* Accelerations
* Decelerations
* Marked variability
If a segment shorter than 10 minutes is used, it cannot be called a "baseline".
Thus the required minimum is 10 minutes.
References:NICHD Definitions; NCC C-EFM Candidate Guide; AWHONN; Miller's Pocket Guide.
NEW QUESTION # 75
A woman with hypertension at 38-weeks gestation has a biophysical profile. The result is 4/10 with decreased amniotic fluid volume. The next step should be to:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned BPP Management Standards:
NCC, AWHONN, and maternal-fetal medicine guidelines state:
* A BPP score of 4/10 at term is abnormal.
* A low score indicates hypoxia-related CNS suppression.
* Oligohydramnios is an additional high-risk finding, especially in hypertension.
* At # 37 weeks, a BPP score of # 4/10 warrants immediate delivery.
Repeating the test is acceptable at preterm gestations (e.g., < 32-34 weeks), but not at 38 weeks.
Why the other answers are incorrect:
* B. Discharge home - Contraindicated with abnormal BPP.
* C. Repeat in 24 hours - Not recommended at term with a score of 4.
Correct answer: A. Admit for delivery
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; Creasy & Resnik MFM; Simpson & Creehan; Menihan.
NEW QUESTION # 76
A woman is being induced with oxytocin. The tracing shown is representative of 20 minutes. Based on this tracing, the next step would be to: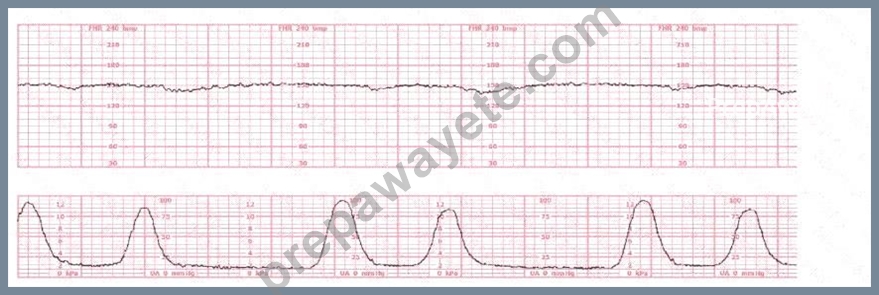
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
Evaluation of a tracing during oxytocin induction requires analysis of fetal status (baseline, variability, accelerations, decelerations) and uterine activity, with attention to tachysystole and fetal intolerance. NCC, AWHONN, Miller, Menihan, Simpson, and the NICHD guidelines all emphasize that oxytocin must be adjusted based on fetal response and contraction frequency.
Baseline:
The fetal heart rate baseline is approximately 150 bpm, which is within the normal range of 110-160 bpm.
Variability:
The tracing shows minimal variability (approximately 1-4 bpm amplitude). Minimal variability for a sustained period is categorized as a Category II pattern under NCC/NICHD classification.
Accelerations:
No accelerations are present during the 20-minute representative segment.
Decelerations:
There are no recurrent variable, no recurrent late, and no prolonged decelerations.
Uterine Activity:
The tracing shows very frequent contractions-approximately every 1½ to 2 minutes, which meets the NCC definition of tachysystole when averaged over 10 minutes (more than 5 contractions in 10 minutes).
According to NCC and AWHONN standards, when tachysystole is present with minimal variability, oxytocin must be reduced or discontinued even in the absence of late decelerations.
Clinical decision-making (per NCC principles):
NCC emphasizes that management of Category II patterns during induction starts with intrauterine resuscitative measures, including decreasing or stopping oxytocin when uterine activity is excessive or fetal response is suboptimal. Minimal variability with tachysystole requires correction of uterine stimulation before escalating to invasive monitoring or considering operative birth.
Option B (place a spiral electrode) is not indicated because the pattern is clearly visible and the priority is correcting uterine overstimulation, not refining the tracing.
Option C (operative birth) is not indicated; there is no Category III pattern or recurrent decelerations.
Option A (discontinue oxytocin) is the correct first-line action according to NCC-aligned guidelines when tachysystole and minimal variability occur.
References:
NCC C-EFM Candidate Guide (2025); NCC Content Outline; NICHD Three-Tier FHR Interpretation System; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 77
This fetal heart rate tracing represents: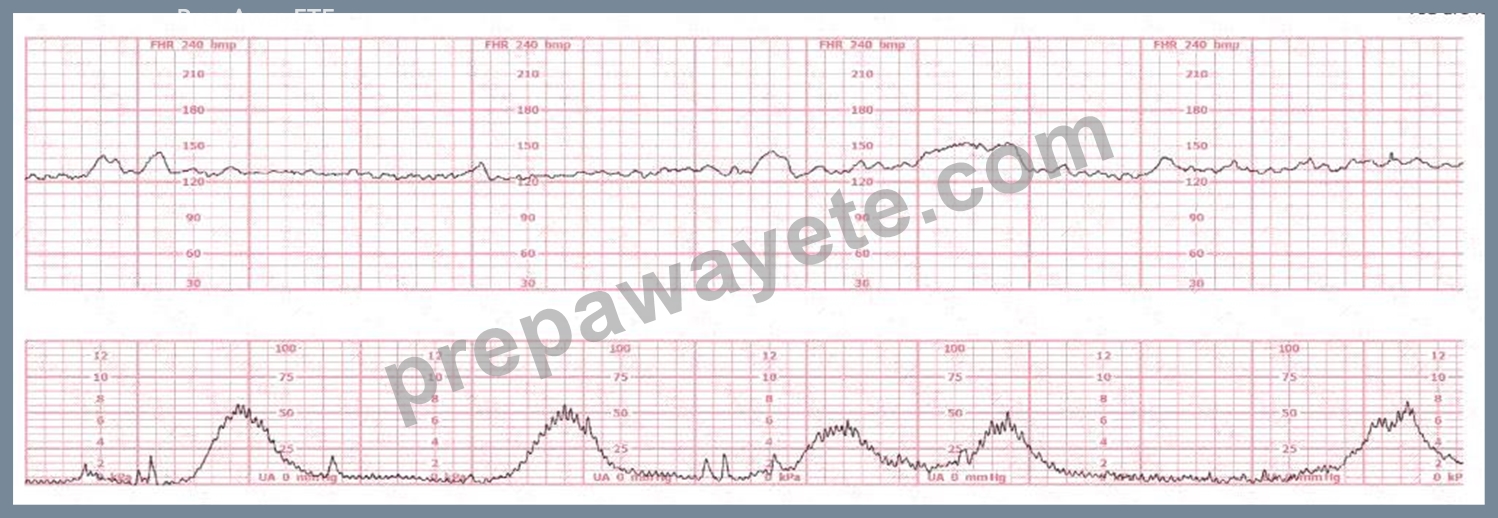
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The lower uterine tracing shows a repetitive contraction pattern characterized by pairs of contractions occurring close together, followed by a longer interval. This is known as "uterine contraction coupling." Key features confirming coupling:
* Two contractions occur back-to-back, separated by only a few seconds.
* Then a longer rest period occurs before the next pair.
* This pattern persists over several minutes.
* FHR remains normal with moderate variability and no decelerations.
Coupling is a uterine activity pattern, not a fetal heart rate abnormality.
Why the other answers are incorrect
A). Category I tracing
* While the FHR itself may appear reassuring, the question is explicitly about the pattern shown, which is (per NCC classification) a uterine pattern, not a category designation.
C). Prolonged acceleration
* A prolonged acceleration would be a fetal heart rate increase #15 bpm lasting #2 minutes but <10 minutes.
* No such FHR increase appears on the strip.
Thus, the correct interpretation is B. Coupling of contractions.
References:NCC C-EFM Candidate Guide; AWHONN Fetal Heart Monitoring Principles & Practices; Miller' s Pocket Guide; Menihan; Simpson & Creehan.
NEW QUESTION # 78
Maternal-fetal oxygen transfer takes place in the:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Physiologic Sources:
Oxygen transfer occurs at the maternal-fetal interface within the intervillous space, where:
* Maternal blood from the spiral arteries bathes the chorionic villi
* Diffusion occurs between maternal blood and fetal capillary beds
* Oxygen then travels through fetal circulation via the umbilical vein
Thus:
* Intervillous space = site of gas exchange
* Spiral arteries = deliver maternal blood to that space
* Umbilical vein = fetal vessel carrying oxygenated blood after exchange has occurred Correct answer: A. Intervillous space References:NCC Physiology Domain; AWHONN FHMPP; Creasy & Resnik; Simpson & Creehan.
NEW QUESTION # 79
......
We provide three versions of EFM study materials to the client and they include PDF version, PC version and APP online version. Different version boosts own advantages and using methods. The content of EFM exam torrent is the same but different version is suitable for different client. For example, the PC version of EFM study materials supports the computer with Windows system and its advantages includes that it simulates real operation exam environment and it can simulates the exam and you can attend time-limited exam on it. And whatever the version is the users can learn the EFM Guide Torrent at their own pleasures. The titles and the answers are the same and you can use the product on the computer or the cellphone or the laptop.
EFM Accurate Study Material: https://www.prepawayete.com/NCC/EFM-practice-exam-dumps.html
2026 Latest PrepAwayETE EFM PDF Dumps and EFM Exam Engine Free Share: https://drive.google.com/open?id=18d6Ig6EoAd9exo8dLty5ERbxZ8HR36Oj