P.S. Free 2026 NCC EFM dumps are available on Google Drive shared by Dumpleader: https://drive.google.com/open?id=1DWcDbsnAqvDrRP5YubTs-R-iUPMZrYWa
If you still have no confidence for passing test, here we will recommend you an excellent reference material. Our valid EFM exam collection pdf will help you pass exam and go to success, you will approach to IT field top. You can just spend short time in preparing for real test with our latest EFM Exam Collection Pdf. You can download free demo in our website for your reference to verify the reliability of our dumps before purchasing.
| Section | Objectives |
|---|---|
| Topic 1: Intrauterine Resuscitation and Interventions | - Fluid management and medication adjustments - Maternal position changes and oxygen administration |
| Topic 2: Fetal Heart Rate Interpretation | - Category I, II, and III tracing interpretation - Accelerations and decelerations - Baseline rate and variability |
| Topic 3: Fetal Physiology and Oxygenation | - Oxygen transport and acid-base balance - Fetal cardiovascular physiology |
| Topic 4: Maternal and Fetal Complications | - High-risk obstetric conditions affecting fetal monitoring - Hypoxia and uteroplacental insufficiency |
| Topic 5: Uterine Activity | - Normal uterine contraction patterns - Tachysystole and abnormal contraction patterns |
| Topic 6: Intrapartum Assessment and Monitoring | - Risk assessment during labor - External and internal monitoring techniques |
Our company is no exception, and you can be assured to buy our EFM exam prep. Our company has been focusing on the protection of customer privacy all the time. We can make sure that we must protect the privacy of all customers who have bought our EFM test questions. If you decide to use our EFM test torrent, we are assured that we recognize the importance of protecting your privacy and safeguarding the confidentiality of the information you provide to us. We hope you will use our EFM Exam Prep with a happy mood, and you don’t need to worry about your information will be leaked out.
NEW QUESTION # 25
A woman (G1, P0) at 41-weeks gestation presents to OB triage to rule out labor. Her cervical exam is 1 cm/50%/-2. Membranes are intact. She would like to go home if not in labor. Based on this tracing, which represents the last two hours, the best approach is: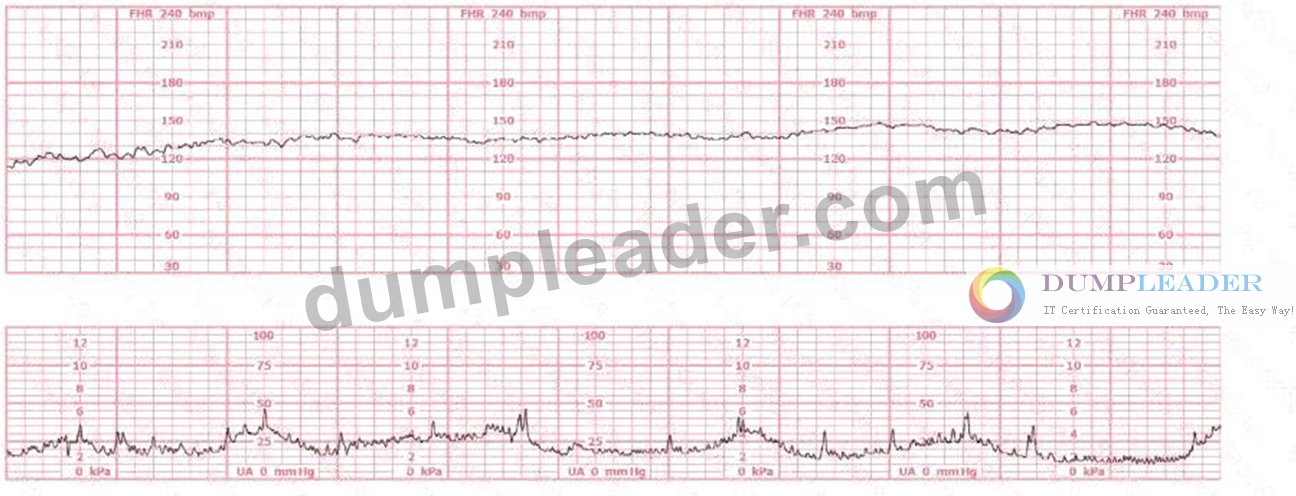
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources The fetal heart rate tracing shows a normal baseline (120-150 bpm), moderate variability, and no decelerations, consistent with a Category I pattern. According to AWHONN's Fetal Heart Monitoring Principles & Practices and NCC Perinatal Safety recommendations, a Category I tracing reliably indicates normal fetal acid-base status at the time of assessment and is considered reassuring.
Simpson & Creehan emphasize that in triage, management decisions depend on cervical status, contraction pattern, membrane status, and fetal well-being. With a cervix at 1 cm/50%/-2, intact membranes, and no regular labor pattern, she is not in active or latent labor requiring admission, provided fetal status is reassuring.
Menihan states that a normal tracing lasting two hours with moderate variability supports safe discharge when maternal and fetal assessments are normal. Creasy & Resnik confirm that reassuring fetal testing plus absence of labor is appropriate for outpatient management.
References:
AWHONN - Fetal Heart Monitoring Principles & PracticesSimpson & Creehan - Perinatal NursingMenihan
- Electronic Fetal MonitoringCreasy & Resnik - Maternal-Fetal MedicineMiller's Pocket Guide
NEW QUESTION # 26
A woman in labor has been pushing for 4 hours. For the last 2 hours, there have been recurrent variable decelerations. Variability has evolved from moderate to minimal. Cervical exam is 10/100%
/+2, fetal head OP. There has been no fetal descent for the last 45 minutes. Based on the tracing shown, the most reasonable approach is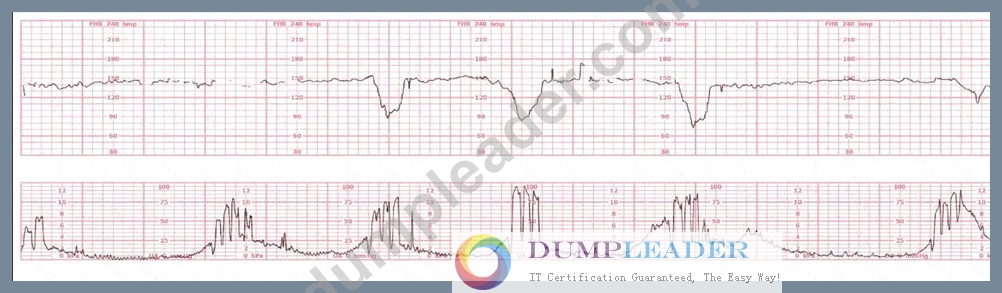
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract (NCC-Referenced Sources) According to the NCC C-EFM Exam Outline and AWHONN Fetal Heart Monitoring (5th & 6th ed.), recurrent variable decelerations with progressive reduction in variability reflect worsening fetal hypoxia, especially when coupled with prolonged second stage and arrest of descent.
AWHONN and Menihan both state that:
* "Minimal variability with recurrent decelerations indicates inability of the fetus to maintain adequate oxygenation."
* "Failure of descent in second stage with non-reassuring patterns requires operative delivery." Creasy & Resnik emphasize that operative vaginal birth requires:
(1) fetal head at +2 station or below,
(2) favorable position,
(3) reassuring fetal status.
Here, the fetus is OP, descent has arrested, and FHR is non-reassuring. This contraindicates vacuum extraction.
Therefore, the appropriate management under NCC competencies is cesarean birth.
NEW QUESTION # 27
This fetal heart rate tracing is obtained upon the woman's admission to labor and delivery. This tracing is most reflective of: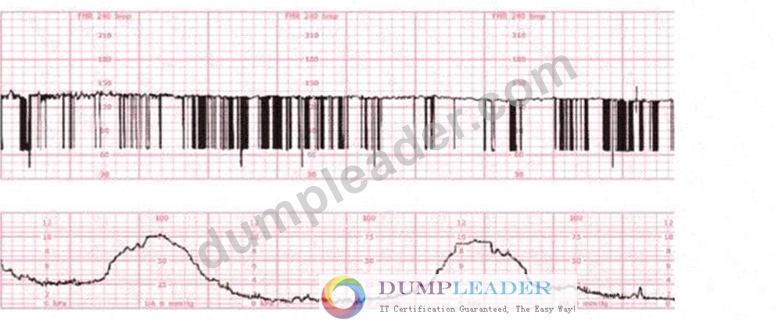
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
When evaluating an admission tracing, NCC emphasizes determining whether the pattern represents baseline variability abnormalities, signal artifact, or an underlying fetal cardiac rhythm disturbance. The strip shown contains clear features of a fetal dysrhythmia, which NCC and AWHONN describe as an irregular rhythm characterized by inconsistent R-R intervals or intermittent missed beats.
Key features in this tracing:
* Extremely irregular FHR signalThe pattern shows abrupt vertical spikes, inconsistent spacing, and intermittent loss of coherent waveform. NCC teaches that this appearance is typical of irregular ventricular conduction or premature atrial/ventricular contractions.
* Wide variability in beat spacingBeat intervals vary significantly, suggesting ectopic beats or conduction abnormalities rather than a stable rhythm such as heart block or atrial flutter.
* Sensor not malfunctioningThe lower uterine activity channel is smooth and consistent, meaning the upper channel's abrupt changes represent true FHR signal irregularity, not artifact.
Why the incorrect answers are ruled out:
A). Atrial flutter - NOT supported
* Atrial flutter produces a very fast, regular atrial rate (typically 300 bpm) with a repetitive saw-tooth pattern.
* It does not produce the highly irregular beat-to-beat pattern seen here.
* FHR in atrial flutter appears more organized, not chaotic.
B). Complete heart block - NOT supported
* Complete heart block (third-degree AV block) produces a very slow, regular ventricular rate, commonly 50-70 bpm, with a dissociation between atrial and ventricular rhythms.
* The tracing here does not show a slow, steady baseline.
* Instead, the rhythm is highly irregular with spikes and losses-not characteristic of AV block.
C). Fetal dysrhythmia - CORRECT
* NCC, AWHONN, Miller, and Menihan describe fetal dysrhythmias as:"Irregular, inconsistent FHR patterns due to premature atrial contractions (PACs), premature ventricular contractions (PVCs), or intermittent conduction disturbances."
* The hallmark is an irregular rhythm, often appearing as abrupt spikes or missing beats on the monitor.
* The tracing shown matches these characteristics precisely.
Therefore, the tracing is most consistent with fetal dysrhythmia, typically benign PACs/PVCs, and is the correct answer.
References:NCC C-EFM Candidate Guide (2025); NCC Content Outline; AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 28
The duration of a contraction is best represented by which colored arrow?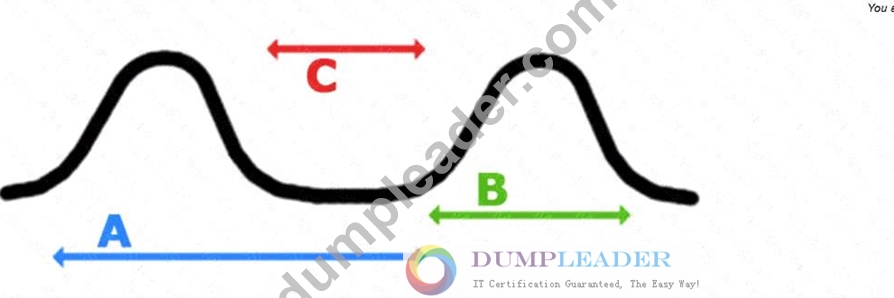
Answer: A
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
Contraction duration is defined as the length of time from the beginning of a contraction to the end of the same contraction (NICHD uterine activity definitions).
In the diagram:
* Green arrow (B) spans one individual contraction from rise # peak # return to baseline.
* Blue arrow (A) measures the interval between contractions (frequency).
* Red arrow (C) measures peak-to-peak amplitude shape, not duration.
Therefore, the green arrow correctly identifies contraction duration.
References:NCC Candidate Guide; AWHONN FHMPP; Menihan EFM; Simpson & Creehan.
NEW QUESTION # 29
Tachysystole can have a negative effect on fetal oxygenation during labor by
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources NCC-recommended physiology references (AWHONN, Simpson & Creehan, Menihan, Creasy & Resnik) consistently state that the primary mechanism by which tachysystole affects fetal oxygenation is reduced uteroplacental perfusion, specifically through impaired intervillous space reperfusion.
During a normal contraction cycle, the fetus receives oxygen between contractions, when the uterus relaxes and maternal blood re-enters the intervillous space. AWHONN's Fetal Heart Monitoring Principles & Practices explains that tachysystole-defined as more than five contractions in 10 minutes averaged over 30 minutes-shortens or eliminates the relaxation phase, preventing adequate placental reoxygenation.
Simpson & Creehan highlight that "tachysystole decreases uteroplacental blood flow and interferes with replenishment of oxygenated maternal blood in the intervillous space." Menihan emphasizes that fetal hypoxemia in tachysystole results from interrupted perfusion, not from altered oxygen transport or maternal hemodynamic changes. Creasy & Resnik confirm that uterine overactivity reduces intervillous perfusion during contractions and impairs fetal oxygen exchange.
Thus, the physiologic problem is failure of the intervillous space to reperfuse, which compromises fetal oxygenation.
References:
AWHONN - Fetal Heart Monitoring Principles & PracticesSimpson & Creehan - Perinatal NursingMenihan
- Electronic Fetal MonitoringCreasy & Resnik - Maternal-Fetal MedicineMiller's Pocket Guide
NEW QUESTION # 30
......
After you use EFM real exam,you will not encounter any problems with system . If you really have a problem, please contact us in time and our staff will troubleshoot the issue for you. EFM exam practice’s smooth operating system has improved the reputation of our products. We also received a lot of praise in the international community. I believe this will also be one of the reasons why you choose our EFM Study Materials.
Mock EFM Exam: https://www.dumpleader.com/EFM_exam.html
2026 Latest Dumpleader EFM PDF Dumps and EFM Exam Engine Free Share: https://drive.google.com/open?id=1DWcDbsnAqvDrRP5YubTs-R-iUPMZrYWa