What's more, part of that Prep4King EFM dumps now are free: https://drive.google.com/open?id=1oppOVjFTe-FSzXnNOsB9UunaHuagDy8s
It Contains a pool of real NCC EFM exam questions. This Certified - Electronic Fetal Monitoring (EFM) practice test is compatible with every windows-based system. One downloaded does not require an active internet connection to operate. You can self-evaluate your mistakes after each EFM Practice Exam attempt and work on the weak points that require more attention.
| Section | Objectives |
|---|---|
| Topic 1: Intrapartum Assessment and Monitoring | - External and internal monitoring techniques - Risk assessment during labor |
| Topic 2: Maternal and Fetal Complications | - Hypoxia and uteroplacental insufficiency - High-risk obstetric conditions affecting fetal monitoring |
| Topic 3: Fetal Heart Rate Interpretation | - Accelerations and decelerations - Baseline rate and variability - Category I, II, and III tracing interpretation |
| Topic 4: Uterine Activity | - Normal uterine contraction patterns - Tachysystole and abnormal contraction patterns |
| Topic 5: Fetal Physiology and Oxygenation | - Oxygen transport and acid-base balance - Fetal cardiovascular physiology |
| Topic 6: Intrauterine Resuscitation and Interventions | - Fluid management and medication adjustments - Maternal position changes and oxygen administration |
Sharp tools make good work. Valid EFM test questions and answers will make your exam easily. If you still feel difficult in passing exam, our products are suitable for you. EFM test questions and answers are worked out by Prep4King professional experts who have more than 8 years in this field. With so many years' development, we can keep stable high passing rate for NCC EFM Exam. You will only spend dozens of money and 20-30 hours' preparation on our EFM test questions, passing exam is easy for you.
NEW QUESTION # 66
Usually, the duration of an early deceleration in comparison with the contraction is:
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
An early deceleration is defined by NICHD and NCC as a gradual decrease and return of the fetal heart rate associated with uterine contractions. NCC emphasizes that early decelerations are:
* Symmetrical
* Uniform in shape
* Mirror images of the contraction
This means:
* Onset of deceleration = onset of contraction
* Nadir of deceleration = peak of contraction
* Recovery = end of contraction
* Duration of the deceleration # duration of the contraction
Thus, the correct answer is C. The same.
References:NCC C-EFM Candidate Guide; AWHONN Fetal Heart Monitoring Principles & Practices; NICHD Definitions; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing.
NEW QUESTION # 67
Maternal conditions of autoimmunity can result in fetal heart block due to antibodies that target:
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
NCC physiology content specifically includes maternal autoimmune influences on fetal cardiac conduction.
Conditions such as maternal lupus (SLE) or Sjogren's syndrome may produce anti-Ro/SSA and anti-La
/SSB antibodies. These antibodies cross the placenta and damage fetal conduction tissue.
The primary site of injury is the fetal atrioventricular (AV) node, leading to:
* First-, second-, or complete third-degree heart block
* A slow, regular ventricular rate typically 50-70 bpm
* Loss of beat-to-beat variability because ventricular myocardium does not display normal autonomic modulation This mechanism is extensively described in AWHONN, NCC physiology materials, and maternal-fetal physiology texts.
Option A: Antibodies do not target fetal RBCs; that describes hemolytic disease of the newborn.
Option B: Targeting maternal WBCs is not fetal-specific.
The correct affected structure is the fetal AV node.
Therefore, the correct answer is C. The fetal atrioventricular node.
References:NCC C-EFM Candidate Guide (2025); NCC Physiology Content Outline; AWHONN Fetal Heart Monitoring Principles & Practices; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine.
NEW QUESTION # 68
A woman at 39-weeks gestation is in early labor, 2-3 cm dilated, 85% effaced, and -2 station. Based on the fetal heart rate tracing shown, what is the most appropriate first intervention?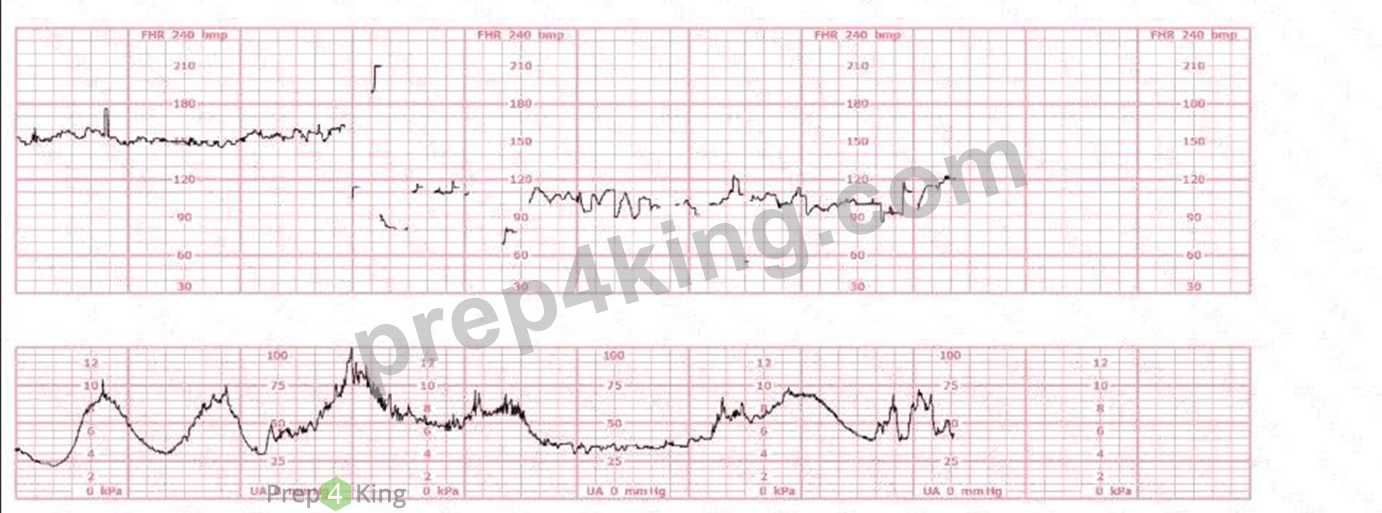
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The tracing shows significant artifact, periods of signal loss, and abrupt changes inconsistent with physiologic fetal patterns. This is typical of poor signal quality, not actual fetal decelerations. In early labor at -2 station, external FHR monitoring often loses contact due to fetal position and maternal movement.
NCC and AWHONN emphasize the following when artifact is present:
* Correct signal quality before interpreting the tracing.
* Troubleshooting steps include:- Adjusting transducer location- Ensuring adequate ultrasound gel- Repositioning the mother- Checking for maternal heart rate contamination Why the other options are incorrect:
* B. IV fluid bolus - Indicated for hypotension or late decelerations, not for artifact.
* C. Terbutaline - Used for tachysystole with fetal intolerance; there is no tachysystole shown.
Thus, the correct first step is A. Adjust the fetal monitor.
References:NCC C-EFM Candidate Guide; AWHONN Fetal Heart Monitoring Principles & Practices; Miller' s Pocket Guide; Menihan; Simpson & Creehan.
NEW QUESTION # 69
(Full question statement)
A dysrhythmia is noted. The pregnancy and labor course has been normal with no complications. The next step in management is to
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract (NCC C-EFM sources: AWHONN, Miller's Pocket Guide, Menihan, Simpson, Creasy & Resnik, 2025 Candidate Guide) AWHONN and Menihan emphasize that most fetal dysrhythmias detected intrapartum are premature atrial contractions (PACs)-the most common benign rhythm variation. They typically appear as intermittent, irregular deflections on the fetal heart rate tracing without affecting variability or baseline.
Miller's Pocket Guide to Fetal Monitoring states that PACs are usually transient, self-limiting, and require only observation unless accompanied by tachyarrhythmia or hemodynamic compromise. When variability is preserved and no repetitive pattern or sustained tachycardia occurs, no intrauterine resuscitation measures are indicated.
Simpson and Creehan describe that oxygen administration and fluid boluses are not recommended for benign dysrhythmias, as they do not improve fetal conduction patterns and may contribute to unnecessary interventions.
The NCC 2025 Candidate Guide specifies that correct management requires distinguishing benign arrhythmias from pathologic tachyarrhythmias, which would require escalation. In the absence of fetal compromise or maternal pathology, the appropriate action is continued observation.
Therefore, the correct management is to continue to observe.
NEW QUESTION # 70
A woman in labor has been pushing for 4 hours. For the last 2 hours, there have been recurrent variable decelerations. Variability has evolved from moderate to minimal. Cervical exam is 10/100%
/+2, fetal head OP. There has been no fetal descent for the last 45 minutes. Based on the tracing shown, the most reasonable approach is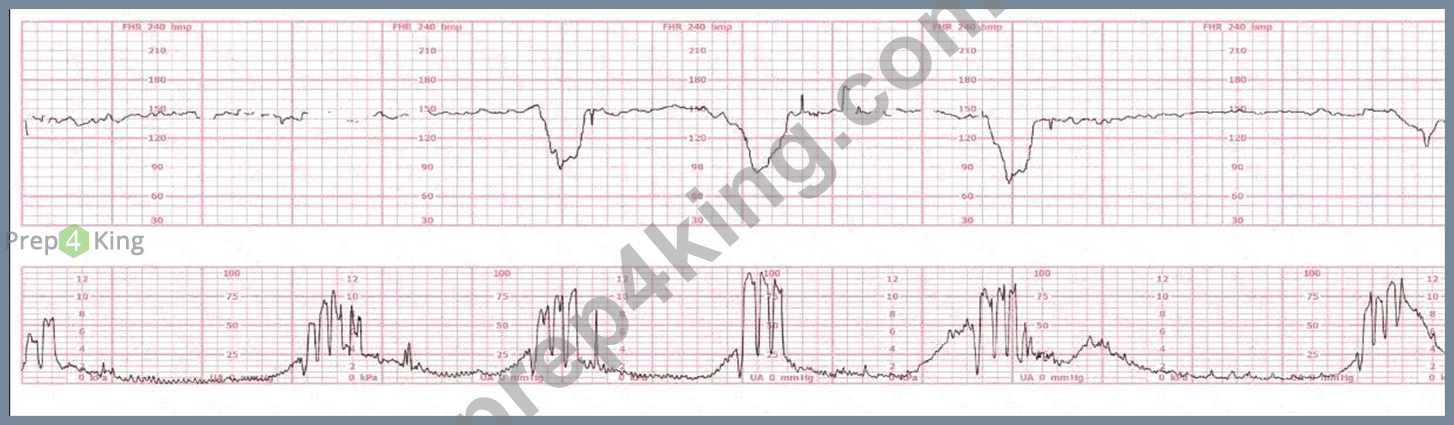
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract (NCC-Referenced Sources) According to the NCC C-EFM Exam Outline and AWHONN Fetal Heart Monitoring (5th & 6th ed.), recurrent variable decelerations with progressive reduction in variability reflect worsening fetal hypoxia, especially when coupled with prolonged second stage and arrest of descent.
AWHONN and Menihan both state that:
* "Minimal variability with recurrent decelerations indicates inability of the fetus to maintain adequate oxygenation."
* "Failure of descent in second stage with non-reassuring patterns requires operative delivery." Creasy & Resnik emphasize that operative vaginal birth requires:
(1) fetal head at +2 station or below,
(2) favorable position,
(3) reassuring fetal status.
Here, the fetus is OP, descent has arrested, and FHR is non-reassuring. This contraindicates vacuum extraction.
Therefore, the appropriate management under NCC competencies is cesarean birth.
NEW QUESTION # 71
......
A certificate may be important for someone who wants to get a good job through it, we have the EFM Learning Materials for you to practice, so that you can pass. EFM Learning materials of our company is pass rate guarantee and money back guarantee if you fail the exam. Free update is also available, you will have the latest version if you want after the purchasing. Our service stuff is also very glad to help you if you have any questions.
Latest EFM Exam Questions: https://www.prep4king.com/EFM-exam-prep-material.html
BTW, DOWNLOAD part of Prep4King EFM dumps from Cloud Storage: https://drive.google.com/open?id=1oppOVjFTe-FSzXnNOsB9UunaHuagDy8s