What's more, part of that Prep4sureExam CPHRM dumps now are free: https://drive.google.com/open?id=1NUIT155auLj9R50TQ9h8jf1mR9ih_-v-
In order to save a lot of unnecessary trouble to users, we have completed our CPHRM study questions research and development of online learning platform, users do not need to download and install, only need your digital devices have a browser, can be done online operation of the CPHRM test guide. This kind of learning method is very convenient for the user, especially in the time of our fast pace to get CPHRM Certification. When using our CPHRM training materials, all the operations of the CPHRM learning material of can be applied perfectly.
| Certification Vendor: | ASHRM (American Society for Health Care Risk Management) |
|---|---|
| Exam Name: | Certified Professional in Health Care Risk Management |
| Exam Number: | CPHRM |
| Certificate Validity Period: | 3 years |
| Exam Duration: | 120 minutes |
| Available Languages: | English |
| Exam Format: | Multiple-choice |
| Passing Score: | Not publicly disclosed |
| Related Certifications: | CPHRM |
| Real Exam Qty: | 110 |
| Exam Price: | USD 275 (ASHRM/AHA members) / USD 425 (non-members) |
| Sample Questions: | ASHRM CPHRM Sample Questions |
| Exam Way: | Computer-based testing at PSI test centers (250+ locations in US) |
| Pre Condition: | Minimum 3,000 hours full-time healthcare risk management experience; plus education requirements: High school diploma + 9 years healthcare experience, OR Associate degree + 7 years healthcare experience, OR Bachelor's degree or higher + 5 years healthcare experience. |
| Official Syllabus URL: | https://www.ashrm.org/topics/certified-professional-healthcare-risk-management-cphrm |
>> Complete CPHRM Exam Dumps <<
First of all, we have the best and most first-class operating system, in addition, we also solemnly assure users that users can receive the information from the CPHRM certification guide within 5-10 minutes after their payment. Second, once we have written the latest version of the CPHRM certification guide, our products will send them the latest version of the CPHRM Test Practice question free of charge for one year after the user buys the CPHRM exam questions. Last but not least, our perfect customer service staff will provide users with the satisfaction in the hours.
| Topic | Details |
|---|---|
| Topic 1 |
|
| Topic 2 |
|
| Topic 3 |
|
| Topic 4 |
|
| Topic 5 |
|
NEW QUESTION # 109
The following is a table of expense and indemnity figures for an organization's last 6 years.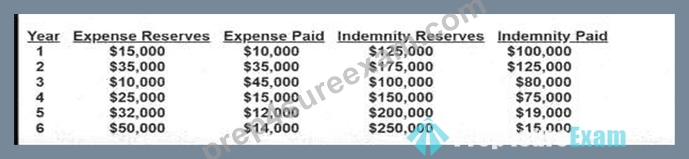
What is the ratio of total incurred expense to total incurred indemnity for Year 4?
Answer: C
Explanation:
According to Health Care Risk Management principles supported by ASHRM and the American Hospital Association Certification Center, total incurred amounts include both paid amounts and reserves. Incurred expense equals expense paid plus expense reserves. Incurred indemnity equals indemnity paid plus indemnity reserves.
For Year 4:
Total incurred expense = $25,000 reserves + $15,000 paid = $40,000.
Total incurred indemnity = $150,000 reserves + $75,000 paid = $225,000.
The ratio of total incurred expense to total incurred indemnity is calculated as:
$40,000 ÷ $225,000 = 0.1778, which rounds to approximately 0.18.
However, among the answer options provided, the closest value is 0.20 only if rounded broadly. Since precise calculation yields approximately 0.18, the mathematically correct ratio is approximately 0.18.
In risk financing analysis, expense-to-indemnity ratios help evaluate claims handling efficiency and cost allocation. Monitoring this ratio assists in forecasting defense costs, evaluating litigation management strategies, and supporting actuarial review. Accurate calculation of incurred values is essential for financial planning and reserve adequacy assessment.
NEW QUESTION # 110
An indemnification clause in a contract is designed to
Answer: D
Explanation:
According to Health Care Risk Management standards supported by ASHRM and the American Hospital Association Certification Center, an indemnification clause is a contractual risk transfer mechanism that defines one party's obligation to compensate another for specified losses, liabilities, damages, or claims arising from the contract relationship. Its purpose is to allocate financial responsibility and clarify which party will bear costs if certain events occur.
Indemnification provisions typically address responsibility for defense costs, settlements, judgments, and related expenses. The scope of indemnity depends on negotiated language and may include limitations, exclusions, or requirements for notice and cooperation. Properly drafted indemnification clauses are critical in vendor agreements, physician contracts, and service arrangements to manage exposure and reduce organizational liability.
Creating a forum for dispute resolution is addressed through arbitration or venue clauses. Holding another party responsible for fulfilling contract terms relates to performance obligations rather than indemnification.
Automatically deferring all legal costs is inaccurate because indemnification is triggered only under specific contractual conditions.
Legal and regulatory objectives emphasize careful contract review, clear allocation of liability, and structured risk transfer. Therefore, an indemnification clause clarifies commitments to compensate the other party for harm, liability, or loss.
NEW QUESTION # 111
A root cause analysis of inpatient suicides would be most likely to discover problems with:
Answer: D
Explanation:
Inpatient suicide prevention is a high-stakes patient safety domain where RCAs frequently identify environmental hazards-particularly ligature risks, blind spots, and unit design that limits observation. Joint Commission-style reviews and published analyses note that thephysical environmentis commonly
"incriminated" in inpatient suicides, emphasizing design/engineering controls alongside clinical monitoring.
Risk management objectives prioritize layered defenses: ligature-resistant fixtures, environmental rounding, safe room standards, removal control for risky items, and observation policies matched to patient risk.
Environmental mitigation is especially powerful because it reduces reliance on perfect human vigilance (which is not realistic). By treating suicide prevention as a systems problem-not an individual failure- organizations improve reliability and reduce recurrence. Environmental corrections also strengthen regulatory readiness and demonstrate that the facility addressed known hazards with sustainable controls.
NEW QUESTION # 112
If an at-risk patient is left unattended and has an adverse response to medication, this is best classified as:
Answer: A
Explanation:
Leaving an at-risk patient unattended during/after medication administration is typically anactive failure occurring at thesharp end-the point of direct care delivery. Active errors are the observable actions
/omissions by frontline personnel that can immediately contribute to harm (e.g., failure to monitor sedation, failure to reassess after opioids). Risk management objectives, however, require looking beyond the individual act: Was staffing insufficient? Was monitoring policy unclear? Were alarms ineffective? Was there inadequate training or workload overload? Those "blunt end" conditions create latent risk that increases the likelihood of sharp-end failures. Proper classification helps organizations respond with systems fixes (monitoring standards, escalation triggers, staffing acuity tools, continuous pulse oximetry/capnography policies where appropriate) rather than blaming individuals alone.
NEW QUESTION # 113
A doctor fails to administer an indicated test, and the patient deteriorates and must be admitted. This is an example of:
Answer: D
Explanation:
Failing to order or perform an indicated test can represent a diagnostic process failure-an omission that delays recognition of deterioration, leading to harm and escalation of care. Risk management objectives treat diagnostic safety as a systems issue: access to decision support, timely follow-up of abnormal results, clear responsibility for test ordering and review, effective handoffs, and adequate staffing/workload conditions to avoid missed steps. Such errors are often linked to underuse in the IOM quality framework (failure to provide beneficial service) and can drive claims due to preventable worsening. Preventive strategies include standardized pathways, trigger tools for abnormal labs, closed-loop test result management, and teamwork practices that encourage escalation when clinical concern persists despite uncertainty.
NEW QUESTION # 114
......
Pdf CPHRM Free: https://www.prep4sureexam.com/CPHRM-dumps-torrent.html
What's more, part of that Prep4sureExam CPHRM dumps now are free: https://drive.google.com/open?id=1NUIT155auLj9R50TQ9h8jf1mR9ih_-v-