P.S. Free 2026 NCC EFM dumps are available on Google Drive shared by Actual4Labs: https://drive.google.com/open?id=1XrhleJKxlq1bPzN3rDWbn85YPF8iGCMH
EFM learning materials have a variety of self-learning and self-assessment functions to test learning outcomes. EFM study guide is like a tutor, not only gives you a lot of knowledge, but also gives you a new set of learning methods. EFM Exam Practice is also equipped with a simulated examination system that simulates the real exam environment so that you can check your progress at any time.
| Section | Objectives |
|---|---|
| Topic 1: Maternal and Fetal Complications | - High-risk obstetric conditions affecting fetal monitoring - Hypoxia and uteroplacental insufficiency |
| Topic 2: Uterine Activity | - Normal uterine contraction patterns - Tachysystole and abnormal contraction patterns |
| Topic 3: Intrauterine Resuscitation and Interventions | - Maternal position changes and oxygen administration - Fluid management and medication adjustments |
| Topic 4: Fetal Physiology and Oxygenation | - Fetal cardiovascular physiology - Oxygen transport and acid-base balance |
| Topic 5: Intrapartum Assessment and Monitoring | - External and internal monitoring techniques - Risk assessment during labor |
| Topic 6: Fetal Heart Rate Interpretation | - Baseline rate and variability - Category I, II, and III tracing interpretation - Accelerations and decelerations |
>> EFM Official Practice Test <<
If you are worried about that if you fail to pass the exam and will waste your money, if you choose us, there is no need for you to worry about this. We ensure that if you fail to pass your exam by using EFM exam materials of us, we will give you full refund, and no other questions will be asked. Besides, we offer you free update for one year, that is to say, there is no need for you to spend extra money on updating. The update version for EFM Exam Braindumps will be sent to you automatically. You just need to check your mail and change your learning methods in accordance with new changes.
NEW QUESTION # 98
The tracing shown is a: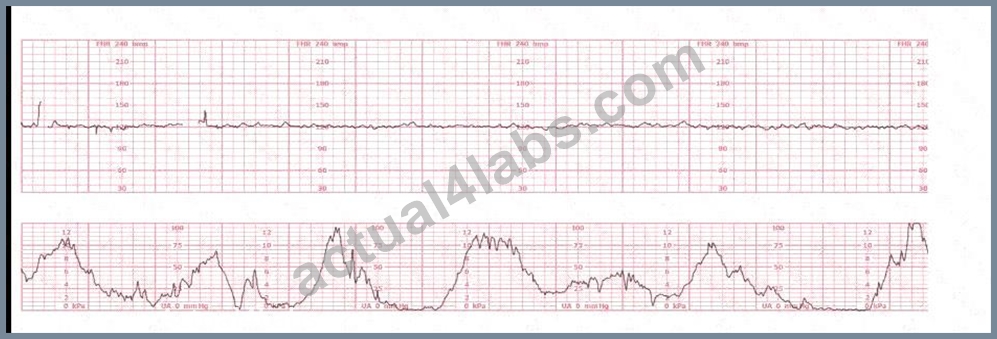
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References (No URLs):
Interpretation of fetal heart rate (FHR) tracings in the NCC C-EFM exam follows the standardized NICHD three-tier classification, which is fully adopted in NCC's content outline and recommended references such as AWHONN Fetal Heart Monitoring Principles & Practices, Miller's EFM Pocket Guide, Menihan, Simpson' s Perinatal Nursing, and Creasy & Resnik.
Baseline:
The tracing demonstrates an FHR baseline around 145-150 bpm, which falls within the normal range of 110-
160 bpm. NCC references define baseline as the mean FHR rounded to increments of 5 bpm over a 10-minute window.
Variability:
The strip shows minimal variability, with amplitude fluctuations approximately 0-2 bpm.
According to NCC-aligned definitions:
* Moderate variability: 6-25 bpm
* Minimal variability: 1-5 bpm
* Absent variability: undetectable amplitude
This tracing shows minimal variability, not moderate, so it cannot be Category I.
Accelerations:
No accelerations are present. Lack of accelerations alone does not classify the tracing as Category III.
Decelerations:
There are no recurrent late decelerations, no recurrent variable decelerations, and no prolonged decelerations. Without these, and with minimal variability, the tracing does not meet Category III criteria.
Category III criteria (per NICHD/NCC):
Must include at least one of the following:
* Absent variability with recurrent late decelerations
* Absent variability with recurrent variable decelerations
* Absent variability with bradycardia
* Sinusoidal pattern
None of these are present.
Category II criteria (per NICHD/NCC):
Category II includes tracings that are not Category I or III.
Examples specifically listed include:
* Minimal variability
* Absent accelerations after fetal stimulation
* Tachycardia
* Bradycardia without absent variability
* Variable or late decelerations occurring intermittently
Because this tracing shows minimal variability, a normal baseline, no accelerations, and no recurrent decelerations, it fits squarely into Category II.
Therefore, the correct classification is Category II.
References:NCC C-EFM Candidate Guide and Content Outline (2025); AWHONN Fetal Heart Monitoring Principles & Practices; Miller's Fetal Monitoring Pocket Guide; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing; Creasy & Resnik Maternal-Fetal Medicine; NICHD Three-Tier FHR Interpretation System.
NEW QUESTION # 99
Patient safety is enhanced when alarms:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
NCC and AWHONN emphasize unit-wide shared responsibility for:
* Recognizing abnormal maternal or fetal findings
* Calling for help
* Triggering emergency responses (e.g., unit huddle, rapid response, safety pathways) Safety culture requires:
* Any staff member (RN, tech, provider) to initiate an alarm or escalate concern
* No hierarchy delay
* Rapid action when fetal compromise is suspected
Why the other answers are wrong:
* A. Determined by unit leaders # incorrect; safety is team-wide, not hierarchical.
* C. Occur infrequently # false; alarms must occur whenever needed, not limited.
Correct answer: B. Can be called by anyone.
References:NCC Professional Issues Domain; AWHONN Standards for Professional Practice; Perinatal Safety Bundles; Simpson & Creehan.
NEW QUESTION # 100
The baseline fetal heart rate decreases with gestational age as a result of an increase in:
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
As gestation advances:
* Vagal (parasympathetic) control increases,
* Sympathetic dominance decreases,
* Resulting in a lower baseline heart rate.
NCC physiology teaching:
"Baseline FHR decreases with advancing gestational age due to maturation and increasing parasympathetic tone." Why the others are incorrect:
* Catecholamines increase heart rate, not decrease it.
* Intrinsic ventricular rate does not change significantly with gestational age.
Thus, the correct physiologic factor is increased parasympathetic tone.
References:NCC Physiology Domain; AWHONN; Menihan; Simpson & Creehan; Creasy & Resnik.
NEW QUESTION # 101
A key differentiating factor when determining if a deceleration is early or late is the
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract (NCC-Referenced Sources) AWHONN and Menihan clearly state that classification of decelerations is determined by their timing relative to uterine contractions:
* Early decelerations: "mirror the contraction; onset, nadir, and recovery occur simultaneously with the contraction."
* Late decelerations: "begin after the contraction begins and return to baseline after the contraction ends." Depth is not a differentiating feature, as both early and late decelerations may vary in depth. The onset-to- nadir interval is used to differentiate variable vs. early/late, not early vs. late.
Thus, timing relative to contractions is the correct NCC-supported answer.
NEW QUESTION # 102
Based on the tracing shown, the first action should be to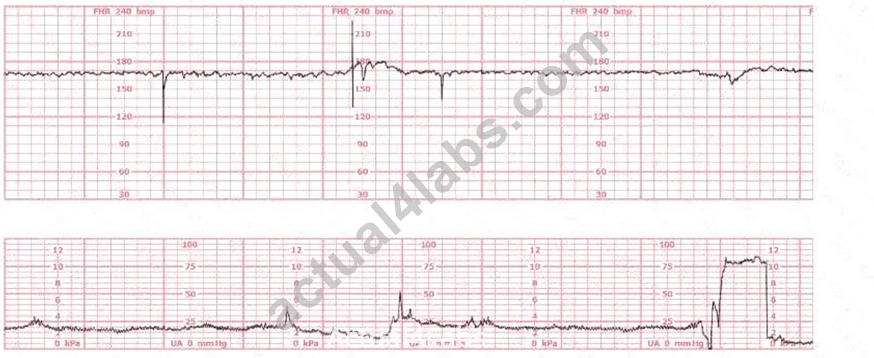
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract (No URLs or Links):
According to the NCC C-EFM exam outline and AWHONN Fetal Heart Monitoring Principles (2022), the first step when evaluating a concerning fetal heart rate pattern is to verify uterine activity, because the fetal response is often directly associated with contraction frequency, strength, or tachysystole. AWHONN states that "the clinician must confirm maternal-fetal physiology and uterine activity by palpation when interpreting any FHR pattern, as tocodynamometry may under- or overestimate uterine pressure." Menihan's Electronic Fetal Monitoring further emphasizes: "Always validate the contraction pattern via maternal abdominal palpation before proceeding with additional interventions." The tracing shows a late-appearing deceleration pattern with uncertain contraction correlation because the external toco waveform is inadequate (flat or poorly recorded). Before determining whether the decelerations are early, late, or variable, the clinician must confirm whether contractions are present, absent, or excessive. This step is listed as a core competency under Pattern Recognition & Intervention in the NCC Candidate Guide.
Therefore, palpating for contractions is the required first intervention.
References:AWHONN Fetal Heart Monitoring (2022-2024 Edition)Menihan: Electronic Fetal MonitoringSimpson & Creasy: Perinatal Nursing / Maternal-Fetal PhysiologyNCC C-EFM Content Outline - Pattern Recognition and Intervention Domain
NEW QUESTION # 103
......
Choosing valid NCC dumps means closer to success. Before you buy our products, you can download the free demo of EFM test questions to check the accuracy of our dumps. Besides, there are 24/7 customer assisting to support you in case you may have any questions about EFM Dumps PDF or download link.
EFM Reliable Exam Cost: https://www.actual4labs.com/NCC/EFM-actual-exam-dumps.html
P.S. Free 2026 NCC EFM dumps are available on Google Drive shared by Actual4Labs: https://drive.google.com/open?id=1XrhleJKxlq1bPzN3rDWbn85YPF8iGCMH