DOWNLOAD the newest CertkingdomPDF EFM PDF dumps from Cloud Storage for free: https://drive.google.com/open?id=1F3PBOfYafkayW--sej6HBqIE6VyOP3Nr
We've always put quality of our EFM study guide on top priority. We don’t strongly chase for the number of products we have manufactured. Each EFM test engine will go through strict inspection from many aspects such as the operation, compatibility test and so on. Also, we have final random sampling survey before we sale our EFM practice material to our customers. The quality inspection process is completely strict. The most professional experts of our company will check the study guide and deal with the wrong parts. What you have bought will totally have no problem. That is why we can survive in the market now. Our company is dedicated to carrying out the best quality EFM Test Engine. Any small mistake is intolerant. You can buy our products at ease.
| Section | Weight | Objectives |
|---|---|---|
| Professional Issues | 5% | - Clinical Practice and Safety
|
| Electronic Monitoring Equipment | 5% | - Monitoring Systems
|
| Fetal Assessment Methods | 9% | - Assessment Techniques
|
| Physiology | 11% | - Maternal-Fetal Physiology
|
| Pattern Recognition and Intervention | 70% | - Fetal Heart Rate Patterns
|
It is the right time to think about your professional career. The right path is to enroll in Certified - Electronic Fetal Monitoring EFM certification and start preparation with the assistance of NCC EFM PDF dumps and practice test software. The NCC EFM PDF Questions file and practice test software both are ready to download. Just pay an affordable NCC EFM exam dumps charge and download files and software.
NEW QUESTION # 116
A 30-year-old woman (G2P0) is experiencing preterm labor at 26-weeks gestation. She is receiving magnesium sulfate for neuroprotection. Her external fetal monitoring tracing over the past 30 minutes is shown. The next step would be to: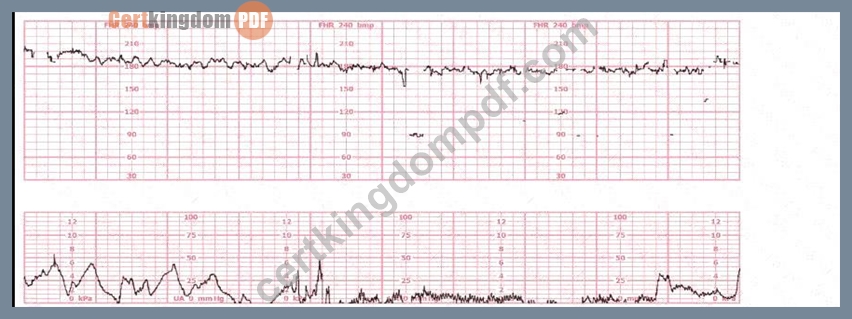
Answer: C
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
This tracing shows:
* Baseline ~170-175 bpm # fetal tachycardia
* Minimal variability
* No contractions of significance
* Maternal treatment with magnesium sulfate, which typically decreases baseline and variability-not increase it NCC and AWHONN physiology guidelines emphasize that fetal tachycardia is most commonly associated with maternal infection, including chorioamnionitis, especially in preterm labor.
Magnesium sulfate does not cause tachycardia; it generally causes:
* # baseline
* # variability
Thus, fetal tachycardia + minimal variability in a preterm patient strongly suggests maternal infection, requiring evaluation for chorioamnionitis.
Why the wrong answers are incorrect:
* A. Acetaminophen # used after confirming fever, not before evaluating the cause.
* B. Discontinuing magnesium # magnesium sulfate does not cause tachycardia; discontinuing it removes fetal neuroprotection.
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; Simpson & Creehan; Menihan EFM; Creasy & Resnik.
NEW QUESTION # 117
A fetal heart rate tracing is abnormal. A change in maternal position and oxygen administration do not correct the pattern. Following birth, a fetal cord blood sample is taken:
pH = 7.25
PaCO# = 46 mm Hg
PaO# = 20 mm Hg
HCO# = 22 mEq/L
Base deficit = -4 mEq/L
These results are best interpreted as:
Answer: C
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
Normal umbilical arterial values per NCC/AWHONN/Menihan:
* pH: 7.20-7.30
* PaCO#: 45-55 mmHg
* HCO#: 20-24 mEq/L
* Base deficit: 0 to -5 (normal to mild respiratory changes)
This sample shows:
* pH 7.25 # normal
* Base deficit -4 # no metabolic acidosis
* HCO# normal
* Slightly elevated PaCO#, consistent with mild respiratory influence but still normal
* PaO# 20 mmHg is normal for cord arterial blood
This profile is not acidotic (acidosis requires pH <7.10 and base deficit #12).
It also does not indicate hypoxia, which would present with metabolic acidosis.
Therefore: Normal.
References:NCC C-EFM Candidate Guide; AWHONN FHMPP; Menihan; Simpson & Creehan; Creasy & Resnik.
NEW QUESTION # 118
A woman at 34-weeks gestation is in active labor after spontaneous rupture of membranes.
Accelerations should be documented as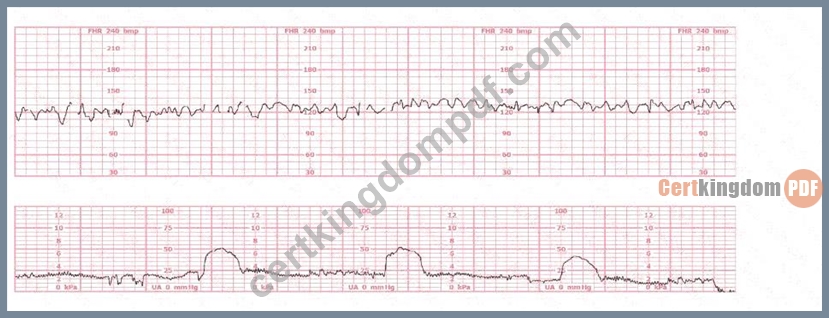
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract (No URLs)
For fetuses before 32-34 weeks, the National Certification Corporation (NCC) follows the physiologic standards established by AWHONN, Simpson & Creehan, Menihan, and Creasy & Resnik, which emphasize that preterm fetuses have less mature autonomic nervous system development, resulting in smaller and shorter accelerations.
According to the NCC C-EFM Exam Content Outline (Pattern Recognition & Intervention) and the AWHONN Fetal Heart Monitoring Principles (2022-2024):
* Preterm fetuses (<32 weeks) normally demonstrate 10 bpm × 10 sec accelerations.
* By approximately 32-34 weeks, accelerations may begin transitioning toward 15×15, but the accepted standard for documentation at 34 weeks remains 10×10, unless clearly meeting 15×15 criteria.
* NCC emphasizes using gestational-age-appropriate criteria for documenting accelerations, because autonomic reactivity increases gradually and is not fully comparable to term until after
32-34 weeks.
Menihan's Electronic Fetal Monitoring also states that preterm fetuses "should be evaluated with the
10×10 rule until it is clear that the fetus is demonstrating mature 15×15 acceleratory capacity." Simpson & Creehan reinforce this point, noting that accelerations in late preterm gestations "may not consistently reach 15 bpm for 15 seconds, and thus 10×10 remains the appropriate designation." Since the patient is 34 weeks, the fetus is late-preterm and may not reliably meet the full 15×15 criteria; therefore, the correct documentation standard remains 10×10.
Thus, accelerations should be charted as:
"Present 10×10."
References
* NCC C-EFM Candidate Guide 2025 - Content Domain: Pattern Recognition and Intervention
* AWHONN Fetal Heart Monitoring Principles & Practices, 2022-2024
* Menihan: Electronic Fetal Monitoring: Concepts and Applications
* Simpson & Creehan: Perinatal Nursing
* Miller: Fetal Monitoring Pocket Guide
* Creasy & Resnik: Maternal-Fetal Medicine
NEW QUESTION # 119
The ratio of oxyhemoglobin to the total amount of hemoglobin available is called oxygen
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources Oxygen saturation refers to the percentage of hemoglobin binding sites occupied by oxygen. NCC physiology resources, including Simpson & Creehan and Creasy & Resnik, define oxygen saturation as the
"ratio of oxyhemoglobin to total hemoglobin"-the same definition used in fetal oxygenation discussions.
Oxygen affinity refers to hemoglobin's tendency to bind oxygen (related to the oxyhemoglobin dissociation curve).
Oxygen carrying capacity refers to the total amount of oxygen hemoglobin can transport, independent of current saturation.
AWHONN and Menihan emphasize that fetal oxygenation assessment is dependent on understanding oxygen saturation, not affinity or carrying capacity, when discussing fetal hypoxemia and gas exchange.
References:
AWHONN - Fetal Heart Monitoring Principles & PracticesSimpson & Creehan - Perinatal NursingCreasy & Resnik - Maternal-Fetal MedicineMenihan - EFM ConceptsMiller's Pocket Guide
NEW QUESTION # 120
Usually, the duration of an early deceleration in comparison with the contraction is:
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
An early deceleration is defined by NICHD and NCC as a gradual decrease and return of the fetal heart rate associated with uterine contractions. NCC emphasizes that early decelerations are:
* Symmetrical
* Uniform in shape
* Mirror images of the contraction
This means:
* Onset of deceleration = onset of contraction
* Nadir of deceleration = peak of contraction
* Recovery = end of contraction
* Duration of the deceleration # duration of the contraction
Thus, the correct answer is C. The same.
References:NCC C-EFM Candidate Guide; AWHONN Fetal Heart Monitoring Principles & Practices; NICHD Definitions; Menihan Electronic Fetal Monitoring; Simpson & Creehan Perinatal Nursing.
NEW QUESTION # 121
......
It will improve your skills to face the difficulty of the EFM exam questions and accelerate the way to success in IT filed with our latest study materials. Free demo of our EFM dumps pdf can be downloaded before purchase and 24/7 customer assisting support can be access. Well preparation of EFM Practice Test will be closer to your success and get authoritative certification easily.
EFM Latest Dumps Pdf: https://www.certkingdompdf.com/EFM-latest-certkingdom-dumps.html
BTW, DOWNLOAD part of CertkingdomPDF EFM dumps from Cloud Storage: https://drive.google.com/open?id=1F3PBOfYafkayW--sej6HBqIE6VyOP3Nr