BTW, DOWNLOAD part of ExamsTorrent EFM dumps from Cloud Storage: https://drive.google.com/open?id=1OZxjx71lXUSZaEKZfKPNugvnAmK3UyEu
One NCC certification will help you get highly favor of large enterprises, it will bring you better opportunities. EFM valid exam dumps PDF will be a stepping-stone for you to success. The most important method for passing exams is targeted learning and preparing. Programmatic learning may make you know professional knowledge better. But it will not only cost a lot of your time and energy but also can't guarantee you pass. Our EFM Valid Exam Dumps PDF can help you pass exam for sure.
| Section | Objectives |
|---|---|
| Intrauterine Resuscitation and Interventions | - Maternal position changes and oxygen administration - Fluid management and medication adjustments |
| Intrapartum Assessment and Monitoring | - External and internal monitoring techniques - Risk assessment during labor |
| Uterine Activity | - Normal uterine contraction patterns - Tachysystole and abnormal contraction patterns |
| Fetal Physiology and Oxygenation | - Oxygen transport and acid-base balance - Fetal cardiovascular physiology |
| Fetal Heart Rate Interpretation | - Category I, II, and III tracing interpretation - Baseline rate and variability - Accelerations and decelerations |
| Maternal and Fetal Complications | - Hypoxia and uteroplacental insufficiency - High-risk obstetric conditions affecting fetal monitoring |
We also fully consider the characteristics of the user on studying the EFM exam questions. For example, many people who choose to obtain a EFM certificate don't have a lot of time to prepare for the exam. Based on this point, our team of experts really took a lot of thought in the layout of the content. The contents of EFM Exam Materials are carefully selected by experts. We hope you can get the most effective knowledge in the shortest possible time.
NEW QUESTION # 35
(Full question statement)
The American College of Obstetricians and Gynecologists (ACOG) recommends continuous electronic fetal monitoring in pregnancies when there is:
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract Without Links:
NCC relies heavily on ACOG Practice Bulletins for risk-based monitoring decisions. ACOG identifies maternal diabetes (pregestational or poorly controlled gestational diabetes) as a key high-risk obstetric condition warranting continuous electronic fetal monitoring due to risks such as fetal hypoxia, macrosomia, and metabolic complications.
In contrast, a history of preterm birth does not necessarily require continuous monitoring unless current pregnancy complications are present.
Macrosomia alone does not automatically justify continuous EFM unless accompanied by other risk factors.
Therefore, according to NCC-aligned ACOG clinical criteria, maternal diabetes is the correct indication.
NEW QUESTION # 36
Intermittent fetal heart rate auscultation for a low-risk, spontaneous laboring patient who is 4-5 centimeters dilated should be assessed at intervals every
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract (No URLs or Links) NCC aligns with AWHONN's "Practice Guidelines for Fetal Heart Monitoring", which specify the appropriate frequency of intermittent auscultation (IA) based on labor phase and risk level. For low- risk patients in active labor, IA must occur:
* Every 15-30 minutes during active labor
* Every 5 minutes during second stage with pushing
AWHONN and Menihan emphasize that intermittent auscultation must follow standardized time intervals to ensure adequate fetal surveillance. These intervals reflect the physiologic understanding that fetal compromise may evolve over relatively short time periods, and active labor (4-7 cm dilation) represents a time of increasing stress on fetal oxygenation.
Simpson & Creehan explain that IA frequency should increase as labor intensifies, and that the 15-30- minute interval is the nationally recognized standard for low-risk active labor. NCC's exam content domain "Fetal Assessment Methods" reinforces knowing these surveillance intervals for safe low- intervention care.
Thus, for a 4-5 cm dilated, low-risk, spontaneous labor, the correct IA interval is every 15-30 minutes.
References (No URLs)
* NCC C-EFM Candidate Guide 2025 - Fetal Assessment Methods
* AWHONN Practice Guidelines for Fetal Heart Monitoring, 2022-2024
* Menihan: Electronic Fetal Monitoring
* Simpson & Creehan: Perinatal Nursing
* Miller: Fetal Monitoring Pocket Guide
NEW QUESTION # 37
A fetus displays a baseline heart rate of 125 beats per minute with moderate variability. During a contraction, the baseline rate drops abruptly to 80 beats per minute with gradual return to baseline over 90 seconds. This is classified as:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Sources:
NICHD definitions:
A variable deceleration is identified by:
* Abrupt onset(drop from baseline to nadir in <30 seconds)
* Depth #15 bpm
* Duration #15 seconds and <2 minutes
* Variable timing relative to contractions
* Variable shape (sharp drop, jagged descents, rapid recovery)
The scenario describes:
* Abrupt drop from 125 # 80 bpm (rapid onset)
* Lasting 90 seconds (still <2 minutes)
* Gradual return but still within variable range
* Occurring during a contraction
* Depth >15 bpm
This meets ALL criteria for a variable deceleration.
Why the other options are wrong:
* A. Early deceleration
* Requires gradual onset (>30 seconds).
* Mirrors contraction shape.
* Caused by head compression.
* This decel is abrupt, so NOT early.
* B. Prolonged deceleration
* Requires #2 minutes and <10 minutes.
* This decel lasts 90 seconds, which is below the threshold.
Correct classification: Variable deceleration.
References:NICHD FHR Definitions; NCC Pattern Recognition Domain; AWHONN FHMPP; Menihan; Simpson & Creehan.
NEW QUESTION # 38
A reliable indicator of fetal oxygenation is fetal
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources AWHONN and NICHD definitions state that fetal accelerations are a strong indicator of adequate fetal oxygenation and neurologic integrity. Accelerations reflect intact sympathetic and parasympathetic balance and adequate oxygen reserve.
Simpson & Creehan emphasize accelerations as "the most reliable sign of fetal well-being," because they require intact autonomic function, sufficient pH, and adequate oxygenation. Menihan also identifies accelerations as the most reassuring feature on a fetal heart tracing.
Fetal movement is helpful but not directly reflective of oxygenation, as movements can decline for non- hypoxic reasons (sleep cycles, maternal sedation). Regular sleep-wake cycles are normal developmental neurologic patterns and not oxygenation markers.
Creasy & Resnik reinforce that "presence of accelerations reliably indicates absence of metabolic acidemia." References:
AWHONN - Fetal Heart Monitoring Principles & PracticesSimpson & Creehan - Perinatal NursingMenihan
- Electronic Fetal MonitoringCreasy & Resnik - Maternal-Fetal MedicineMiller's Pocket Guide
NEW QUESTION # 39
The tracing shown is a: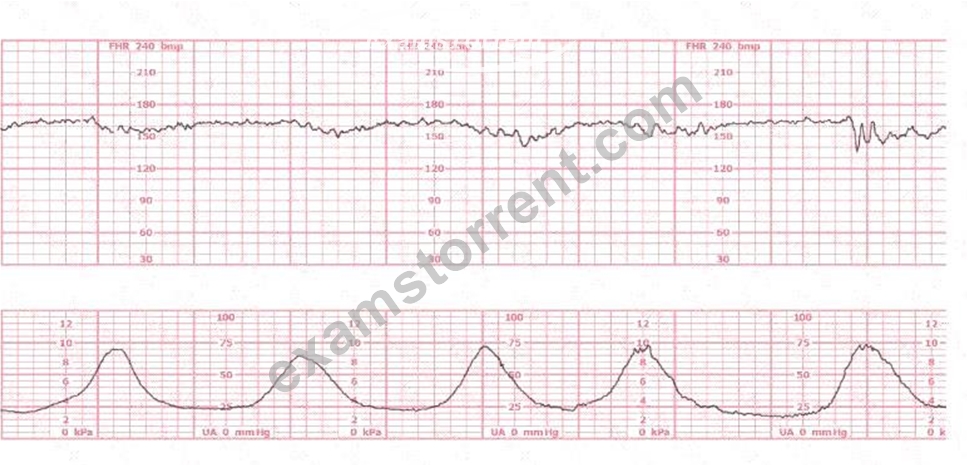
Answer: C
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The tracing demonstrates:
* Baseline: approx. 140 bpm
* Variability: minimal-to-moderate (fluctuating but not consistently moderate)
* Decelerations: shallow variable decelerations
* Accelerations: not consistently present
According to NICHD/NCC definitions:
Category I requires ALL of the following:
* Baseline 110-160
* Moderate variability
* No late or variable decelerations
* Early decels and accelerations may be present
This tracing does not have consistently moderate variability and does have variable decelerations, so it is not Category I.
Category III requires ANY of the following:
* Absent variability with recurrent late decels
* Absent variability with recurrent variable decels
* Absent variability with bradycardia
* Sinusoidal pattern
This tracing does not show absent variability, bradycardia, or recurrent significant lates.
Category II includes:
* Minimal variability
* Absence of accelerations
* Variable decelerations
* Tracings not clearly Category I or III
This strip fits Category II exactly due to minimal variability + intermittent variable decelerations.
Thus, the correct classification is Category II.
References:NCC C-EFM Candidate Guide; NICHD Three-Tier Interpretation System; AWHONN Fetal Heart Monitoring Principles & Practices; Menihan; Miller; Simpson & Creehan.
NEW QUESTION # 40
......
We are a leading corporation in this line handling EFM study questions well with passing rate up to 98 and over percent, which is an unreachable goal for others. So our EFM preparation exam enjoys good sales for the excellent quality and reasonable prices in recent years. And we are so sure that we can serve you even better than you can imagine with our EFM learning guide since we are keeping on doing a better job in this career.
EFM Dumps Free Download: https://www.examstorrent.com/EFM-exam-dumps-torrent.html
P.S. Free & New EFM dumps are available on Google Drive shared by ExamsTorrent: https://drive.google.com/open?id=1OZxjx71lXUSZaEKZfKPNugvnAmK3UyEu