Persistence and proficiency made our experts dedicated in this line over so many years. Their passing rates are over 98 and more, which is quite riveting outcomes. After using our EFM practice materials, you will have instinctive intuition to conquer all problems and difficulties in your review. We are sure you can seep great deal of knowledge from our EFM practice materials in preference to other materials obviously. These EFM practice materials have variant kinds including PDF, app and software versions.
| Section | Objectives |
|---|---|
| Fetal Heart Rate Interpretation | - Baseline rate and variability - Category I, II, and III tracing interpretation - Accelerations and decelerations |
| Uterine Activity | - Normal uterine contraction patterns - Tachysystole and abnormal contraction patterns |
| Maternal and Fetal Complications | - High-risk obstetric conditions affecting fetal monitoring - Hypoxia and uteroplacental insufficiency |
| Intrapartum Assessment and Monitoring | - Risk assessment during labor - External and internal monitoring techniques |
| Fetal Physiology and Oxygenation | - Oxygen transport and acid-base balance - Fetal cardiovascular physiology |
| Intrauterine Resuscitation and Interventions | - Fluid management and medication adjustments - Maternal position changes and oxygen administration |
Our windows software of the EFM study materials are designed to simulate the real test environment. If you want to experience the real test environment, you must install our EFM preparation questions on windows software. Also, it only support running on Java environment. If you do not install the system, the system of our EFM Exam Braindumps will automatically download to ensure the normal operation.
NEW QUESTION # 13
Uterine contraction intensity is manually measured by degree of uterine:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From NCC-Aligned Equipment Concepts:
When using external tocodynamometry, uterine contraction intensity cannot be measured in mmHg. It is assessed manually, using palpation. NCC and AWHONN teach:
* Contraction intensity is estimated by palpating the fundus during a contraction.
* The degree of firmness versus indentation determines intensity:
* Mild # uterus easily indented
* Moderate # firm, difficult to indent
* Strong # rigid, cannot be indented
Why the incorrect answers are wrong:
* B. Muscle strength - Not measurable by external or manual exam.
* C. Pain - Not a reliable indicator; pain perception varies widely and does not correlate with uterine intensity.
Thus, the correct manual measurement is done through uterine indentation, making A correct.
References:NCC C-EFM Candidate Guide; AWHONN Principles & Practices; Menihan EFM; Miller's Pocket Guide; Simpson & Creehan.
NEW QUESTION # 14
A 20-year-old woman (G1P0) at 40-weeks gestation was admitted for cervical ripening with dinoprostone (Cervidil) four hours ago. She developed the pattern shown one hour ago. She has been changed to a lateral position and given a fluid bolus, and the pattern continues. An appropriate intervention would be to: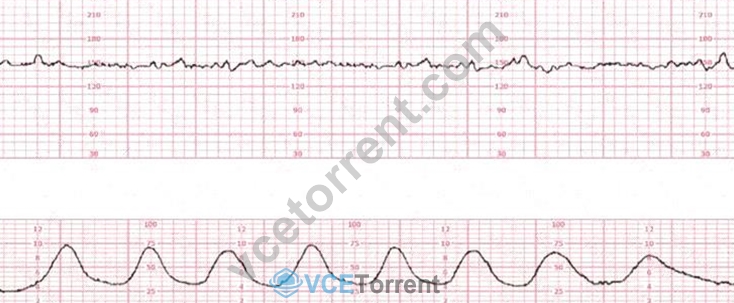
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract-Based NCC C-EFM References:
The tracing shows tachysystole (more than 5 contractions in 10 minutes) with minimal variability and recurrent decelerations consistent with uteroplacental insufficiency caused by excessive uterine activity.
Dinoprostone (Cervidil) is a uterotonic prostaglandin, and one of its known complications is uterine tachysystole with Category II or III fetal heart rate patterns.
NCC/AWHONN guidance for tachysystole caused by prostaglandins:
* FIRST intervention: Remove the dinoprostone insert.
* Reposition the patient (already done).
* IV fluid bolus (already done).
* Consider terbutaline only if tachysystole persists after removal of the agent.
Since maternal repositioning and IV fluids have already failed, the next step is to remove the cervical ripening agent.
Why other answers are incorrect:
* A. Continue to observe - Never acceptable with tachysystole + fetal intolerance.
* B. Terbutaline - May be used after prostaglandin removal, not before.
Thus, the correct answer is C. Remove the dinoprostone insert.
References:NCC C-EFM Candidate Guide; AWHONN Fetal Heart Monitoring Principles & Practices; Menihan; Miller's Pocket Guide; NICHD Definitions; Creasy & Resnik.
NEW QUESTION # 15
(Full question statement)
The American College of Obstetricians and Gynecologists (ACOG) recommends continuous electronic fetal monitoring in pregnancies when there is:
Answer: B
Explanation:
Comprehensive and Detailed Explanation From Exact Extract Without Links:
NCC relies heavily on ACOG Practice Bulletins for risk-based monitoring decisions. ACOG identifies maternal diabetes (pregestational or poorly controlled gestational diabetes) as a key high-risk obstetric condition warranting continuous electronic fetal monitoring due to risks such as fetal hypoxia, macrosomia, and metabolic complications.
In contrast, a history of preterm birth does not necessarily require continuous monitoring unless current pregnancy complications are present.
Macrosomia alone does not automatically justify continuous EFM unless accompanied by other risk factors.
Therefore, according to NCC-aligned ACOG clinical criteria, maternal diabetes is the correct indication.
NEW QUESTION # 16
Based on the tracing shown, the first action should be to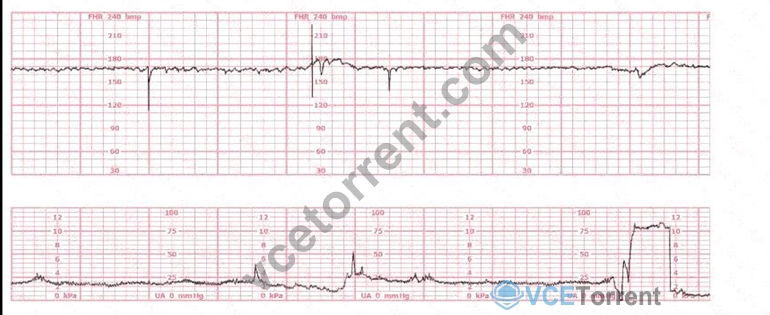
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract (No URLs or Links):
According to the NCC C-EFM exam outline and AWHONN Fetal Heart Monitoring Principles (2022), the first step when evaluating a concerning fetal heart rate pattern is to verify uterine activity, because the fetal response is often directly associated with contraction frequency, strength, or tachysystole. AWHONN states that "the clinician must confirm maternal-fetal physiology and uterine activity by palpation when interpreting any FHR pattern, as tocodynamometry may under- or overestimate uterine pressure." Menihan's Electronic Fetal Monitoring further emphasizes: "Always validate the contraction pattern via maternal abdominal palpation before proceeding with additional interventions." The tracing shows a late-appearing deceleration pattern with uncertain contraction correlation because the external toco waveform is inadequate (flat or poorly recorded). Before determining whether the decelerations are early, late, or variable, the clinician must confirm whether contractions are present, absent, or excessive. This step is listed as a core competency under Pattern Recognition & Intervention in the NCC Candidate Guide.
Therefore, palpating for contractions is the required first intervention.
References:AWHONN Fetal Heart Monitoring (2022-2024 Edition)Menihan: Electronic Fetal MonitoringSimpson & Creasy: Perinatal Nursing / Maternal-Fetal PhysiologyNCC C-EFM Content Outline - Pattern Recognition and Intervention Domain
NEW QUESTION # 17
The fetal heart rate tracing shown represents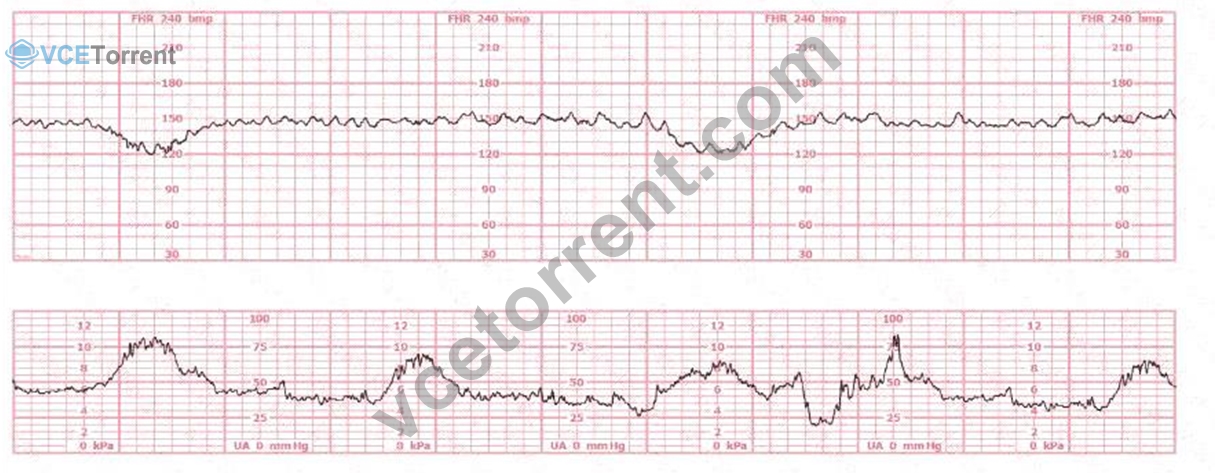
Answer: A
Explanation:
Comprehensive and Detailed Explanation From Exact Extract NCC-Recommended Sources The tracing demonstrates a baseline within normal limits, moderate variability, and recurrent variable decelerations associated with contractions. According to NICHD/NCC definitions reproduced in AWHONN' s Fetal Heart Monitoring Principles & Practices and Menihan's Electronic Fetal Monitoring, recurrent variable decelerations with preserved variability classify the tracing as Category II.
A Category I pattern must show baseline 110-160, moderate variability, and absence of late or variable decelerations. Because this tracing shows recurrent variable decelerations, it does not meet Category I criteria.
Category III requires absent variability PLUS recurrent late decelerations, recurrent variable decelerations, bradycardia, or a sinusoidal pattern. This tracing shows moderate variability, therefore it cannot be Category III.
Simpson & Creehan emphasize that variable decelerations reflect cord compression and fall into Category II unless accompanied by absent variability. Miller's Pocket Guide confirms that moderate variability maintains fetal compensatory reserve, keeping the pattern in Category II.
References:
AWHONN - Fetal Heart Monitoring Principles & PracticesMenihan - Electronic Fetal MonitoringSimpson & Creehan - Perinatal NursingCreasy & Resnik - Maternal-Fetal MedicineMiller's Pocket Guide
NEW QUESTION # 18
......
You may think choosing EFM practice materials at the first time is a little bit like taking gambles. However, you can be assured by our EFM learning quiz with free demos to take reference, and professional elites as your backup. They are a bunch of censorious elites who do not compromise on any errors happened on our EFM Training Materials. So their accuracy rate is unbelievably high and helped over 98 percent of exam candidates pass the EFM exam.
EFM Practice Exam Questions: https://www.vcetorrent.com/EFM-valid-vce-torrent.html